Özet
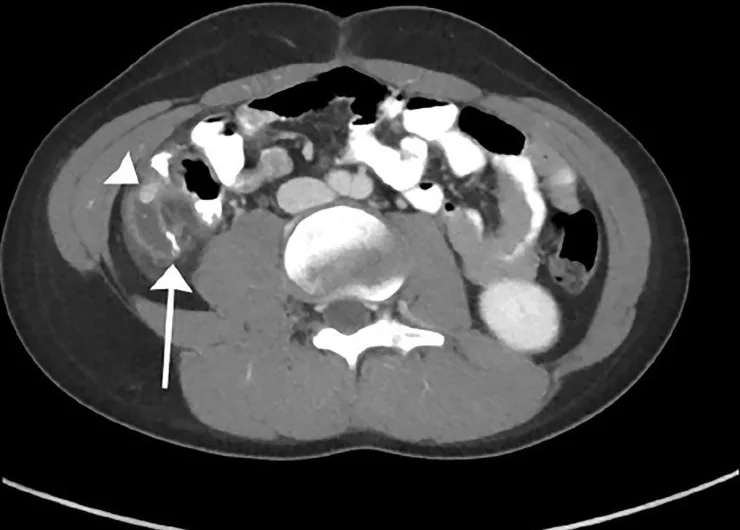
Güdük apandisiti, apendektomi sonrası kalan apendiks segmentinin yeniden inflamasyonudur ve önceki cerrahi öyküsü tanının akla gelmesini geciktirebilir. Kontrastlı BT, çekum tabanındaki kör sonlanan rezidüel tüpü, cerrahi klipsleri ve çevresel inflamasyonu birlikte gösterir. Tanı için yalnız klips varlığı değil, klips komşuluğundaki güdüğün anormal duvarı ve çevre dokular önemlidir. Gözden kaçması perforasyon ve periçekal apseyle sonuçlanabilir.
Faz ve pencere
- Portal tanısal
- Kontrastlı BT'de çekum tabanına yapışık kör sonlanan rezidüel apendiks segmentinde lümen genişlemesi, duvar kalınlaşması/hiper-kontrastlanma, periçekal yağ kirlenmesi ve varsa apse görülür; cerrahi klipsler anatomik yer belirtecidir.
Önerilen pencereler: Batın (G 400 / M 50), Yumuşak doku (G 400 / M 40).
BT bulguları
- Çekum tabanında kör sonlanan rezidüel tüp — klipsli cerrahi yatağa komşu apendiks güdüğü çekum duvarından izlenir.
- Güdük lümeninde distansiyon — rezidüel segment genişleyebilir ve lümeninde sıvı veya apendikolit görülebilir.
- Güdük duvarında kalınlaşma ve hiper-kontrastlanma — inflamasyon, klips çevresindeki rezidüel tüp duvarında belirgindir.
- Perisekal yağ kirlenmesi — inflamatuvar çizgilenme çekum tabanı ve cerrahi yatağın çevresinde yoğunlaşır.
- apendikolit — güdük lümeninde obstrüktif odak olarak bulunabilir; lümen dışındaki kalkülden ayrılmalıdır.
- Çekum veya terminal ileumda reaktif kalınlaşma — cerrahi yatağa komşu bağırsak duvarı ikincil etkilenebilir.
- Perisekal apse veya ekstralüminal gaz — komplike güdük inflamasyonunda koleksiyon ve perforasyon bulguları gelişebilir.
Normalde
Apendektomi sonrası çekum tabanında klips veya cerrahi materyal görülebilir; normal ameliyat yatağında çevre yağ planları sakindir ve distandü, kalın duvarlı kör sonlanan güdük izlenmez. Klipslerin çekum tabanına göre konumunu belirleyip hemen komşuluğunda rezidüel tüp, duvar kontrastlanması ve periçekal inflamasyon bulunup bulunmadığını araştırın.
Normal BT ile kıyasla
Aynı bölgenin, kaynak veri setinde patoloji içermediği belirtilen bir BT incelemesini kesit kesit kaydırın; organ sınırlarını açarak anatomiyi hasta görüntüsüyle karşılaştırın. Küçük rastlantısal bulgular tümüyle dışlanmamıştır.
Kaynak: TotalSegmentator v2.01 veri seti (Wasserthal ve ark., Radiology: Artificial Intelligence 2023), CC BY 4.0, vaka s0119; organ sınırları veri setinin otomatik segmentasyonundan, birleştirilerek sadeleştirildi. Görüntüler 2,5 mm kesit aralığına yeniden örneklendi.
Ayırıcı tanı
- Perisekal apse
- koleksiyon klipsli yatağa yakın olabilir; içinde güdük veya inflame apendiksin izlenmesi kaynağı ayırt ettirir.
- Çekal divertikülit
- divertikülit güdük apandisitinin ayırıcı tanılarından biri olabilir; ancak kaynaklarda çekal divertikülitin özgül BT bulguları tanımlanmamıştır.
- Terminal ileit
- duvar kalınlaşması distal ileum segmentini izler; çekum tabanındaki rezidüel kör tüp inflamasyonun odağı değildir.
- Postoperatif fibrotik değişiklik
- klips çevresinde çizgisel skar olabilir, ancak distandü duvarı kontrastlanan güdük ve aktif yağ kirlenmesi beklenmez.
- Sağ kolon divertiküliti
- inflamatuvar odak çıkan kolon duvarındaki divertiküle bağlıdır, apendektomi yatağına değil.
Tuzaklar
- Öyküde apendektomi bulunmasını apendiks kaynaklı hastalığı dışlamak için kullanmayın; klipslerin ötesinde rezidüel güdüğü ayrıca arayın.
- Klips artefaktı küçük güdük lümenini örtebilir; koronal ve sagittal reformatlarda çekum tabanını yeniden izleyin.
- Tek başına klips çevresi hafif skar inflamatuvar güdük tanısı değildir; rezidüel tüp duvarı ve çevre yağ bulgularını eşleştirin.
Kendini dene
Apendektomi öyküsü olan hastada klips komşuluğunda kalın duvarlı, distandü kör tüp ve yağ kirlenmesi var. Tanı nedir?
Cevabı göster
Güdük apandisiti. Klipsli cerrahi yatağa komşu inflame rezidüel kör tüp güdük apandisitidir. Klipsli cerrahi yatağa komşu inflame rezidüel kör tüp güdük apandisitidir; prior apendektomide düşük şüpheli ayırıcı tanı oluşturur ve tanı gecikebilir.
Güdük apandisitini destekleyen BT bulgusu hangisidir?
Cevabı göster
Güdük lümeninde genişleme ve periçekal inflamatuvar infiltrasyon. Güdük lümeninde genişleme ve periçekal inflamatuvar infiltrasyon, güdük apandisitinde bildirilen BT bulgularıdır.
Kaynaklar
Bu sayfadaki 34 cümle ve 2 quiz sorusu aşağıdaki kaynaklardan alıntılarla otomatik olarak karşılaştırıldı; 4 cümle bu karşılaştırmada düzeltildi (2026-10-09).
- Stump Appendicitis: A 25-Year Review of Pathophysiology, Diagnosis, and Management (2000-2025)pmc.ncbi.nlm.nih.gov
- Endoscopic retrograde appendicitis therapy: Progress in clinical applicationpmc.ncbi.nlm.nih.gov
- Laparoscopic management for stump appendicitispmc.ncbi.nlm.nih.gov
- Adenocarcinoma of Stump Appendicitis: An Extremely Rare Pathology – A Literature Reviewpmc.ncbi.nlm.nih.gov
- From Diagnosis to Management; Mucocele of Stump Appendicitis, Extremely Rare Finding in an Uncommon Surgical Disease: Literature Reviewpmc.ncbi.nlm.nih.gov
- Stump appendicitis: a surgeon's dilemma.pubmed.ncbi.nlm.nih.gov
- Beyond appendicitis; radiologic review of unusual and rare pathology of the appendix.pubmed.ncbi.nlm.nih.gov
- A 60-year literature review of stump appendicitis: the need for a critical view.pubmed.ncbi.nlm.nih.gov
- Adenocarcinoma of Stump Appendicitis: An Extremely Rare Pathology - A Literature Review.pubmed.ncbi.nlm.nih.gov
- Appendicoliths, the little giants: A narrative review.pubmed.ncbi.nlm.nih.gov
- A rare clinical entity: stump appendicitis. Case report and complete review of literature.pubmed.ncbi.nlm.nih.gov
- High-volume center analysis and systematic review of stump appendicitis: solving the pending issue.pubmed.ncbi.nlm.nih.gov
- Stump appendicitis: a rare and unusual complication after appendectomy. Case report and review of the literature.pubmed.ncbi.nlm.nih.gov
- Stump Appendicitis: A 25-Year Review of Pathophysiology, Diagnosis, and Management (2000-2025).pubmed.ncbi.nlm.nih.gov
- Stump appendicitis.pubmed.ncbi.nlm.nih.gov
- Stump Appendicitis.pubmed.ncbi.nlm.nih.gov
- Recurrent stump appendicitis.pubmed.ncbi.nlm.nih.gov
- Stump Appendicitis.pubmed.ncbi.nlm.nih.gov
- A Case of Retained Viable Appendiceal Segment after Perforated Appendicitis.pubmed.ncbi.nlm.nih.gov
- Handmade loop ligation versus Hem-o-lok clip closure for appendiceal stump management in laparoscopic appendectomy: a propensity score-matched study with direct material cost analysis.pubmed.ncbi.nlm.nih.gov
- Pediatric emergency medicine point-of-care ultrasound: summary of the evidence.pubmed.ncbi.nlm.nih.gov
- Patterns of injury and violence in Yaoundé Cameroon: an analysis of hospital data.pubmed.ncbi.nlm.nih.gov
- Does laparoscopic surgery decrease the risk of atrial fibrillation after foregut surgery?pubmed.ncbi.nlm.nih.gov
- The uncertain fate of a wandering appendicolith: personal experience and literature review.pubmed.ncbi.nlm.nih.gov
- Subhepatic Appendicitis: A Systematic Review of Clinical Presentation, Diagnostic Challenges, and Surgical Management.pubmed.ncbi.nlm.nih.gov
- The Association of Polish Surgeons (APS) clinical guidelines for the use of laparoscopy in the management of abdominal emergencies. Part II.pubmed.ncbi.nlm.nih.gov
- Global practices and attitudes in acute appendicitis management: the PAMAP-W international survey and Delphi consensus study on the WSES appendicitis grading system.pubmed.ncbi.nlm.nih.gov
- Preoperative Inflammatory Markers and Sonographic Free Peritoneal Fluid in Relation to Histopathologically Confirmed Appendiceal Perforation in Children: A Retrospective Cohort Study.pubmed.ncbi.nlm.nih.gov
- A Cascade of Abscess, Fasciitis, and Obstruction: Rare Presentation of Perforated Appendicitis.pubmed.ncbi.nlm.nih.gov
- Unusual discovery of an appendiceal mucocele in case of stump appendicitis: a rare clinical presentation and diagnostic challenge.pubmed.ncbi.nlm.nih.gov
- Infarcts and ischemia in the abdomen: an imaging perspective with an emphasis on cross-sectional imaging findings.pubmed.ncbi.nlm.nih.gov
- Duodenal imaging on the spotlight: from A to Z.pubmed.ncbi.nlm.nih.gov
- Incidental Appendiceal Mucinous Neoplasm Found During Appendectomy in a 15-Year-Old Patient: A Case Report.pubmed.ncbi.nlm.nih.gov
- Twisted Troubles: A Rare Case of Intestinal Obstruction Due to Endometriosis and a Review of the Literature.pubmed.ncbi.nlm.nih.gov
- Delayed residual intra-abdominal abscess with threatened preterm labor after laparoscopic appendectomy in the second trimester.pubmed.ncbi.nlm.nih.gov
- Metastatic appendiceal mucinous adenocarcinoma presenting as bilateral ovarian masses mimicking advanced ovarian cancer: a case report.pubmed.ncbi.nlm.nih.gov
- Signet-ring cell carcinoma of the appendix presenting as diffuse uterine involvement: a case report and literature review.pubmed.ncbi.nlm.nih.gov
- Complete subserosal embedding of the appendix-cecal complex presenting as a non-visualized appendix during pediatric laparoscopic appendectomy: a case report.pubmed.ncbi.nlm.nih.gov
- Rare Appendicular Pathologies: Diagnostic Challenges, Surgical Management, and Outcomes in a Retrospective Tertiary-Center Cohort with Literature Review.pubmed.ncbi.nlm.nih.gov
- Beyond the Scope: Unmasking Appendicitis Following Colonoscopy.pubmed.ncbi.nlm.nih.gov
- SpyGlass/Cholangioscope-Assisted Colonoscopic Removal of Appendicolith as a Nonsurgical Alternative for Stump Appendicitis Management.pubmed.ncbi.nlm.nih.gov
- Case of giant appendicolith: A common ailment with a rare finding.pubmed.ncbi.nlm.nih.gov
- A Case of Low-Grade Appendiceal Mucinous Neoplasm: The Role of Preoperative Imaging and Surgical Technique in Achieving Favorable Outcomes.pubmed.ncbi.nlm.nih.gov
- Perforated acute appendicitis on computed tomography revealing underlying tuberculosis.pubmed.ncbi.nlm.nih.gov
- Perforated Subhepatic Appendicitis Mimicking Hepatobiliary Pathology: A Case Report and Narrative Literature Review.pubmed.ncbi.nlm.nih.gov
- Beyond the Appendix: Unveiling Florid Lymphoid Hyperplasia.pubmed.ncbi.nlm.nih.gov
- Clinical outcomes and optimal indications for nonoperative management of acute appendicitis in adult patients: a comprehensive literature review.pubmed.ncbi.nlm.nih.gov
- A case report of unexpected pathology within an incarcerated ventral hernia.pubmed.ncbi.nlm.nih.gov
- Invited review: Recommendations for reporting intervention studies on reproductive performance in dairy cattle: Improving design, analysis, and interpretation of research on reproduction.pubmed.ncbi.nlm.nih.gov
- Endoscopic drainage and one-stage titanium clip closure for appendiceal root abscess mimicking cecal submucosal tumor: a case report.pubmed.ncbi.nlm.nih.gov
- Acute Appendicitis With Periappendiceal Abscess Caused by Migration of an Endoscopic Clip Into the Appendix: A Case Report.pubmed.ncbi.nlm.nih.gov
- Inflammatory Metabolic Index and Metabolic-Inflammatory Stress Index as New Biomarkers for Complicated and Perforated Acute Appendicitis.pubmed.ncbi.nlm.nih.gov
- Emergence of the natural history of Myhre syndrome: 47 patients evaluated in the Massachusetts General Hospital Myhre Syndrome Clinic (2016-2023).pubmed.ncbi.nlm.nih.gov
- Cutaneous Atypical Mycobacterial Infections: A Brief Review.pubmed.ncbi.nlm.nih.gov
- Abstracts of the 16th European Congress of Paediatric and Adolescent Gynaecology † .pubmed.ncbi.nlm.nih.gov
- Horseshoe appendix: A case report and literature review.pubmed.ncbi.nlm.nih.gov
- Acute appendicitis-advances and controversies.pubmed.ncbi.nlm.nih.gov
- The Association of Coloproctology of Great Britain and Ireland consensus guidelines in emergency colorectal surgery.pubmed.ncbi.nlm.nih.gov
- Sessile serrated lesions of the appendix: a contemporary review of the literature.pubmed.ncbi.nlm.nih.gov
- A rare case of tip appendicitis treated successfully with conservative management.pubmed.ncbi.nlm.nih.gov
- Tubal Stump Ectopic Pregnancy After IVF-ET in Patients Who Underwent Salpingectomy or Adnexectomy: A Qualitative Systematic Review.pubmed.ncbi.nlm.nih.gov
- Single-incision versus conventional multi-incision laparoscopic appendicectomy for suspected uncomplicated appendicitis.pubmed.ncbi.nlm.nih.gov
- Single-incision versus conventional multi-incision laparoscopic appendicectomy for suspected uncomplicated appendicitis.pubmed.ncbi.nlm.nih.gov
- Beyond Angiography: Cardiac CT for Planning Complex PCI in Calcified Coronary Lesions.pubmed.ncbi.nlm.nih.gov
- Comparative evaluation of nerve repair and local tissue response following ReFeel<sup>®</sup> nerve cuff implantation in a rat sciatic model.pubmed.ncbi.nlm.nih.gov
- Onlay grafting with or without coronary endarterectomy maintains long-term favorable anastomotic remodeling regardless of the graft materials used.pubmed.ncbi.nlm.nih.gov
- A literature review and case report: Traumatic appendicitis in an elderly patient with spinal cord injury and medical comorbidities.pubmed.ncbi.nlm.nih.gov
- Role of magnetic resonance in bowel pathologies: Beyond inflammatory bowel disease.pubmed.ncbi.nlm.nih.gov
- Acute Appendicitis with Appendicolith and its Complication and Management: A Case Report.pubmed.ncbi.nlm.nih.gov
- Non-traumatic lower abdominal pain: ultrasonographic and clinical differential diagnosis.pubmed.ncbi.nlm.nih.gov
- Imaging of Acute Abdominopelvic Pain in Pregnancy and Puerperium-Part II: Non-Obstetric Complications.pubmed.ncbi.nlm.nih.gov
- Appendicitis mimicking the CT appearance of an appendiceal mucinous neoplasm.pubmed.ncbi.nlm.nih.gov
- Appendicitis on the Wrong Side: A Case of Left-Sided Acute Appendicitis With Intestinal Nonrotation.pubmed.ncbi.nlm.nih.gov
- Management of Cutaneous Squamous Cell Carcinoma of the Scalp: The Role of Imaging and Therapeutic Approaches.pubmed.ncbi.nlm.nih.gov
- Multidetector CT appearance of the pelvis after cesarean delivery: normal and abnormal acute findings.pubmed.ncbi.nlm.nih.gov
- Circulating Tumor DNA, Imaging, and Carcinoembryonic Antigen: Comparison of Surveillance Strategies Among Patients Who Underwent Resection of Colorectal Cancer-A Systematic Review and Meta-analysis.pubmed.ncbi.nlm.nih.gov
- NCCN Task Force report: update on the management of patients with gastrointestinal stromal tumors.pubmed.ncbi.nlm.nih.gov
- Identification of the optimal treatment strategy for complex appendicitis in the paediatric population: a protocol for a multicentre prospective cohort study (CAPP study).pubmed.ncbi.nlm.nih.gov
- WSES consensus conference: Guidelines for first-line management of intra-abdominal infections.pubmed.ncbi.nlm.nih.gov
- Appendiceal abscess: pathologic definitions and a diagnostic framework-SIRC/SICUT consensus.pubmed.ncbi.nlm.nih.gov
- Jejunal Diverticulitis With Contained Perforation and Abscess Successfully Managed With Conservative Therapy: A Case Report and Review of the Literature.pubmed.ncbi.nlm.nih.gov
- Acute abdomen secondary to perforated jejunal diverticulitis: an unusual clinical presentation - case report.pubmed.ncbi.nlm.nih.gov
- A Rare Case of Pneumatosis Cystoides Intestinalis in a Patient with Chronic Appendicitis.pubmed.ncbi.nlm.nih.gov
- Pediatric colonic diverticulitis: clinical presentation, management, and review of the literature.pubmed.ncbi.nlm.nih.gov
- Partial appendiceal duplication with double bases converging into a single body and tip: a first reported case from Nepal.pubmed.ncbi.nlm.nih.gov
- A Case of Ascending Colon Stricture Following Appendicitis with Abscess Formation.pubmed.ncbi.nlm.nih.gov
Eğitim amaçlıdır; hasta başında tanı ve tedavi kararının yerine geçmez, tıbbi tavsiye değildir. Metinler yapay zekâ desteğiyle yazıldı ve otomatik bir adımda kaynak alıntılarıyla karşılaştırıldı; bu bir tıbbi doğrulama değildir ve içerik uzman radyolog incelemesinden geçmedi. Klinik kararlarda güncel kılavuzları, kurum protokollerini ve radyoloji raporunu esas alın.