Özet
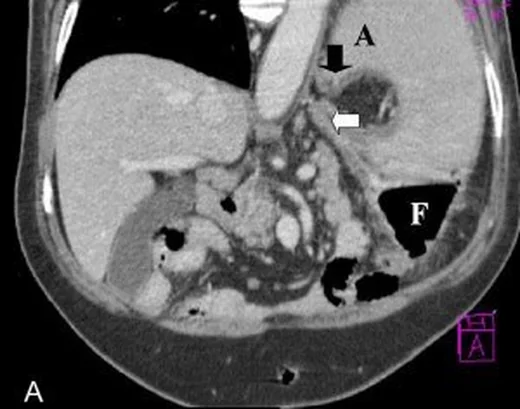
Midenin fundusu, gövdesi ve antropilorik bileşkesi doluluk, diyafram konturu ve destek bağlarının gevşekliğine göre farklı konumlarda görülebilir; bu görünüm tek başına hastalık ya da torsiyon anlamına gelmez. BT'de hiatus düzlemi, gastroözofageal bileşke (GEJ), fundus ve pilorun birbirine göre konumu; intratorasik mide, paraözofageal herni veya organoaksiyel/mezenterikoaksiyel volvulusu ayırt etmeye yardım eder. Özellikle GEJ'nin yerini fundusun yerinden ayrı tarif etmek, kayan hiatus hernisini paraözofageal herniden ayırır. Pozisyon farkını torsiyon sanmak gereksiz acil yorum doğurabilir; gerçek volvulustaki obstrüksiyon ve iskemi işaretlerini kaçırmak ise mide duvarı hasarının geç fark edilmesine yol açar.
Faz ve pencere
- Kontrastsız tanısal
- Midenin anatomik konumu ve ekseni, lümen içeriğiyle BT'de izlenebilir; ancak duvar kalınlığı, kanlanma ve iskemi bulgularını değerlendirmek için kontrastlı BT gereklidir. Torsiyon kuşkusu varsa lümen distansiyonu, antropilorik geçiş noktası, perigastrik sıvı ve duvar kalınlığı bu anatomik harita üzerinde değerlendirilir.
Önerilen pencereler G genişlik, M merkez; değerler Hounsfield birimi (HU)
- BatınG 400 / M +50
- Yumuşak dokuG 400 / M +40
BT bulguları
- Kardiya GEJ'yi çevreler; fundus, GEJ'ye teğet çizginin üstündeki mide bölümüdür.
- GEJ hiatus altında kalırken fundusun özofagus yanında toraksa yükselmesi (paraözofageal bileşen)
- Kayan hiatus hernisinde kardiya ve GEJ toraksa geçebilir.
- İntratorasik mide kesiminin büyüklüğü, ekseni ve kardiya-antrum-pilor devamlılığının koronal/sagittal planda izlenmesi
- Organoaksiyel torsiyonda büyük kurvatur küçük kurvaturun üstüne ve sağına geçebilir; fundus posteroinferiora, antrum anterosuperiora yer değiştirebilir.
- Mezenterikoaksiyel torsiyonda antropilorik bileşkenin GEJ'nin üstüne taşınması ve mide çıkışında daralma
- Volvulus lehine herni boynunda stenoz ve pilor düzeyinde geçiş noktasıdır.
- Mide duvarında kontrastlanmanın azalması, pnömatozis veya ekstraluminal gaz ya da sıvı iskemiyle ilişkili BT bulguları olabilir; duvar kalınlaşması ve perigastrik sıvı eşlik edebilir.
Ölçütler ve sınıflamalar
- Hiatus hernisi anatomik tipleri
- Tip I, kayan (sliding) hiatus hernisi olarak adlandırılır. Tip II: fundus hiatusa yükselir, GEJ yerinde kalır. Tip III: GEJ ile fundus birlikte toraksa çıkar. Tip IV: mideye ek başka karın organları herni kesesine girer.
- Gastrik volvulus eksen sınıflaması
- Organoaksiyel: dönüş uzun eksen çevresindedir ve büyük kurvatur küçük kurvaturun üstüne/sağına geçer. Mezenterikoaksiyel: kısa eksen çevresinde dönüşte antropilorik bileşke GEJ'nin üstüne çıkar. Kombine tipte iki yönün bulguları birlikte görülür.
Normalde
Normal anatomide pilor, GEJ'nin anteroinferiorunda yer alır. Aynı koronal-sagittal düzlemlerde GEJ ile fundusu ayrı işaretle, antropilorik bileşkenin GEJ'ye göre yüksekliğini ve büyük-küçük kurvatur yönünü kıyasla; yalnız farklı mide şekli veya yönelimi obstrüksiyon demek değildir.
Normal BT ile kıyasla
Aynı bölgenin, kaynak veri setinde patoloji içermediği belirtilen bir BT incelemesini kesit kesit kaydırın; organ sınırlarını açarak anatomiyi hasta görüntüsüyle karşılaştırın. Küçük rastlantısal bulgular tümüyle dışlanmamıştır.
Kaynak: TotalSegmentator v2.01 veri seti (Wasserthal ve ark., Radiology: Artificial Intelligence 2023), CC BY 4.0, vaka s0541; organ sınırları veri setinin otomatik segmentasyonundan, birleştirilerek sadeleştirildi. Görüntüler 2,5 mm kesit aralığına yeniden örneklendi.
Ayırıcı tanı
- Gastrik volvulus
- kurvaturların ters ilişkisi veya antropilorik bileşkenin GEJ üstüne geçmesine ek olarak geçiş noktası, lümen tıkanması ya da herni boynu daralması görülür.
- Kayan hiatus hernisi, tip I (sliding) hiatus hernisi olarak adlandırılır.
- Paraözofageal herni
- fundus özofagus yanında hiatus üstüne geçerken GEJ abdominal konumunu korur; büyük hernide mide ekseni de değişebilir.
- Diyafram eventrasyonu, diyaframın anatomik bir anormalliğidir.
- Konjenital diyafram hernisi
- mide ya da diğer karın organları diyaframdaki gerçek defektten toraksa uzanır; defekt yeri hiatusla sınırlı değildir.
- Situs inversus
- mide ve dalak sağda, karaciğerin bir bölümü solda olabilir; değişiklik yalnız mide ekseniyle sınırlı kalmayıp çoklu organ yerleşimlerini içerir.
Tuzaklar
- Supin pozisyonda fundus midenin en bağımlı bölümüdür; GEJ ve pilorun konumunu da birlikte değerlendir.
- Hiatus üstündeki mide segmenti tek başına kayan herniyi göstermez; paraözofageal hernide mide özofagus yanında yükselirken GEJ karında kalabilir.
- Büyük hiatus hernisi volvulus için yatkınlık yaratır, fakat herni içindeki mide eksen değişikliği tek başına akut torsiyon kanıtı değildir.
- Tek aksiyel kesit mide eksenini yanıltabilir; kardiya, fundus, antrum ve piloru koronal-sagittal rekonstrüksiyonlarla kesintisiz izle.
- Kurvaturların yer değiştirmesi veya antropilorik bileşkenin GEJ’ye göre yüksek konumu tek başına yeterli değildir; volvulus değerlendirmesinde herni boynunda stenoz ve pilorda geçiş noktası gibi BT bulgularını da ara.
Kendini dene
Fundus toraksta, özofagusun yanında; GEJ diyafram altında ve mide çıkışı açık. En uygun tanım hangisidir?
Cevabı göster
Paraözofageal herni. Fundusun özofagus yanında yükselip GEJ'nin abdominal konumda kalması paraözofageal herniyle uyumludur. Akut volvulusta eksen bozulmasıyla birlikte tıkanma işaretleri beklenir; eventrasyonda diyafram süreklidir; situs inversusta diğer organların yerleşimi de ters döner.
Büyük kurvatur küçük kurvaturun üstüne ve sağına geçmiş, mide belirgin distandü ve pilor düzeyinde obstrüksiyon geçiş noktası görülüyor. Öncelikle hangi durum düşünülmelidir?
Cevabı göster
Organoaksiyel volvulus. Kurvaturların organoaksiyel volvulusa uygun ters ilişkisine pilor düzeyinde geçiş noktası ve distansiyon eşlik etmesi mekanik çıkış tıkanmasını destekler. Büyük kurvaturun küçük kurvaturun üstüne ve sağına geçmesi organoaksiyel volvulusla uyumludur; pilor düzeyindeki geçiş noktası mide çıkış tıkanmasını destekler.
Kaynaklar
Bu sayfadaki 50 cümle ve 2 quiz sorusu aşağıdaki kaynaklardan alıntılarla otomatik olarak karşılaştırıldı; 16 cümle bu karşılaştırmada düzeltildi (2026-10-09).
- Multimodality imaging of adult gastric emergencies: A pictorial reviewpmc.ncbi.nlm.nih.gov
- Hereditary chronic intestinal pseudo-obstruction caused by a rare MYH11 mutation: A case reportpmc.ncbi.nlm.nih.gov
- Obesity and Cardiovascular Disease: An Obesity Medicine Association (OMA) Clinical Practice Statement (CPS) 2026pmc.ncbi.nlm.nih.gov
- Abstracts - IANCON 2025pmc.ncbi.nlm.nih.gov
- Proceedings of the 33rd European Paediatric Rheumatology Congresspmc.ncbi.nlm.nih.gov
- Acute gastric volvulus following rapid and incomplete chewing of vegetables: A case report.pubmed.ncbi.nlm.nih.gov
- Body mass index should be considered as an indicator for laparoscopic surgery or robot-assisted surgery selection in patients with hiatal hernia.pubmed.ncbi.nlm.nih.gov
- Mesenteroaxial Gastric Volvulus: A Case Report.pubmed.ncbi.nlm.nih.gov
- A Massive Type IV Hiatal Hernia With Gastric Volvulus and the Complicated Road to Recovery.pubmed.ncbi.nlm.nih.gov
- Acute Esophageal Necrosis Secondary to Gastric Volvulus Presenting With Massive Aspiration of Upper Gastrointestinal Contents: A Case Report.pubmed.ncbi.nlm.nih.gov
- A Rare Complication of Gastric Volvulus in Infectious Mononucleosis: A Case Report.pubmed.ncbi.nlm.nih.gov
- Robotic Surgical Repair of a Parahiatal Hernia: A Case Report.pubmed.ncbi.nlm.nih.gov
- Grade IV hiatal hernia in a neonate: A radiologic mimic of congenital diaphragmatic hernia.pubmed.ncbi.nlm.nih.gov
- Patterns of injury and violence in Yaoundé Cameroon: an analysis of hospital data.pubmed.ncbi.nlm.nih.gov
- Sleeve gastrectomy for acute gastric volvulus: a salvage surgery.pubmed.ncbi.nlm.nih.gov
- Sigmoid Volvulus in a Young Adult With Cerebral Palsy: A Case Managed by the Paul-Mikulicz Procedure.pubmed.ncbi.nlm.nih.gov
- Delayed Traumatic Diaphragmatic Hernia Presenting With Gastric Volvulus and Necrosis: A Case Report and Literature Review.pubmed.ncbi.nlm.nih.gov
- Acute Gastric Necrosis Secondary to Mesenteric Ischemia: A Case Report and Literature Review.pubmed.ncbi.nlm.nih.gov
- Gastric Ischemia Secondary to Abdominal Distension.pubmed.ncbi.nlm.nih.gov
- Multimodality imaging of adult gastric emergencies: A pictorial review.pubmed.ncbi.nlm.nih.gov
- Two Hernias, One Patient: A Case of Organoaxial Gastric Volvulus in a Paraesophageal Hernia With an Incisional Hernia.pubmed.ncbi.nlm.nih.gov
- Association Between Large Hernia Size and Severe Postoperative Complications After Type III/IV Hiatal Hernia Repair.pubmed.ncbi.nlm.nih.gov
- Giant Paraesophageal Hernia Presenting With Dyspnea: A Case Report With Surgical Considerations.pubmed.ncbi.nlm.nih.gov
- Laparoscopic Management of a Strangulated Hiatal Hernia: A Case Report.pubmed.ncbi.nlm.nih.gov
- The management of recurrent hiatal hernia: a single-center retrospective study.pubmed.ncbi.nlm.nih.gov
- A Comparative Assessment of the Diagnosis of Swallowing Impairment and Gastroesophageal Reflux in Canines and Humans.pubmed.ncbi.nlm.nih.gov
- Intrathoracic major duodenal papilla with transhiatal herniation of the pancreas and duodenum: A case report and review of the literature.pubmed.ncbi.nlm.nih.gov
- Association Between Thoracic Kyphosis and Hiatal Enlargement: A CT-Based Study Interpreted in Light of GERD-Linked Morphological Markers.pubmed.ncbi.nlm.nih.gov
- A case report of type II Floyd tracheal agenesis with staged tracheal and alimentary reconstructions.pubmed.ncbi.nlm.nih.gov
- TACE combined with DynaCT-guided MWA in the treatment of high-risk location liver cancers with ≤5 cm tumor size.pubmed.ncbi.nlm.nih.gov
- An Adult Case of Gastric Volvulus Associated With Wandering Spleen: A Case Report.pubmed.ncbi.nlm.nih.gov
- Organoaxial gastric volvulus: a rare cause of an acute abdomen.pubmed.ncbi.nlm.nih.gov
- Successful laparoscopic management of paraesophageal hiatal hernia with upside-down intrathoracic stomach: a case report.pubmed.ncbi.nlm.nih.gov
- Gastric Volvulus, Pancreatic Volvulus, and Wandering Spleen: A Rare Emergency Triad Behind Acute Abdomen.pubmed.ncbi.nlm.nih.gov
- A Case of Complicated Hiatus Hernia Rupture Causing Tension Hydropneumothorax.pubmed.ncbi.nlm.nih.gov
- Left paraduodenal hernia: a rare cause of gastric outlet obstruction and large bowel obstruction.pubmed.ncbi.nlm.nih.gov
- Emphysematous conditions of the abdomen and pelvis: pearls and pitfalls.pubmed.ncbi.nlm.nih.gov
- Gastrointestinal perforation: clinical and MDCT clues for identification of aetiology.pubmed.ncbi.nlm.nih.gov
- Gastric outlet obstruction in uncomplicated mesentero-axial gastric volvulus associated to hiatal hernia.pubmed.ncbi.nlm.nih.gov
- Surgical Anatomy of Paraesophageal Hernias.pubmed.ncbi.nlm.nih.gov
- A Rare Case of Gastric Volvulus Post Laparoscopic Gastric Greater Curvature Plication.pubmed.ncbi.nlm.nih.gov
- Imaging Characteristics of Pylorogastric, Duodenogastric, and True-Gastrogastric Intussusception in 25 Dogs and One Cat.pubmed.ncbi.nlm.nih.gov
- Role of Endoscopic Ultrasonography in Management of Pancreaticobiliary Cancers: Recent Trends and Advances.pubmed.ncbi.nlm.nih.gov
- Thoracic and Abdominal Radiologic Anatomy of the Greater Cane Rat (<i>Thryonomys swinderianus</i>).pubmed.ncbi.nlm.nih.gov
- Cameron Lesions: Endoscopic Characteristics, Clinical Profile, and Therapeutic Implications-A Retrospective Study of 43 Patients.pubmed.ncbi.nlm.nih.gov
- Sliding hiatal hernia detected by transnasal esophagogastroscopy is associated with poorer treatment response in reflux-associated globus sensation.pubmed.ncbi.nlm.nih.gov
- Preoperative Hill grade versus hiatal hernia size: which drives the decision for Dor fundoplication during sleeve gastrectomy? A retrospective cohort study.pubmed.ncbi.nlm.nih.gov
- Spontaneous Acute Mesenteroaxial Gastric Volvulus Diagnosed by Computed Tomography Scan in a Young Man.pubmed.ncbi.nlm.nih.gov
- Twist in the cecum: A case series of mobile cecum, cecal volvulus and cecal bascule.pubmed.ncbi.nlm.nih.gov
- When Nausea and Vomiting Are Something Else Entirely, It's Not Gastroparesis: A Report of Two Cases.pubmed.ncbi.nlm.nih.gov
- A Misplaced Pocket of Air: Intramural Gastric Air Most Consistent With Gastric Emphysema.pubmed.ncbi.nlm.nih.gov
- The Fundoplication Revision of a Recurrent Large Paraesophageal Hiatal Hernia in a 63-Year-Old Female.pubmed.ncbi.nlm.nih.gov
- Prenatal ultrasound diagnosis of a rare morgagni hernia: a case report.pubmed.ncbi.nlm.nih.gov
- The Perception of the Diaphragm with Ultrasound: Always There Yet Overlooked?pubmed.ncbi.nlm.nih.gov
- Does laparoscopic surgery decrease the risk of atrial fibrillation after foregut surgery?pubmed.ncbi.nlm.nih.gov
- Tension Gastrothorax in a Child With Undiagnosed Congenital Diaphragmatic Hernia: A Case Report and Proposed Emergency Management Algorithm.pubmed.ncbi.nlm.nih.gov
- Adaptability of minimally invasive thoracoscopic repair for congenital diaphragmatic hernia: a neonatal case report from a low-income country.pubmed.ncbi.nlm.nih.gov
- Congenital Diaphragm Defect in a Neonatal Southern White Rhinocerus (Ceratotherium simum simum).pubmed.ncbi.nlm.nih.gov
- Laparoscopic Distal Gastrectomy Using Multimodal Visualization in a Patient with Situs Inversus Totalis and a Duplicated Portal Vein: A Case Report.pubmed.ncbi.nlm.nih.gov
- Malignancy in mirror image anatomy reveals situs inversus totalis as an anatomic modifier of oncologic care.pubmed.ncbi.nlm.nih.gov
- Pancreatic cancer in situs inversus totalis: case presentation and literature review.pubmed.ncbi.nlm.nih.gov
- The value of "diaphragmatic relaxing incision" for the durability of the crural repair in patients with paraesophageal hernia: a double blind randomized clinical trial.pubmed.ncbi.nlm.nih.gov
- Prevalence of Abnormalities at Tandem Endoscopy in Patients Referred for Colorectal Cancer Screening/Surveillance Colonoscopy.pubmed.ncbi.nlm.nih.gov
- Successful surgical management of pancreatic torsion in a 3-month-old Bernese Mountain dog without evidence of long-term pancreatic dysfunction.pubmed.ncbi.nlm.nih.gov
- Effect of the COVID-19 pandemic on CT scans ordered from the emergency department for abdominal complaints.pubmed.ncbi.nlm.nih.gov
- Preoperative measurement of the hiatal surface with MDCT: impact on surgical planning.pubmed.ncbi.nlm.nih.gov
- Staging laparoscopy in esophagogastric junction cancer: Systematic review and meta-analysis.pubmed.ncbi.nlm.nih.gov
- Endoscopic Advances in the Diagnosis and Management of Gastroesophageal Reflux Disease.pubmed.ncbi.nlm.nih.gov
- Risk factors predisposing to cardia gastric adenocarcinoma: Insights and new perspectives.pubmed.ncbi.nlm.nih.gov
- An Interesting Case of Recurrent Postprandial Cardiogenic Syncope Caused by Type III Hiatal Hernia.pubmed.ncbi.nlm.nih.gov
- Paraesophageal Hernia in a Newborn Mimicking Esophageal Atresia.pubmed.ncbi.nlm.nih.gov
- Magnetic sphincter augmentation (MSA) in patients with hiatal hernia: clinical outcome and patterns of recurrence.pubmed.ncbi.nlm.nih.gov
- Routine Orogastric Tube Placement Reveals an Unexpected Diagnosis Resulting in a Change in Therapy: A Case Report.pubmed.ncbi.nlm.nih.gov
- Twist in the Bowel: A Multimodality Radiological Imaging Spectrum.pubmed.ncbi.nlm.nih.gov
- Concurrent occurrence of a wandering spleen, organoaxial gastric volvulus, pancreatic volvulus, and cholestasis - A rare cause of an acute abdomen.pubmed.ncbi.nlm.nih.gov
- CT of Gastric Volvulus: Interobserver Reliability, Radiologists' Accuracy, and Imaging Findings.pubmed.ncbi.nlm.nih.gov
- The "ABCD" framework for assessment: a task-oriented approach to reconcile multimodal diagnostic discordance.pubmed.ncbi.nlm.nih.gov
- Hereditary chronic intestinal pseudo-obstruction caused by a rare <i>MYH11</i> mutation: A case report.pubmed.ncbi.nlm.nih.gov
- From Pixels to Stroma: AI-Driven Spatial Profiling of Cancer-Associated Fibroblasts on H&E and Its Implications for Immunotherapy.pubmed.ncbi.nlm.nih.gov
- Obesity and Cardiovascular Disease: An Obesity Medicine Association (OMA) Clinical Practice Statement (CPS) 2026.pubmed.ncbi.nlm.nih.gov
- Fetal MRI findings in conjoined twin pregnancies.pubmed.ncbi.nlm.nih.gov
- Congenital Diaphragmatic Eventration in the Neonatal Period: Systematic Review of the Literature and Report of a Rare Case Presenting with Gastrointestinal Disorders.pubmed.ncbi.nlm.nih.gov
- Congenital mixed hiatal hernia: A case report of an atypical cause of neonatal vomiting.pubmed.ncbi.nlm.nih.gov
- Diagnostic value of real-time dynamic gastric contrast ultrasound for hiatal hernia.pubmed.ncbi.nlm.nih.gov
- Morphology of the Esophageal Hiatus: Is It Different in 3 Types of Hiatus Hernias?pubmed.ncbi.nlm.nih.gov
- Imaging of pediatric gastrostomy tube malposition: Pearls and pitfalls.pubmed.ncbi.nlm.nih.gov
- Imaging following bariatric surgery: roux-en-Y gastric bypass, laparoscopic adjustable gastric banding and sleeve gastrectomy.pubmed.ncbi.nlm.nih.gov
- Spontaneous onset and resolution of gastroesophageal intussusception during contrast-enhanced computed tomography.pubmed.ncbi.nlm.nih.gov
- Nomographic predictive models for complications after minimally invasive esophagectomy: Current status and future perspectives.pubmed.ncbi.nlm.nih.gov
- Analysis of computed tomographic findings according to gastroesophageal flap valve grade.pubmed.ncbi.nlm.nih.gov
- Standardized W-H fundoplication procedure for gastroesophageal reflux disease (2026).pubmed.ncbi.nlm.nih.gov
- Laparoscopic Fundoplication Using the Excluded Stomach Versus Conversion to Roux-en-Y Gastric Bypass for Refractory Reflux After One-Anastomosis Gastric Bypass: A Retrospective Comparative Analysis of Safety and 1-Year Outcomes.pubmed.ncbi.nlm.nih.gov
- Restoration of normal anatomy without fundoplication in non-elective incarcerated giant paraesophageal hernia repair.pubmed.ncbi.nlm.nih.gov
- Laparoscopic repair of a primary parahiatal hernia combined with gastric volvulus: a case report and literature review.pubmed.ncbi.nlm.nih.gov
- Removal of the sac during surgery for the repair of "giant" paraesophageal hernias.pubmed.ncbi.nlm.nih.gov
- Gastric Fundus Obstruction From Hiatal Hernia After Sleeve Gastrectomy: A Case Report.pubmed.ncbi.nlm.nih.gov
- Sliding hiatus hernia (intrathoracic sleeve migration) post-laparoscopic sleeve gastrectomy: A case series and review of literature.pubmed.ncbi.nlm.nih.gov
- Robotic Repair of a Paraesophageal Hernia After an Open Nissen Fundoplication: Case Presentation and Clinical Discussion.pubmed.ncbi.nlm.nih.gov
- Hiatal hernia with gastric volvulus and perforation: a rare complicated entity.pubmed.ncbi.nlm.nih.gov
- Multifactorial late complications 13 years after conversion to Roux-en-Y gastric bypass: a case report.pubmed.ncbi.nlm.nih.gov
- Transverse colon incarceration and necrosis in a hiatal hernia: a case report.pubmed.ncbi.nlm.nih.gov
- The Wandering Pancreas: A Rare Case of Complex Hiatal Hernia Presenting With Thoracic Symptoms.pubmed.ncbi.nlm.nih.gov
- CT Findings of Obstructed Hiatal Hernia and Correlation with Clinical Outcomes.pubmed.ncbi.nlm.nih.gov
Eğitim amaçlıdır; hasta başında tanı ve tedavi kararının yerine geçmez, tıbbi tavsiye değildir. Metinler yapay zekâ desteğiyle yazıldı ve otomatik bir adımda kaynak alıntılarıyla karşılaştırıldı; bu bir tıbbi doğrulama değildir ve içerik uzman radyolog incelemesinden geçmedi. Klinik kararlarda güncel kılavuzları, kurum protokollerini ve radyoloji raporunu esas alın.