Özet
Allojenik hematopoietik kök hücre nakli sonrası ishal ve karın ağrısı olan hastada gastrointestinal graft-versus-host hastalığı (GVHH), enfeksiyon ve ilaç toksisitesiyle örtüşen bir olasılıktır. İntravenöz kontrastlı BT, ince bağırsak duvarı, mukozal kontrastlanma, mezenter ve eşlik eden organ bulgularını birlikte değerlendirir; tek başına GVHH tanısını koydurmaz. Yaygın tutulum ve hedef görünümü inflamasyonu destekleyebilir, fakat histoloji ve klinik bağlam gerekir. Pnömatozis, azalan duvar kontrastlanması veya ekstraluminal hava ileri komplikasyonlara işaret eder ve acil değerlendirme gerektirir.
Faz ve pencere
- Portal tanısal
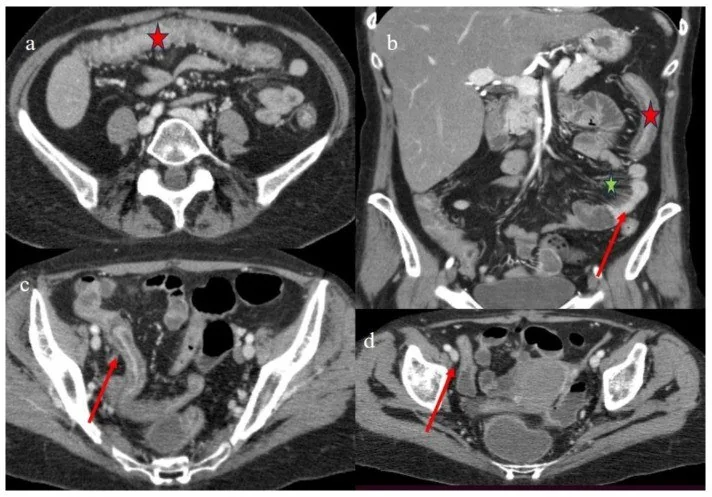
- İntravenöz kontrast sonrası ince barsak mukozasının belirgin kontrastlanması, submukozal ödemin düşük atenüasyonlu halka oluşturduğu hedef/halo görünümü, segmental ya da yaygın duvar kalınlaşması ve lümende sıvı izlenebilir. Mezenterik ödem, serbest sıvı ve nadiren intramural gaz eşlik edebilir; bu bulgular GVHH'ye özgü değildir.
Önerilen pencereler: Batın (G 400 / M 50), Yumuşak doku (G 400 / M 40).
BT bulguları
- Duvar kalınlaşması — yeterince distandü ince barsak duvarının 3 mm'den kalın ölçülmesi kalınlaşma kabul edilir; bu genel ölçüt GVHH'ye özgü değildir.
- Hedef/halo görünümü — kontrastlanan mukoza ve seroza arasında ödemli, daha düşük atenüasyonlu submukoza seçilir.
- Anormal mukozal kontrastlanma — kalınlaşmış segmentlerde mukoza, komşu normal anslara göre daha belirgin kontrastlanabilir.
- Çok segmentli tutulum — jejunum ve ileumda atlamalı veya yaygın duvar değişiklikleri görülebilir; kolon tutulumu eşlik edebilir.
- Sıvı ile genişlemiş anslar — lümende sıvı artışı ve kalibrasyon genişlemesi gelişebilir, ancak her GVHH olgusunda bulunmaz.
- Mezenterik reaksiyon — tutulu anslar çevresinde yağ planlarında bulanıklık, damar belirginliği veya az miktarda serbest sıvı görülebilir.
- Bağırsak dışı eşlikçiler — periportal ödem, safra kesesi duvar kontrastlanması veya splenomegali sistemik nakil komplikasyonları bağlamında eşlik edebilir; hiçbiri tek başına tanı koydurmaz.
- Pnömatozis, azalan duvar kontrastlanması veya ekstraluminal hava ileri komplikasyonlara işaret eder ve acil değerlendirme gerektirir.
Ölçütler ve sınıflamalar
- Distandü ince barsakta genel duvar kalınlaşması ölçütü
- >3 mm
- Diffüz bağırsak duvarı kalınlaşmasının genel uzunluk sınıfı
- Yaygın ince barsak tutulumu kötü prognozla ilişkilidir; belirli bir uzunluk ölçüsü tanı eşiği oluşturmaz.
Normalde
Normal, yeterince distandü ince barsakta duvar incedir; jejunal kıvrımlar düzenli uzanır ve mukoza-submukoza-seroza arasında belirgin ödem halkası oluşmaz. Tutulumun yerini ve yaygınlığını, duvar kalınlığının derecesi ve örüntüsüyle birlikte mezenterik yağ değişikliklerini değerlendirerek inceleyin.
Normal BT ile kıyasla
Aynı bölgenin, kaynak veri setinde patoloji içermediği belirtilen bir BT incelemesini kesit kesit kaydırın; organ sınırlarını açarak anatomiyi hasta görüntüsüyle karşılaştırın. Küçük rastlantısal bulgular tümüyle dışlanmamıştır.
Kaynak: TotalSegmentator v2.01 veri seti (Wasserthal ve ark., Radiology: Artificial Intelligence 2023), CC BY 4.0, vaka s0119; organ sınırları veri setinin otomatik segmentasyonundan, birleştirilerek sadeleştirildi. Görüntüler 2,5 mm kesit aralığına yeniden örneklendi.
Ayırıcı tanı
- Enfeksiyöz enterit
- benzer hedef görünümü yapabilir; patojen, dışkı testleri ve dağılım klinik korelasyonla ayrımı destekler.
- Nötropenik enterokolit (tifilit)
- çekum ve çıkan kolon ağırlıklı tutulum, nötropeni ve sağ alt kadran çevre inflamasyonu öne çıkar.
- CMV enterokoliti
- immün baskılanmış hastalarda benzer BT bulguları oluşturabilir; enfeksiyon kaynakları ve klinik bağlam ayrım için kritiktir.
- İlaç veya radyasyon enteriti
- tedavi alanıyla uyumlu dağılım ve maruziyet öyküsü ayrımda önemlidir.
- Damar anomalileri (vasa recta dolgunluğu) enfeksiyon ve iskemi ile çakışabilir; klinik bağlam ve laboratuvar bulguları ayırıcı tanıyı yönlendirir.
Tuzaklar
- Hedef görünümü inflamasyonu gösterir, GVHH'yi kanıtlamaz; enfeksiyon ve ilaç ilişkili enterit aynı katmanlı kontrastlanmayı oluşturabilir.
- Kollabe ansın duvarı yalancı kalın görünür; ölçümü lümeni açık ve enine kesiti dik olan segmentte yapın.
- Nötropenik hastada terminal ileum/çekum baskın inflamasyonu GVHH olarak etiketlemek tifiliti gözden kaçırabilir.
- Akut gastrointestinal semptomlar nedeniyle ağızdan kontrast materyali genellikle uygulanamaz veya önerilmez; bu durum mukozal kontrastlanmanın görselleştirilmesini kısıtlar.
Kendini dene
Allojenik nakil sonrası ishalde jejunum ve ileumda mukozal parlaklıkla çevrili düşük atenüasyonlu duvar halkaları görülüyor. En uygun yorum hangisidir?
Cevabı göster
Gastrointestinal GVHH. Nakil bağlamı ve çok segmentli ince barsak hedef görünümü gastrointestinal GVHH'yi destekler, ancak BT özgül değildir. Nötropenik enterokolit, hastaların %75-100'ünde sağ kolon veya çekum tutulumu gösterir ve bu durum GVHH ile ayırım yapmada kritik bir özelliktir.
Aynı hastada sağ alt kadranda çekum ağırlıklı belirgin kalınlaşma ve nötropeni var. Hangi taklitçi öne çıkar?
Cevabı göster
Nötropenik enterokolit. Nötropeni ile çekum ve sağ kolon ağırlıklı inflamasyon tifilit için tipiktir. Sağ kolon veya çekum ağırlıklı tutulum, nötropeni varlığında tanısal olarak nötropeenik enterokoliti (tiflit) akla getirmeli ve GVHH gibi diğer nedenlerden ayırmalıdır.
Kaynaklar
Bu sayfadaki 41 cümle ve 2 quiz sorusu aşağıdaki kaynaklardan alıntılarla tek tek karşılaştırıldı; 14 cümle bu karşılaştırmada düzeltildi (2026-10-08).
- New Insight for the Diagnosis of Gastrointestinal Acute Graft-versus-Host Diseasepmc.ncbi.nlm.nih.gov
- Endoscopic findings in patients with Shwachman–Diamond syndrome: A report from the North American Shwachman–Diamond syndrome registrypmc.ncbi.nlm.nih.gov
- Bedside Ultrasound Versus Computed Tomography in Adult Neutropenic Patients with Acute Abdominal Symptoms: A Comparative Studypmc.ncbi.nlm.nih.gov
- Apoptotic Colitis in a Liver Transplant Recipient: A Case of Solid Organ Transplant-Associated Graft-Versus-Host Diseasepmc.ncbi.nlm.nih.gov
- Clinical translation of an immunomodulatory cell therapy that is designed to convert “cold” tumors to “hot”: A phase 2B trial in 3L MSS/pMMR metastatic colorectal cancerpmc.ncbi.nlm.nih.gov
- Gastrointestinal Manifestations of Immunodeficiency: Imaging Spectrum.pubmed.ncbi.nlm.nih.gov
- [Radiological imaging of acute infectious and non-infectious enterocolitis].pubmed.ncbi.nlm.nih.gov
- Biopsy-Induced Duodenal Hematoma Is Not an Infrequent Complication Favored by Bone Marrow Transplantation.pubmed.ncbi.nlm.nih.gov
- Gastrointestinal Perforations in Adult Whole-Liver Transplant Patients: Clinical, Radiologic, and Histopathologic Analysis.pubmed.ncbi.nlm.nih.gov
- CT-analysis of the course of gastrointestinal graft-versus-host disease--patterns of involvement.pubmed.ncbi.nlm.nih.gov
- Graft-versus-host disease complicated with small bowel obstruction in children: A case report.pubmed.ncbi.nlm.nih.gov
- CT in the clinical and prognostic evaluation of acute graft-vs-host disease of the gastrointestinal tract.pubmed.ncbi.nlm.nih.gov
- Encapsulating peritoneal sclerosis in a patient after allogeneic hematopoietic stem cell transplantation: a case report.pubmed.ncbi.nlm.nih.gov
- Computed tomography imaging of acute gastrointestinal graft-versus-host disease after haematopoietic stem cell transplantation in children.pubmed.ncbi.nlm.nih.gov
- Hepatic portal venous gas associated with severe graft-versus-host disease of the gastrointestinal tract.pubmed.ncbi.nlm.nih.gov
- [Pancreas-preserving duodenectomy in acute situations. Surgical treatment of an iatrogenic hemorrhage in the duodenal wall].pubmed.ncbi.nlm.nih.gov
- Pneumatosis cystoides interstitialis: A complication of graft-versus-host disease. A report of two cases.pubmed.ncbi.nlm.nih.gov
- Early and late-onset acute GvHD following hematopoietic cell transplantation: CT features of gastrointestinal involvement with clinical and pathological correlation.pubmed.ncbi.nlm.nih.gov
- Intestinal and Extraintestinal Findings of Graft-versus-Host Disease on CT: A Case Series with Radiological and Histopathological Correlations.pubmed.ncbi.nlm.nih.gov
- Extranodal Nasal Type NK/T-Cell Lymphoma of the Transverse Colon With Gastrointestinal Perforation in a 15-Year-Old: Durable Remission With Modified SMILE Chemotherapy and HSCT.pubmed.ncbi.nlm.nih.gov
- An Unusual Presentation of Philadelphia Chromosome Positive B-Cell Acute Lymphoblastic Leukemia With Isolated Osteolytic Lesions at Diagnosis: A Case Report.pubmed.ncbi.nlm.nih.gov
- Adenovirus Infections in Hematologic Malignancy and Hematopoietic Cell Transplant Recipients: Epidemiology, Diagnosis, and Management.pubmed.ncbi.nlm.nih.gov
- Pneumatosis intestinalis revisited: associated imaging findings, clinical correlation, management, risk stratification and future perspectives.pubmed.ncbi.nlm.nih.gov
- Severe Lupus Enteritis in a Regional Hospital: An Uncommon Presentation of the Acute Surgical Abdomen.pubmed.ncbi.nlm.nih.gov
- A Rare Manifestation of Abdominal Pain in Systemic Lupus Erythematosus: A Case Report on Lupus Enterocolitis.pubmed.ncbi.nlm.nih.gov
- Clinical Predictors and Outcomes for Recurrent Pneumatosis Intestinalis in Children: A Case Control Study.pubmed.ncbi.nlm.nih.gov
- Large Bowel Ischemia/Infarction: How to Recognize It and Make Differential Diagnosis? A Review.pubmed.ncbi.nlm.nih.gov
- Pneumatosis Intestinalis Presenting as Small Bowel Obstruction without Bowel Ischemia after Mechanical Ventilation.pubmed.ncbi.nlm.nih.gov
- Role of magnetic resonance in bowel pathologies: Beyond inflammatory bowel disease.pubmed.ncbi.nlm.nih.gov
- Clinical and CT features of patients with pneumatosis intestinalis: A retrospective single-center study.pubmed.ncbi.nlm.nih.gov
- Venous congestive ischemic colitis following left hemicolectomy: A rare case of superior rectal vein occlusion.pubmed.ncbi.nlm.nih.gov
- The Importance of Magnetic Resonance Enterography in Monitoring Inflammatory Bowel Disease: A Review of Clinical Significance and Current Challenges.pubmed.ncbi.nlm.nih.gov
- Evaluating luminal and post-operative Crohn's disease activity on magnetic resonance enterography: A review of radiological disease activity scores.pubmed.ncbi.nlm.nih.gov
- Beyond Fixed Thresholds: Cluster-Derived MRI Boundaries Improve Assessment of Crohn's Disease Activity.pubmed.ncbi.nlm.nih.gov
- Fontan-associated liver disease in children following surgical correction of congenital heart defects.pubmed.ncbi.nlm.nih.gov
- Ultrasound Evaluation of Fontan-Associated Liver Disease: A State-of-the-Art Review.pubmed.ncbi.nlm.nih.gov
- Infarcts and ischemia in the abdomen: an imaging perspective with an emphasis on cross-sectional imaging findings.pubmed.ncbi.nlm.nih.gov
- Probable everolimus-associated severe colitis with hematochezia in a patient with metastatic hormone receptor-positive, HER2-negative breast cancer: a case report.pubmed.ncbi.nlm.nih.gov
- Medical emergencies in pediatric blood & marrow transplant and cellular therapies.pubmed.ncbi.nlm.nih.gov
- Ileocecal thickening: Clinical approach to a common problem.pubmed.ncbi.nlm.nih.gov
- Apoptotic Colitis in a Liver Transplant Recipient: A Case of Solid Organ Transplant-Associated Graft-Versus-Host Disease.pubmed.ncbi.nlm.nih.gov
- Endoscopic findings in patients with Shwachman-Diamond syndrome: A report from the North American Shwachman-Diamond syndrome registry.pubmed.ncbi.nlm.nih.gov
- Sequential High-Dose Ruxolitinib and Low-Dose Splenic Irradiation for Pretransplant Management of Splenomegaly Before Allogeneic Hematopoietic Cell Transplantation With Fludarabine/Busulfan-Based Conditioning in Myelofibrosis.pubmed.ncbi.nlm.nih.gov
- Severe Gastrointestinal Graft-versus-Host Disease Following Haploidentical Stem Cell Transplantation Presenting With Passage of a Colonic Cast.pubmed.ncbi.nlm.nih.gov
- Gastrointestinal acute graft versus host disease: a translational perspective from pathogenesis to precision prevention and treatment.pubmed.ncbi.nlm.nih.gov
- Diagnostic prediction of gastrointestinal graft-versus-host disease based on a clinical- CT- signs nomogram model.pubmed.ncbi.nlm.nih.gov
- Intestinal Angioedema: A Mimic of an Acute Abdomen.pubmed.ncbi.nlm.nih.gov
- Current Developments and Role of Intestinal Ultrasound including the Advent of AI.pubmed.ncbi.nlm.nih.gov
- Guidelines on the Use of Therapeutic Apheresis in Clinical Practice-Evidence-Based Approach From the Writing Committee of the American Society for Apheresis: The Tenth Special Issue.pubmed.ncbi.nlm.nih.gov
- The Importance and Challenges of Early Diagnosis of Paraneoplastic Skin Syndromes in Cancer Detection-A Review.pubmed.ncbi.nlm.nih.gov
- Review Article: Immune Effector Cell-Mediated Enterocolitis Following CAR-T Cell Therapy-Clinical Features, Pathophysiology and Management.pubmed.ncbi.nlm.nih.gov
- Emerging Techniques in Minimally Invasive Surgery in Hematologic Malignancies.pubmed.ncbi.nlm.nih.gov
- Giardiasis in the Immunocompromised: A Case Series Highlighting Diagnostic Pitfalls and Treatment Challenges.pubmed.ncbi.nlm.nih.gov
- Lupus enteritis and peritonitis presenting as initial manifestations of systemic lupus erythematosus: diagnostic challenge in tuberculosis-endemic regions - case report.pubmed.ncbi.nlm.nih.gov
- Case Report: Suspected <i>Mycobacterium abscessus</i>-associated polyserositis following coronary stenting, diagnosed with the aid of metagenomic next-generation sequencing.pubmed.ncbi.nlm.nih.gov
- Hiding in Plain Sight: A Case of Intestinal Tuberculosis Masquerading as Benign Lower GI Bleeding.pubmed.ncbi.nlm.nih.gov
- Imaging of abdominal and pelvic infections in the cancer patient.pubmed.ncbi.nlm.nih.gov
- Imaging panorama in postoperative complications after liver transplantation.pubmed.ncbi.nlm.nih.gov
- Imaging in pediatric small bowel transplantation.pubmed.ncbi.nlm.nih.gov
- Analysis of Diagnosis and Treatment of Active Lupus Enteritis Accompanied by Intestinal Pseudo-Obstruction as the Initial Manifestation: A Case Report and Literature Review.pubmed.ncbi.nlm.nih.gov
- Feline chronic diarrhea: causes and nutritional management.pubmed.ncbi.nlm.nih.gov
- Gastrointestinal Involvement in Adult IgA Vasculitis: A Comprehensive Review.pubmed.ncbi.nlm.nih.gov
- A Practical Approach in Differentiating IBD From Other Causes of Enterocolitis.pubmed.ncbi.nlm.nih.gov
- Diagnosis and management of immune effector cell-associated enterocolitis after ciltacabtagene autoleucel.pubmed.ncbi.nlm.nih.gov
- Overcoming the Odds: Successful Treatment of Disseminated Mucormycosis with Gastrointestinal and Jaw Involvement in a Patient with Acute Myeloid Leukemia.pubmed.ncbi.nlm.nih.gov
- Immune-Related Adverse Events Induced by Immune Checkpoint Inhibitors and CAR-T Cell Therapy: A Comprehensive Imaging-Based Review.pubmed.ncbi.nlm.nih.gov
- Management of Crohn's disease in Taiwan: consensus guideline of the Taiwan Society of Inflammatory Bowel Disease updated in 2023.pubmed.ncbi.nlm.nih.gov
- Advances in Pediatric Diagnostic Endoscopy: A State-of-the-Art Review.pubmed.ncbi.nlm.nih.gov
- Is Contrast-Enhanced Ultrasonography a New, Reliable Tool for Early-Graft-versus-Host Disease Diagnosis?pubmed.ncbi.nlm.nih.gov
- Imaging of intestinal vasculitis focusing on MR and CT enterography: a two-way street between radiologic findings and clinical data.pubmed.ncbi.nlm.nih.gov
- Mucosal-Associated Invariant T Cells in Health and Disease.pubmed.ncbi.nlm.nih.gov
- Secondary causes of inflammatory bowel diseases.pubmed.ncbi.nlm.nih.gov
Eğitim amaçlıdır; hasta başında tanı ve tedavi kararının yerine geçmez. İçerik yapay zekâ destekli bir süreçle güncel literatüre göre cümle cümle kaynaklarla karşılaştırıldı, ancak uzman radyolog incelemesinden geçmedi. Klinik kararlarda güncel kılavuzları, kurum protokollerini ve radyoloji raporunu esas alın.