Özet
PanNEC, küçük hücreli veya büyük hücreli morfoloji gösterebilen, kötü diferansiye ve yüksek dereceli pankreatik nöroendokrin neoplazmdır. İyi diferansiye PanNET G3 de yüksek proliferasyon gösterebilir, ancak PanNEC ile aynı hastalık değildir. Kontrastlı çok fazlı BT primer kitlenin yerini, damar ilişkisini ve karaciğer başta olmak üzere metastatik yayılımı haritalar; PanNEC çoğu zaman klasik hipervasküler PanNET görünümünü vermez. Hızlı büyüyen, nekrotik ve invaziv kitle ile yaygın metastaz tanıyı düşündürür, ancak kesin sınıflama doku örneği gerektirir. Lezyonun PanNET sanılması biyolojik davranış ve evrelemenin yanlış yorumlanmasına yol açabilir.
Faz ve pencere
- Arteriyel tanısal
- Primer kitle sıklıkla pankreas parankiminden daha az kontrastlanan heterojen solid kitle olarak öne çıkar; arteriyel seri tümör sınırını ve değişken ya da hipovasküler olabilecek karaciğer metastazlarını gösterir, ancak belirgin hipervasküler görünüm beklenmez.
- Portal tanısal
- Heterojen kitle, nekrotik düşük atenüasyonlu alanlar, karaciğer metastazları, bölgesel lenf nodları ve portal-splenik-mezenterik damarlarla temas veya invazyon değerlendirilir.
- Kontrastsız
- Kitle çoğunlukla izodens veya hafif hipodens yumuşak doku kitlesidir; kanama ya da kalsifikasyon varsa bu seri ek bilgi sağlar, fakat tek başına karakterizasyon için yeterli değildir.
Önerilen pencereler: Batın (G 400 / M 50), Karaciğer (G 150 / M 30), Yumuşak doku (G 400 / M 40).
BT bulguları
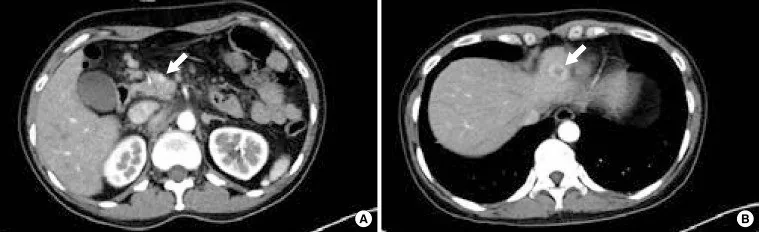
- Pankreas kuyruğu veya gövdesinde büyük, düzensiz sınırlı, heterojen solid kitle; baş yerleşimi de mümkündür
- İyi diferansiye PanNET'ten farklı olarak hipovasküler veya değişken kontrastlanan primer lezyon
- Kitle merkezinde nekroz ya da kistik dejenerasyon biçiminde düşük atenüasyonlu alanlar
- Pankreas konturunun bozulması ve komşu yağ planlarının silinmesiyle infiltratif büyüme
- Yaygın venöz tromboz (splenik ve portal ven gibi) yapabilir; ayrıca komşu büyük damarlara ve organlara direkt invazyon ileri evre hastalığına işaret edebilir.
- Çok odaklı veya çevresel kontrastlanan karaciğer metastazları; görünürlükleri kontrast fazına göre değişebilir
- Peripankreatik ve üst abdominal lenf nodları ile uzak organ metastazları
- Ana pankreatik kanal veya safra kanalında genişleme eşlik edebilir, fakat belirgin kanal genişlemesi şart değildir
Ölçütler ve sınıflamalar
- WHO 2019: pankreatik nöroendokrin neoplazmlar
- İyi diferansiye PanNET’ler G1–G3 olarak derecelendirilir; kötü diferansiye nöroendokrin karsinomlar küçük hücreli veya büyük hücreli morfolojide, yüksek dereceli tümörlerdir. İyi diferansiye PanNET G3, PanNEC ile eş anlamlı değildir; görüntüleme diferansiyasyonu kesinleştiremez.
- AJCC Version 9: PanNET ve PanNEC evreleme kapsamı
- AJCC Version 9 pankreatik NET protokolü iyi diferansiye PanNET evrelemesine aittir. Kötü diferansiye PanNEC ve MiNEN, organ-özgül karsinom ölçütleriyle evrelenir; PanNEC’ye PanNET protokolü uygulanmamalıdır.
Normalde
Normal pankreas parankimi homojen yapıda ve düzgün konturludur; ana pankreatik kanal belirgin genişleme veya kesinti göstermeden kesintisiz izlenir. Aynı düzeyde lezyonun parankime göre kontrastlanma farkını, kontur kaybını ve yağ planlarının korunup korunmadığını kıyasla; karaciğer segmentlerinde yeni odak veya damar lümeninde daralma normal görünümde bulunmaz.
Normal BT ile kıyasla
Aynı bölgenin, kaynak veri setinde patoloji içermediği belirtilen bir BT incelemesini kesit kesit kaydırın; organ sınırlarını açarak anatomiyi hasta görüntüsüyle karşılaştırın. Küçük rastlantısal bulgular tümüyle dışlanmamıştır.
Kaynak: TotalSegmentator v2.01 veri seti (Wasserthal ve ark., Radiology: Artificial Intelligence 2023), CC BY 4.0, vaka s0541; organ sınırları veri setinin otomatik segmentasyonundan, birleştirilerek sadeleştirildi. Görüntüler 2,5 mm kesit aralığına yeniden örneklendi.
Ayırıcı tanı
- İyi diferansiye PanNET
- sıklıkla sınırlı ve arteriyel fazda belirgin hipervaskülerdir; kötü diferansiye PanNEC daha sık heterojen, nekrotik ve infiltratiftir.
- Pankreatik duktal adenokarsinom
- çoğunlukla infiltratif hipovasküler kitle, ani kanal kesilmesi ve yukarı akım kanal genişlemesi/atrofi yapar; histoloji olmadan kesin ayrım yapılamaz.
- Solid psödopapiller neoplazm
- daha çok genç kadınlarda, iyi sınırlı kapsüllü kitle ve kanama-kistik dejenerasyonla görülür.
- Pankreas metastazı
- böbrek hücreli karsinom öyküsü ve arteriyel hipervasküler odaklar metastazı destekler; primer pankreatik NEC'de klinik öykü ve yayılım paterni ayırt ettirir.
- Akut fokal pankreatit
- çevresel inflamasyon ve sıvı değişiklikleri gösterebilir; kitle benzeri görünüm takipte gerileyebilir, ancak klinik ve doku değerlendirmesi önemlidir.
Tuzaklar
- PanNEC ile iyi diferansiye PanNET G3’ü yalnız proliferasyon düzeyine göre eşitlemeyin; WHO sınıflaması diferansiyasyonu da esas alır ve ayrım histopatolojiktir.
- PanNEC'yi hipervasküler görmeyi bekleme; kötü diferansiye olgular pankreas kitlesi ve karaciğer metastazlarında hipokontrastlanabilir.
- Nekroz nedeniyle merkezdeki düşük atenüasyonu kistik neoplazm sanma; çevredeki solid komponenti ve infiltratif sınırı incele.
- Bir fazda görünmeyen karaciğer odağını dışlama; metastaz kontrastlanması değişken olduğundan arteriyel ve portal serileri birlikte gözden geçir.
Kendini dene
Pankreas kuyruğunda nekrotik, infiltratif kitle ve çok sayıda karaciğer odağı var; primer kitle belirgin hipervasküler değil. Hangi tümör tipi daha olasıdır?
Cevabı göster
Pankreatik nöroendokrin karsinom. Kötü diferansiye PanNEC heterojen, nekrotik ve infiltratif olabilir; hipervasküler PanNET görünümü şart değildir. İyi diferansiye PanNET çoğu kez sınırlı ve arteriyel hipervaskülerdir; seröz neoplazm mikrokistik, solid psödopapiller neoplazm ise genellikle kapsüllü ve dejeneratif görünür.
Pankreatik kitleye ek olarak karaciğerde yeni odaklar görülüyor. Metastaz taramasında hangi BT incelemesi en uygundur?
Cevabı göster
Arteriyel ve portal fazlı pankreas protokolü. Pankreas protokolündeki arteriyel ve portal fazlar primer kitlenin damar ilişkisini ve değişken kontrastlanan karaciğer metastazlarını birlikte değerlendirmeye yardım eder. Kontrastsız, kemik ve üriner faz tek başına bu amaç için uygun değildir.
Kaynaklar
Bu sayfadaki 46 cümle ve 2 quiz sorusu aşağıdaki kaynaklardan alıntılarla tek tek karşılaştırıldı; 4 cümle bu karşılaştırmada düzeltildi (2026-10-08).
- Imaging of Pancreatic Neuroendocrine Neoplasmspmc.ncbi.nlm.nih.gov
- The 2019 WHO classification of tumours of the digestive systempmc.ncbi.nlm.nih.gov
- Penpulimab in an adolescent patient with pancreatic neuroendocrine carcinoma with liver metastasis: A case report and literature reviewpmc.ncbi.nlm.nih.gov
- Molecular drivers and cells of origin in pancreatic ductal adenocarcinoma and pancreatic neuroendocrine carcinomapmc.ncbi.nlm.nih.gov
- Nonfunctional Pancreatic Neuroendocrine Carcinoma With Isolated Retroperitoneal Metastasispmc.ncbi.nlm.nih.gov
- Non-functioning pancreatic neuroendocrine tumors--a case report and review of literature.pubmed.ncbi.nlm.nih.gov
- [Magnetic resonance imaging features of pancreatic neuroendocrine carcinoma: a literature review].pubmed.ncbi.nlm.nih.gov
- CT and MR evaluation of main pancreatic duct dilation: A radiologist's guide to differentiating benign from malignant causes.pubmed.ncbi.nlm.nih.gov
- Penpulimab in an adolescent patient with pancreatic neuroendocrine carcinoma with liver metastasis: A case report and literature review.pubmed.ncbi.nlm.nih.gov
- Pancreatic panniculitis.pubmed.ncbi.nlm.nih.gov
- Adrenocorticotropin Hormone Secreting Carcinoma of the Pancreas: A Case Report.pubmed.ncbi.nlm.nih.gov
- Clinicopathological features of small nonfunctioning pancreatic neuroendocrine tumors.pubmed.ncbi.nlm.nih.gov
- A case of metachronous double primary neuroendocrine cancer in pancreas/ileum and uterine cervix.pubmed.ncbi.nlm.nih.gov
- A malignant cause of hypoglycaemia: a metastatic insulin-secreting pancreatic neuroendocrine carcinoma.pubmed.ncbi.nlm.nih.gov
- Pancreatic neuroendocrine carcinoma diagnosed using endoscopic ultrasound-guided fine needle aspiration: A case report and literature review.pubmed.ncbi.nlm.nih.gov
- The value of MRI in identifying pancreatic neuroendocrine tumour G3 and carcinoma G3.pubmed.ncbi.nlm.nih.gov
- Characterization of single lesion nonfunctioning pancreatic neuroendocrine carcinoma via computed tomography.pubmed.ncbi.nlm.nih.gov
- Historical Evolution of Terminology and Current Classification of Neuroendocrine Neoplasms of the Larynx and Mixed Neuroendocrine-Non-Neuroendocrine Neoplasms (MiNENs): A Narrative Review.pubmed.ncbi.nlm.nih.gov
- What are the Unmet Needs in Managing Digestive Neuroendocrine Carcinomas?pubmed.ncbi.nlm.nih.gov
- Cytological Identification of a Rhabdoid Variant of Pancreatic Neuroendocrine Neoplasm.pubmed.ncbi.nlm.nih.gov
- Combined pancreatic grade 1 neuroendocrine tumour and ductal adenocarcinoma - MiNEN versus collision tumour: a rare surgical case report and diagnostic challenge.pubmed.ncbi.nlm.nih.gov
- The Genomic Patterns of Well-Differentiated Pancreatic Neuroendocrine Tumors (NETs) Identify Sub-Sets for Rational Therapeutic Targeting.pubmed.ncbi.nlm.nih.gov
- AI-powered histopathology classifiers identify transcriptomic biomarkers associated with cell cycle regulation and increased mitotic activity in poorly differentiated neuroendocrine carcinoma.pubmed.ncbi.nlm.nih.gov
- Incidental cystic pancreatic neuroendocrine neoplasm and differential diagnosis.pubmed.ncbi.nlm.nih.gov
- A retrospective comparative study of CT and MRI findings of different types of pancreatic serous cystic neoplasms: Correlation with histopathology.pubmed.ncbi.nlm.nih.gov
- Appropriate use of tissue sampling and somatostatin receptor PET imaging in the diagnosis of pancreatic neuroendocrine tumors: results of an International Delphi Consensus.pubmed.ncbi.nlm.nih.gov
- Marked response to dabrafenib plus trametinib in a patient with BRAF V600E-mutant pancreatic hepatoid carcinoma: a case report and systematic analysis of 57 cases.pubmed.ncbi.nlm.nih.gov
- Lymph node metastasis from a small papillary renal cell carcinoma mimicking pancreatic infiltration: A case report.pubmed.ncbi.nlm.nih.gov
- Mapping Misconceptions in Neuroendocrine Tumor Nomenclature: A Scoping Review of National Database Studies and Clinical Implications.pubmed.ncbi.nlm.nih.gov
- Radiologically Probable Late-Onset Von Hippel-Lindau Syndrome: A Case Report.pubmed.ncbi.nlm.nih.gov
- Upper common bile duct neuroendocrine tumor presenting with obstructive jaundice: a case report and literature review.pubmed.ncbi.nlm.nih.gov
- Splenic Vein Tumor Thrombosis in a Patient With an Oligometastatic Pancreatic Neuroendocrine Tumor: A Case Report and Literature Review.pubmed.ncbi.nlm.nih.gov
- Imaging of pancreatic hepatoid adenocarcinoma: a scoping review.pubmed.ncbi.nlm.nih.gov
- Differentiation between G3 pancreatic neuroendocrine tumor and pancreatic neuroendocrine carcinoma based on intratumor and peritumor CT value ratio and abnormal vascular network.pubmed.ncbi.nlm.nih.gov
- Case Report: Delayed diagnosis of pancreatic solid pseudopapillary neoplasm in a boy initially misdiagnosed as traumatic retroperitoneal hematoma.pubmed.ncbi.nlm.nih.gov
- Solid serous adenoma of the pancreas mimicking a solid pseudopapillary neoplasm: A case report.pubmed.ncbi.nlm.nih.gov
- Mixed exocrine-neuroendocrine intraductal papillary mucinous neoplasms of the pancreas: a case series.pubmed.ncbi.nlm.nih.gov
- Metachronous Primary Pancreatic Neuroendocrine Tumor and Adenocarcinoma: A Case Report.pubmed.ncbi.nlm.nih.gov
- Unusual cystic presentation of pheochromocytoma in a case of suspected von Hippel-Lindau disease.pubmed.ncbi.nlm.nih.gov
- Schwannoma Likely Arising from the Pancreatic Head Nerve Plexus That Mimicked a Mucinous Cystic Neoplasm and Was Treated by Pancreaticoduodenectomy: A Case Report.pubmed.ncbi.nlm.nih.gov
- Common cystic pancreatic neoplasms: A comprehensive magnetic resonance imaging-based review of typical and atypical imaging features.pubmed.ncbi.nlm.nih.gov
- APC-rearranged solid pseudopapillary neoplasm-pancreatic neuroendocrine tumor collision tumor: a molecularly resolved case report.pubmed.ncbi.nlm.nih.gov
- Analysis of misdiagnosis of pancreatic acinar cell carcinoma with significantly elevated alpha-fetoprotein: a case report and literature review.pubmed.ncbi.nlm.nih.gov
- Pancreatic Collision Tumor Composed of Solid Pseudopapillary Neoplasm and Well-Differentiated Neuroendocrine Tumor: Diagnostic Challenges and Classification Considerations.pubmed.ncbi.nlm.nih.gov
- Utilizing allogeneic venous grafts to solve the problem of vascular defects and reconstruction in pancreatic surgery: a retrospective cohort study.pubmed.ncbi.nlm.nih.gov
- From companion animals to patients: interspecies lessons in neuroendocrine oncology.pubmed.ncbi.nlm.nih.gov
- The Use of Adjunct Therapies with Surgery for Gastroenteropancreatic Neuroendocrine Tumors: Indications, Timing, and Outcomes.pubmed.ncbi.nlm.nih.gov
- Primary pancreatic squamous cell carcinoma with duodenal invasion: Literature review and a case report.pubmed.ncbi.nlm.nih.gov
- Rapidly Progressive Neuroendocrine Carcinoma of the Ampulla of Vater Detected During Intraductal Papillary Mucinous Neoplasm Surveillance.pubmed.ncbi.nlm.nih.gov
- Multiple Incidental Pancreatic Neuroendocrine Tumors in a Patient With Suspected Duodenal Papillary Adenocarcinoma: A Case Report.pubmed.ncbi.nlm.nih.gov
- Videolaparoscopic pancreatojejunostomy using a hybrid technique in chronic pancreatitis without significant ductal dilatation.pubmed.ncbi.nlm.nih.gov
- Geometric simplification by ductal unification of dual pancreatic ducts during pancreaticojejunostomy.pubmed.ncbi.nlm.nih.gov
- Surgical and functional outcomes of pediatric pancreatic solid pseudopapillary neoplasm: A retrospective study.pubmed.ncbi.nlm.nih.gov
- A modified stent-free Chen's U-suture technique in pediatric pancreaticojejunostomy: safety and efficacy.pubmed.ncbi.nlm.nih.gov
- Cholecystogastric fistula masquerading as gastrointestinal stromal tumour: Unusual presentation of gallbladder adenomyomatosis - a case report.pubmed.ncbi.nlm.nih.gov
- Modified TNM staging system for well-differentiated pancreatic neuroendocrine tumors: A comparative study with the AJCC 9th edition.pubmed.ncbi.nlm.nih.gov
- Using Machine Learning to Revise the AJCC Staging System for Neuroendocrine Tumors of the Pancreas.pubmed.ncbi.nlm.nih.gov
- Development and internal validation of a SEER-based prediction model for survival in poorly and undifferentiated colorectal neuroendocrine neoplasms.pubmed.ncbi.nlm.nih.gov
- Histopathological subtypes independently predict survival in ampullary carcinoma: a contemporary SEER nomogram study.pubmed.ncbi.nlm.nih.gov
- Association of primary-site surgery with survival in patients with metastatic gastroenteropancreatic neuroendocrine carcinoma: a population-based SEER study (2004-2023).pubmed.ncbi.nlm.nih.gov
- Single-Cell and Spatial Transcriptomics Reframe the Immunosuppressive Microenvironment of Neuroendocrine Neoplasms.pubmed.ncbi.nlm.nih.gov
- The metastatic spectrum in functional and non-functional NENs: mechanistic insights from multi-omics.pubmed.ncbi.nlm.nih.gov
- When Immunophenotype Is Not Identity: A Clinicopathological Review of Neuroendocrine Differentiation in Tumors of the Female Genital Tract.pubmed.ncbi.nlm.nih.gov
- Pancreatic Acinar Cell Carcinoma: A Rare Pancreatic Malignancy with Distinct Biology and Emerging Therapeutic Opportunities.pubmed.ncbi.nlm.nih.gov
- CAF-derived PTGDS drives pancreatic cancer neuroendocrine differentiation and chemoresistance via PAQR9-MAPK.pubmed.ncbi.nlm.nih.gov
- Solid pseudopapillary neoplasm of the pancreas: a rare tumor case report.pubmed.ncbi.nlm.nih.gov
- Frantz-Gruber tumor with atypical presentation as a pancreatic pseudocyst following abdominal trauma: a case report.pubmed.ncbi.nlm.nih.gov
- Intussusception caused by metastatic renal cell carcinoma at the duodenojejunal junction 41 years after nephrectomy: a case report.pubmed.ncbi.nlm.nih.gov
- Pancreatic Metastasis from Intracranial Solitary Fibrous Tumor/Hemangiopericytoma Mimicking a Pancreatic Neuroendocrine Tumor: A Case Report and Focused Literature Review.pubmed.ncbi.nlm.nih.gov
- Non-keratinizing immature squamous metaplasia in the pancreas mimicking malignancy: a diagnostic pitfall in cytology.pubmed.ncbi.nlm.nih.gov
- Postpancreatitis extrapancreatic necrosis mimicking peritoneal carcinomatosis: A pediatric diagnostic pitfall.pubmed.ncbi.nlm.nih.gov
- Nodal metastasis from an occult duodenal gastrinoma amid an overlap of xanthogranulomatous and type 1 autoimmune pancreatitis: A case report.pubmed.ncbi.nlm.nih.gov
- Grading medullary thyroid carcinoma on fine needle aspiration biopsy specimens: a comparative study between manual counting and a deep learning platform.pubmed.ncbi.nlm.nih.gov
- Three-Tier Prognostic Stratification of Lung Carcinoids (NET G1-G2-G3) by Multivariable, Data-Driven Integration of Ki-67 and Mitotic Count.pubmed.ncbi.nlm.nih.gov
- Grading and detecting gastroenteropancreatic neuroendocrine neoplasms with dual-tracer ( 18 F-AlF-NOTA-octreotide/ 18 F-FDG) PET/CT: a metabolic parameter-based study.pubmed.ncbi.nlm.nih.gov
- Percutaneous Computed Tomography (CT)-Guided Biopsy of Focal Chest Wall Lesions: A Retrospective Cohort Study.pubmed.ncbi.nlm.nih.gov
- Correlation between positive biopsy rates and contrast-enhanced ultrasound findings in patients with pancreatic cancer: a retrospective analysis of percutaneous ultrasound-guided fine-needle aspiration.pubmed.ncbi.nlm.nih.gov
- Pediatric Solid Pseudopapillary Neoplasm With Aberrant CD31 Expression: A Potential Diagnostic Pitfall.pubmed.ncbi.nlm.nih.gov
- X-ray histology on rapidly fixed fresh tumor tissue samples for fast resection margin assessment.pubmed.ncbi.nlm.nih.gov
- Pancreatic Atrophy: A Narrative Review and Surgical Interpretation.pubmed.ncbi.nlm.nih.gov
- The role of preoperative 3D reconstruction in optimizing surgical planning and intraoperative guidance during laparoscopic distal pancreatectomy: a pilot study.pubmed.ncbi.nlm.nih.gov
- Heterogeneity Analyzed by CT-Based Habitat Analysis for Clinical Management of Cancers: A Narrative Review.pubmed.ncbi.nlm.nih.gov
- Giant Pancreatic Acinar Cell Carcinoma: A Case Report and Review of Molecular Pathogenesis and Emerging Therapies.pubmed.ncbi.nlm.nih.gov
- Case Report: Pancreatic amphicrine-like carcinoma with acinar differentiation harboring a KANK4-RAF1 gene fusion.pubmed.ncbi.nlm.nih.gov
- Pancreatic Neuroendocrine Tumor in Lynch Syndrome: Expanding the Tumor Spectrum of Mismatch Repair Deficiency.pubmed.ncbi.nlm.nih.gov
- Magnetic Resonance Imaging Features of Hepatic Hydatid Disease: A Pictorial Review with Emphasis on Atypical Presentations and Differential Diagnosis.pubmed.ncbi.nlm.nih.gov
- When rarity meets thoracic cancers: a narrative review from ITMIG 2024.pubmed.ncbi.nlm.nih.gov
- Case Report: The cystic masquerade in type 1 Von Hippel-Lindau disease: coexisting clear cell renal cell carcinoma and an imaging-suspected pancreatic neuroendocrine tumor.pubmed.ncbi.nlm.nih.gov
- The Role of the Mesopancreas in Pancreatic Neuroendocrine Neoplasms.pubmed.ncbi.nlm.nih.gov
- Three Types of Collateral Arterial Supply to the Spleen After Spleen-Preserving Distal Pancreatectomies with Splenic Vessels Resection-How to Use This Knowledge for Organ(s) Preservation in Locally Advanced and Borderline Resectable Pancreatic Head Cancers Surgery-Hemodynamic, Surgical and Oncological Outcomes of 134 Spleen-Preserving Pancreatectomies.pubmed.ncbi.nlm.nih.gov
- Role of Endoscopic Ultrasonography in Management of Pancreaticobiliary Cancers: Recent Trends and Advances.pubmed.ncbi.nlm.nih.gov
- Dorsal Pancreatic Agenesis Associated With New-Onset Diabetes Mellitus and Acute Pancreatitis in an 18-Year-Old Man: A Case Report.pubmed.ncbi.nlm.nih.gov
- Endoscopic Ultrasound-Guided Radiofrequency Ablation for Pancreatic Metastases: Safety and Clinical Outcomes in a Single-Center Case Series.pubmed.ncbi.nlm.nih.gov
- Updates on Imaging Assessment of Pancreatic Cancer for Determining Anatomic and Biologic Resectability.pubmed.ncbi.nlm.nih.gov
- A pictorial essay on cross-sectional imaging findings of pathologies in the second (D2) segment of the duodenum in adults.pubmed.ncbi.nlm.nih.gov
- Advances in MRI in the Evaluation of Chronic Pancreatitis and the Less Common Forms of Pancreatitis.pubmed.ncbi.nlm.nih.gov
- Case Report: Alternative biopsy targets plus CEUS-guided omental puncture: enabling CLDN18.2 detection and precision therapy enrollment in pancreatic cancer.pubmed.ncbi.nlm.nih.gov
- Role of B-Mode and Contrast-Enhanced Ultrasound in the Diagnostic Workflow of Gastro-Entero-Pancreatic Neuroendocrine Tumors (GEP-NETs).pubmed.ncbi.nlm.nih.gov
- Stocky/Packed Pancreas: A Case of Focal Drug-Induced Acute Pancreatitis Mimicking Cancer.pubmed.ncbi.nlm.nih.gov
- T Cell Roles and Activity in Chronic Sclerosing Sialadenitis as IgG4-Related Disease: Current Concepts in Immunopathogenesis.pubmed.ncbi.nlm.nih.gov
- Acinar cell carcinoma of the pancreas: can CT and MR features predict survival?pubmed.ncbi.nlm.nih.gov
- The Many Faces of the Angry Peritoneum.pubmed.ncbi.nlm.nih.gov
- An update on pancreatic cancer imaging, staging, and use of the PACT-UK radiology template pre- and post-neoadjuvant treatment.pubmed.ncbi.nlm.nih.gov
- Splenic Torsion in a Patient with Polysplenia Syndrome and Dorsal Pancreatic Agenesis: A Case Report.pubmed.ncbi.nlm.nih.gov
- Radiological Assessment After Pancreaticoduodenectomy for a Precision Approach to Managing Complications: A Narrative Review.pubmed.ncbi.nlm.nih.gov
- Dynamic volume perfusion CT for preoperative multidimensional resectability assessment of pancreatic ductal adenocarcinoma.pubmed.ncbi.nlm.nih.gov
- Preoperative Imaging Assessment and Staging of Perihilar Cholangiocarcinoma: Tips and Pitfalls.pubmed.ncbi.nlm.nih.gov
- Imaging of the Liver and Pancreas: The Added Value of MRI.pubmed.ncbi.nlm.nih.gov
- Spontaneous Bacterial Peritonitis as a Rare Complication of a Pancreatic Duct Leak in a Patient Without Cirrhosis: A Case Report.pubmed.ncbi.nlm.nih.gov
- Distal vs. total pancreatectomy with celiac axis resection in patients with locally advanced/borderline resectable pancreatic carcinoma - a retrospective cohort study.pubmed.ncbi.nlm.nih.gov
- Pancreatic Neuroendocrine Tumors: From Benchside to Surgical Treatment.pubmed.ncbi.nlm.nih.gov
- Diagnosis and Surgical Management for Advanced Pancreatic Cancer Requiring Vascular Resection.pubmed.ncbi.nlm.nih.gov
- Case Report: Robotic-assisted laparoscopic primary repair for pancreaticoduodenal grade V injury in a pediatric patient.pubmed.ncbi.nlm.nih.gov
- Hepatic metastasis of mucinous adenocarcinoma with neuroendocrine differentiation harboring a rare HER2 R678Q mutation: a case report and literature review.pubmed.ncbi.nlm.nih.gov
- IgG4-related autoimmune pancreatitis mimicking pancreatic carcinoma: a case report.pubmed.ncbi.nlm.nih.gov
Eğitim amaçlıdır; hasta başında tanı ve tedavi kararının yerine geçmez. İçerik yapay zekâ destekli bir süreçle güncel literatüre göre cümle cümle kaynaklarla karşılaştırıldı, ancak uzman radyolog incelemesinden geçmedi. Klinik kararlarda güncel kılavuzları, kurum protokollerini ve radyoloji raporunu esas alın.