Özet
Ağır kafa travması ve rotasyonel kuvvet sonrası mezensefalon veya pons hasarı, hastanın bilinç ve nörolojik durumunu belirleyen kritik bir bulgudur. Kontrastsız BT'de büyük kanama, ödem veya kontüzyon görülebilir; küçük peteşiyal odaklar ve hemorajik olmayan hasar BT'de kolayca saklı kalır. Dorsolateral üst beyin sapı ve serebral pedinküller dikkatle taranmalı, klinik ağırlık BT ile açıklanmıyorsa MR ile ileri değerlendirme düşünülmelidir. Bası herniasyonuna bağlı Duret kanamasını birincil travmatik odaktan ayırmamak yaralanma mekanizmasının yanlış yorumlanmasına yol açabilir.
Faz ve pencere
- Kontrastsız tanısal
- Akut kanama beyin sapı parankiminde küçük noktasal hiperdens odak, daha büyük kontüzyon veya yaygın kanama şeklinde izlenebilir; hemorajik olmayan yaralanmada lokal düşük atenüasyon ya da BT'de belirgin bulgu olmayabilir. Kontrastsız BT klinik değerlendirmenin yanı sıra akut beyin travması değerlendirmesinin temel taşıdır; beyin sapı ve çevresindeki sisternalar incelemeye dahil edilmelidir.
Önerilen pencereler: Beyin (G 80 / M 40), Subdural (G 200 / M 75).
BT bulguları
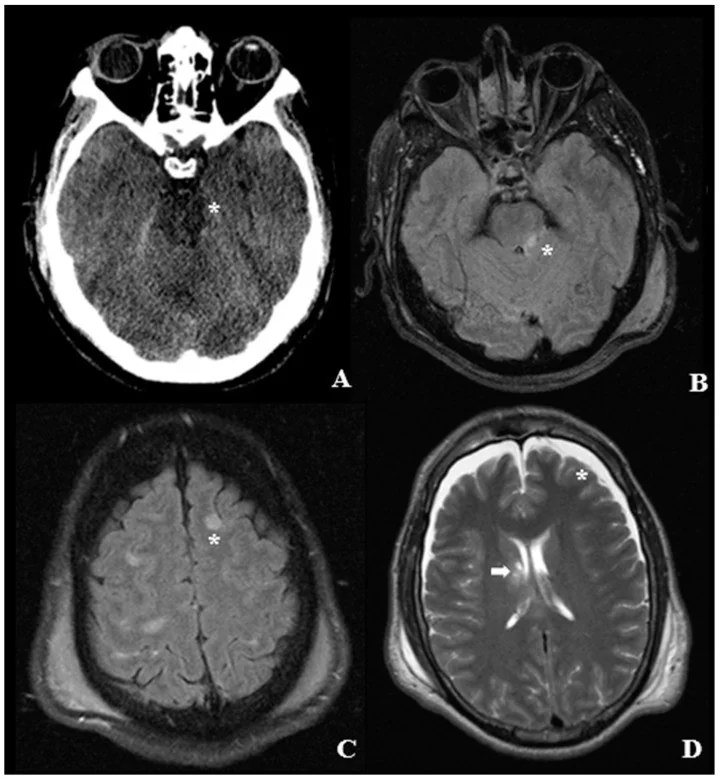
- Dorsolateral mezensefalik peteşi — üst beyin sapının yan-arka kısmında küçük, sınırlı hiperdens odak.
- Serebral pedinküllerin simetrisini ve dansitesini kontrol edin; perimesensefalik sisterna basısı veya ödem nedeniyle pedinküllerde deformite veya kaybolma gözlenebilir, normalde ise perimesensefalik CSF ile net sınırlanmış simetrik yapılar izlenir.
- Üst pons kontüzyonu — pons parankiminde daha büyük hemorajik odak, çevresel düşük dansite veya lokal genişleme.
- Dağınık derin odaklar — talamus, hipotalamus, periaquaduktal bölge veya derin beyaz cevherde eşlik eden travmatik peteşiler.
- Beyin sapı deformasyonu — pons/mezensefalon çevresindeki sisternaların silinmesi, komşu hematom basısı veya aksiyel kontur asimetrisi.
- Herniasyon eşliği — sisternal effasman, transtentoryal yer değiştirme ve beyin sapı içindeki orta hat Duret kanaması.
- BT-MR duyarlılık farkı — BT'de izlenemeyen mikrokanama ve ödem odakları MR SWI/GRE, FLAIR ve DWI'da belirginleşebilir.
Normalde
Normal mezensefalon ve ponsun konturu iki taraflı simetriktir; serebral pedinküller benzer dansitede, prepontin ve interpedinküler sisternalar açıktır. Aynı düzeyde karşı pedinkülün genişlik ve dansitesini, beyin sapı çevresindeki sisterna açıklığını ve orta hatta yeni hiperdens bir çizgi olup olmadığını kıyaslayın.
Normal BT ile kıyasla
Aynı bölgenin, kaynak veri setinde patoloji içermediği belirtilen bir BT incelemesini kesit kesit kaydırın; organ sınırlarını açarak anatomiyi hasta görüntüsüyle karşılaştırın. Küçük rastlantısal bulgular tümüyle dışlanmamıştır.
Kaynak: TotalSegmentator v2.01 veri seti (Wasserthal ve ark., Radiology: Artificial Intelligence 2023), CC BY 4.0, vaka s0103; organ sınırları veri setinin otomatik segmentasyonundan, birleştirilerek sadeleştirildi. Görüntüler 2,5 mm kesit aralığına yeniden örneklendi.
Ayırıcı tanı
- Duret kanaması
- transtentoryal herniasyon ve ciddi kitle etkisi zemininde pons/mezensefalon orta hattında kanama yapar; izole dorsolateral peteşiden mekanizma ve dağılımıyla ayrılır.
- Kavernöz malformasyon
- genellikle sınırlı, tekrarlayan kan ürünleri içeren bir beyin sapı odağıdır; travmatik dağılım veya eşlik eden aksonal odaklar bulunmayabilir.
- Akut beyin sapı iskemi
- infraötörital bölge artefaktları nedeniyle BT'de erken dönemde saptanamayabilir veya kompresyona bağlı hipodensite taklit edebilir; difüzyon ağırlıklı MR duyarlılığı artırır ancak küçük lezyonlarda başlangıçta negatif olabilir.
- Hemorajik kontüzyon
- daha büyük, düzensiz ve ödemli parankimal kan odağı yapar; aynı travmada beyin sapı dışında kortikal yüzey odakları da beklenebilir.
- Parsiyel hacim/kemik sertleşme artefaktı
- posterior fossada gerçek lezyonu örtebilir ya da yapay dansite farkı oluşturabilir; komşu kesitlerde devamlılık ve simetri kontrol edilir.
Tuzaklar
- Beyin sapı gibi infratentoryal yapılarda artefaktlar ve düşük kontrast nedeniyle travmatik yaralanmalar BT'de kolayca kaçabilir veya tam olarak değerlendirilemeyebilir.
- BT'de beyin sapı odağı görülmemesi yaralanmayı dışlamaz; ağır klinik ile açıklanamayan negatif BT'de MR mikrokanama ve ödemi daha duyarlı gösterir.
- Orta hat Duret kanamasını birincil dorsolateral travmatik peteşiyle eşitlemeyin; eşlik eden bazal sisterna basısı ve transtentoryal herniasyon işaretleri mekanizma için belirleyicidir.
- Tek bir hiperdens noktanın anatomik konumunu doğrulamadan beyin sapı kontüzyonu demeyin; damar kesiti, kalsifikasyon ve parsiyel hacim taklitçileri komşu kesitlerde izlenebilir.
Kendini dene
Erken BT'de saptanan travmatik beyin sapı kanamaları hangi üç ana patolojik tipe ayrılır?
Cevabı göster
Traumatik aksonal yaralanma, kontüzyon ve Duret kanaması. Erken BT değerlendirmesinde travmatik beyin sapı lezyonları travmatik aksonal yaralanma, kontüzyon veya Duret kanaması olarak sınıflandırılır.
Ağır travmada orta hat beyin sapı kanamasına transtentoryal herniasyon eşlik ediyor. Bu bulgular hangi ikincil kanama mekanizmasını düşündürür?
Cevabı göster
Duret kanaması. Transtentoryal herniasyonla birlikte görülen beyin sapı kanaması, ikincil Duret kanaması mekanizmasını destekler. Duret kanaması, ikincil intrakraniyal basınç artışı ve transtentoryal herniasyonla ilişkili beyin sapı kanamasıdır.
İlgili konular
Kaynaklar
Bu sayfadaki 36 cümle ve 2 quiz sorusu aşağıdaki kaynaklardan alıntılarla tek tek karşılaştırıldı; 12 cümle bu karşılaştırmada düzeltildi (2026-10-09).
- A case report of giant inflammatory mass in the hypopharynxpmc.ncbi.nlm.nih.gov
- Possible delayed neuronal death after seemingly successful evacuation of traumatic acute subdural hematoma: Image reportpmc.ncbi.nlm.nih.gov
- Role of Magnetic Resonance Imaging in Acute Head Injury Patients with Normal Computed Tomography Brain Findingspmc.ncbi.nlm.nih.gov
- Computed tomography signs of intracranial hypertension: what intensivists should knowpmc.ncbi.nlm.nih.gov
- Fatal Injuries Caused by Falling Trees: Correlation Between Postmortem Computed Tomography and Forensic Autopsy Findings in Eight Casespmc.ncbi.nlm.nih.gov
- Differential diagnosis of T2 hyperintense brainstem lesions: Part 2. Diffuse lesions.pubmed.ncbi.nlm.nih.gov
- Prognostic Value of Hemorrhagic Brainstem Injury on Early Computed Tomography: A TRACK-TBI Study.pubmed.ncbi.nlm.nih.gov
- The prognostic significance of traumatic brainstem injury detected on T2-weighted MRI.pubmed.ncbi.nlm.nih.gov
- A case report of giant inflammatory mass in the hypopharynx.pubmed.ncbi.nlm.nih.gov
- Imaging assessment of traumatic brain injury.pubmed.ncbi.nlm.nih.gov
- Imaging the trigeminal nerve.pubmed.ncbi.nlm.nih.gov
- The traumatic bone: trauma-induced heterotopic ossification.pubmed.ncbi.nlm.nih.gov
- Coma After Acute Head Injury.pubmed.ncbi.nlm.nih.gov
- Traumatic hematoma of the posterior fossa.pubmed.ncbi.nlm.nih.gov
- Changes in cerebral hemodynamics in patients with posttraumatic diffuse brain swelling after external intraventricular drainage.pubmed.ncbi.nlm.nih.gov
- Preventable fatal injury during rally race: a multidisciplinary approach.pubmed.ncbi.nlm.nih.gov
- Mechanisms of hearing loss after blast injury to the ear.pubmed.ncbi.nlm.nih.gov
- Rapid Detection of Significant Traumatic Brain Injury Requiring Emergency Intervention.pubmed.ncbi.nlm.nih.gov
- Isolated traumatic retroclival hematoma: case report and review of literature.pubmed.ncbi.nlm.nih.gov
- Parkinsonism associated with prolonged unresponsive wakefulness syndrome after blunt head injury: a clinico-pathological study.pubmed.ncbi.nlm.nih.gov
- Two Coarse Spatial Patterns of Altered Brain Microstructure Predict Post-traumatic Amnesia in the Subacute Stage of Severe Traumatic Brain Injury.pubmed.ncbi.nlm.nih.gov
- Traumatic brain injury and the development of parkinsonism: Understanding pathophysiology, animal models, and therapeutic targets.pubmed.ncbi.nlm.nih.gov
- Choking leading to cardiac arrest and subsequent atypical radiological features of brain damage: A case report.pubmed.ncbi.nlm.nih.gov
- Neuroimaging Characterization of Acute Traumatic Brain Injury with Focus on Frontline Clinicians: Recommendations from the 2024 National Institute of Neurological Disorders and Stroke Traumatic Brain Injury Classification and Nomenclature Initiative Imaging Working Group.pubmed.ncbi.nlm.nih.gov
- Diagnostic and Prognostic Capability of Newer Magnetic Resonance Imaging Brain Sequences in Diffuse Axonal Injury Patient.pubmed.ncbi.nlm.nih.gov
- Integrative Diagnostic and Prognostic Paradigms in Diffuse Axonal Injury: Insights from Clinical, Histopathological, Biomolecular, Radiological, and AI-Based Perspectives.pubmed.ncbi.nlm.nih.gov
- Atypical Parkinsonian Syndromes: Structural, Functional, and Molecular Imaging Features.pubmed.ncbi.nlm.nih.gov
- Multimodality imaging of neurodegenerative disorders with a focus on multiparametric magnetic resonance and molecular imaging.pubmed.ncbi.nlm.nih.gov
- Incidence, Clinician Misdiagnosis Rate, Radiologist Missed Diagnosis Rate, and Lesion Distribution of Isolated Medial Longitudinal Fasciculus Infarction: A Retrospective Study.pubmed.ncbi.nlm.nih.gov
- Analysis of Pontine cavernous malformation resection based on 3D microanatomical study.pubmed.ncbi.nlm.nih.gov
- Subarachnoid cisterns as surgical corridors: Integrating microsurgical anatomy and neuroimaging for intracranial navigation.pubmed.ncbi.nlm.nih.gov
- Imaging Evaluation of Acute Traumatic Brain Injury.pubmed.ncbi.nlm.nih.gov
- Locations and clinical significance of non-hemorrhagic brain lesions in diffuse axonal injuries.pubmed.ncbi.nlm.nih.gov
- Imaging for the diagnosis and management of traumatic brain injury.pubmed.ncbi.nlm.nih.gov
- The Epidemiology and Clinical Presentation of the Acute Imbalance Syndrome (AIS)-A Systematic Review and Meta-Analysis.pubmed.ncbi.nlm.nih.gov
- Transcranial Doppler Pulsatility Index and MRI Findings in Meningoencephalitis: A Pilot Observational Retrospective Cohort Study in Critically Ill Patients.pubmed.ncbi.nlm.nih.gov
- Autoimmune Glial Fibrillary Acidic Protein (GFAP) Astrocytopathy and Its Radiological Manifestations: A Case Report.pubmed.ncbi.nlm.nih.gov
- Retroclival Epidural Hematoma in Pediatric Head Trauma: A Case Report and Comprehensive Literature Review.pubmed.ncbi.nlm.nih.gov
- Traumatic basilar artery incarceration following longitudinal clival fracture: illustrative case.pubmed.ncbi.nlm.nih.gov
- Acute neutrophilic vasculitis (leukocytoclasia) in 36 COVID-19 autopsy brains.pubmed.ncbi.nlm.nih.gov
- Brain Midline Shift Measurement and Its Automation: A Review of Techniques and Algorithms.pubmed.ncbi.nlm.nih.gov
- Low-flow vascular malformations without arteriovenous shunting of the central nervous system: a pictorial review.pubmed.ncbi.nlm.nih.gov
- Imaging in scrub typhus - a pictorial review.pubmed.ncbi.nlm.nih.gov
- Spontaneous Non-Aneurysmal Convexity Subarachnoid Hemorrhage: A Scoping Review of Different Etiologies beyond Cerebral Amyloid Angiopathy.pubmed.ncbi.nlm.nih.gov
- Brain Shift Patterns: Upward, Lateral and Downward Herniation, Its Correlation with Clinical Patterns in Acute Intracranial Pathologies and Neurosurgical Management.pubmed.ncbi.nlm.nih.gov
- Anatomically Precise Microsurgical Resection of a Posterior Fossa Cerebellar Metastasis in an Elderly Patient with Preservation of Venous Outflow, Dentate Nucleus, and Cerebrospinal Fluid Pathways.pubmed.ncbi.nlm.nih.gov
- The spectrum of brain malformations and disruptions in twins.pubmed.ncbi.nlm.nih.gov
- Duret brainstem hemorrhage: chronological illustration and favorable outcome in a young trauma patient.pubmed.ncbi.nlm.nih.gov
- Brainstem Hemorrhage After Extradural Hematoma Evacuation: Myth or Truth?pubmed.ncbi.nlm.nih.gov
- Delayed neurological improvement in a patient with Duret hemorrhage secondary to an acute subdural hematoma: illustrative case.pubmed.ncbi.nlm.nih.gov
- Spontaneous hemorrhage of cavernous malformation in the region of the cochlear nucleus: A case report.pubmed.ncbi.nlm.nih.gov
- Resection of a thalamomesencephalic cavernous malformation via a retrosigmoid supracerebellar transtentorial approach: illustrative case.pubmed.ncbi.nlm.nih.gov
- Radiation-induced cavernous malformation arising within vestibular schwannoma manifesting as subarachnoid hemorrhage: Case report and literature review.pubmed.ncbi.nlm.nih.gov
- Recurrent brief positional vertigo as the initial presentation of medial branch of the posterior inferior cerebellar artery territory cerebellar infarction: a case report.pubmed.ncbi.nlm.nih.gov
- A Toothache That Was a Stroke: Acute Right Parietal Infarction Presenting As Isolated Left-Sided Odontogenic-Like Pain.pubmed.ncbi.nlm.nih.gov
- C3 spinal cord infarction associated with cervical ossification of the posterior longitudinal ligament presenting as a stroke mimic: illustrative case.pubmed.ncbi.nlm.nih.gov
- Correlation of Contusion Morphology and Volume With Functional Recovery and in Hospital Mortality in Traumatic Brain Injury.pubmed.ncbi.nlm.nih.gov
- The supracerebellar approach to pineal lesions: A review of history, evolution, and outcomes.pubmed.ncbi.nlm.nih.gov
- The Dynamics of Neuroinflammation in Traumatic Brain Injury: Molecular Markers Useful for Establishing the Post-Traumatic Interval in Forensic Practice.pubmed.ncbi.nlm.nih.gov
- Understanding Photon-Counting CT: Physics, Detector Technology, and Image Reconstructions.pubmed.ncbi.nlm.nih.gov
- Where Does the Signal Go? Technical Challenges of CT Perfusion in Lacunar and Infratentorial Stroke.pubmed.ncbi.nlm.nih.gov
- Spectral CT and Photon-counting Detector CT: Principles and Applications in Neuroradiology.pubmed.ncbi.nlm.nih.gov
- Diagnosis of Mild Traumatic Brain Injury: A Narrative Review of Advances in Neuroimaging and Patient-Reported Outcome Measures.pubmed.ncbi.nlm.nih.gov
- Pathophysiology-driven neuroimaging: decoding brain injury in sepsis.pubmed.ncbi.nlm.nih.gov
- Neurosarcoidosis Presenting With Cerebellar Hemorrhage and Spinal Cord Involvement: A Case Report.pubmed.ncbi.nlm.nih.gov
- A scoping review of stem cell models of leukodystrophies: advances in understanding pathophysiological mechanisms.pubmed.ncbi.nlm.nih.gov
- Bilateral hyperdense middle cerebral arteries: Stroke sign or not?pubmed.ncbi.nlm.nih.gov
- Enlarged Perivascular Spaces and Cerebral Small Vessel Disease in Spontaneous Intracerebral Hemorrhage Patients.pubmed.ncbi.nlm.nih.gov
- Cerebellum, or Not Cerebellum, That Was the Question.pubmed.ncbi.nlm.nih.gov
- Prognostic significance of contrast staining following mechanical thrombectomy in acute ischaemic stroke.pubmed.ncbi.nlm.nih.gov
- A case report of a neonate with Arnold Chiari II malformation.pubmed.ncbi.nlm.nih.gov
- Solving the Riddle of "Idiopathic" in Idiopathic Intracranial Hypertension and Normal Pressure Hydrocephalus: An Imaging Study of the Possible Mechanisms - Monro-Kellie 3.0.pubmed.ncbi.nlm.nih.gov
- Detection of third and sixth cranial nerve palsies with a novel method for eye tracking while watching a short film clip.pubmed.ncbi.nlm.nih.gov
- The neuropathology of traumatic brain injury.pubmed.ncbi.nlm.nih.gov
- Ballooned neurons in semi-recent severe traumatic brain injury.pubmed.ncbi.nlm.nih.gov
- Multifocal intracranial hemorrhage on emergency brain CT in a child with end-stage nephrotic syndrome.pubmed.ncbi.nlm.nih.gov
- Successfully treated delayed upward trans-tentorial herniation (UTTH) following ventriculoperitoneal shunt placement for an acute obstructive hydrocephalus secondary to midline posterior fossa mass in a low-resource setting: case report.pubmed.ncbi.nlm.nih.gov
- In-hospital unexpected cerebral herniation-New neurosurgical quality control standards: A case report.pubmed.ncbi.nlm.nih.gov
- Persistent Post-Traumatic Brain Injury Hiccups Unresponsive to Standard Agents: Resolution Associated With Levetiracetam Therapy.pubmed.ncbi.nlm.nih.gov
- Possible delayed neuronal death after seemingly successful evacuation of traumatic acute subdural hematoma: Image report.pubmed.ncbi.nlm.nih.gov
- Role of Magnetic Resonance Imaging in Acute Head Injury Patients with Normal Computed Tomography Brain Findings.pubmed.ncbi.nlm.nih.gov
- Beta-ketothiolase deficiency with progressive basal ganglia and extra basal ganglia involvement: CT-MRI correlation in a pediatric metabolic encephalopathy: A case report.pubmed.ncbi.nlm.nih.gov
- Diagnostic Pitfalls of CT in Malignant Superior Cerebellar Artery Infarction: Implications for Treatment Decisions and Future Management Strategies.pubmed.ncbi.nlm.nih.gov
- Ischemic Stroke as a Possible Initial Manifestation of Primary Sjögren's Syndrome: A Case Report.pubmed.ncbi.nlm.nih.gov
- Partial Oculomotor Nerve Palsy Revealing PDCD10-Related Familial Cerebral Cavernous Malformation in a Child.pubmed.ncbi.nlm.nih.gov
- Endoscopic transclival decompression for ventral brainstem tuberculous abscess: illustrative case.pubmed.ncbi.nlm.nih.gov
- Technical nuances of endoscopic transcortical transventricular fenestration for management of giant suprasellar arachnoid cysts in adults: illustrative cases.pubmed.ncbi.nlm.nih.gov
- A window into eye movement dysfunction following mTBI: A scoping review of magnetic resonance imaging and eye tracking findings.pubmed.ncbi.nlm.nih.gov
- Pathological neural networks and artificial neural networks in ALS: diagnostic classification based on pathognomonic neuroimaging features.pubmed.ncbi.nlm.nih.gov
- Microstructural brain injury in post-concussion syndrome after minor head injury.pubmed.ncbi.nlm.nih.gov
- Postmortem brain 7T MRI with minimally invasive pathological correlation in deceased COVID-19 subjects.pubmed.ncbi.nlm.nih.gov
- Neuroimaging Patterns of Intracranial Infections: Meningitis, Cerebritis, and Their Complications.pubmed.ncbi.nlm.nih.gov
- Neuroimaging standards for research into small vessel disease and its contribution to ageing and neurodegeneration.pubmed.ncbi.nlm.nih.gov
- Neuro-Optometric Rehabilitation to Prevent Post-concussion Visual Complications: A Case Report.pubmed.ncbi.nlm.nih.gov
- Continuum of Irreversible and Potentially Reversible Traumatic Brain Injury Sequelae: Axonal Injury and Hydrocephalus.pubmed.ncbi.nlm.nih.gov
Eğitim amaçlıdır; hasta başında tanı ve tedavi kararının yerine geçmez. İçerik yapay zekâ destekli bir süreçle güncel literatüre göre cümle cümle kaynaklarla karşılaştırıldı, ancak uzman radyolog incelemesinden geçmedi. Klinik kararlarda güncel kılavuzları, kurum protokollerini ve radyoloji raporunu esas alın.