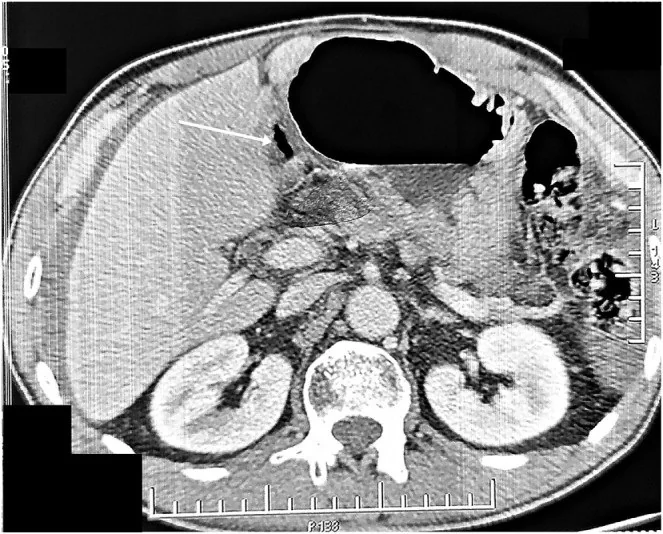
Özet
Marjinal ülser, gastrojejunostomi sonrasında en sık anastomozun jejunal tarafında veya hemen komşuluğunda gelişen mukozal defekttir. BT, özellikle acil başvuruda ülser çevresindeki fokal duvar değişikliği ve yağlı doku reaksiyonunu fark ettirebilir; perforasyon, koleksiyon ve aktif kanama gibi acil komplikasyonları da araştırır. BT ülseri kesin dışlamak veya mukozal krateri doğrulamak için endoskopinin yerini tutmaz. Perforasyon ya da kanama bulgularının atlanması acil klinik kötüleşmenin tanınmasını geciktirebilir.
Faz ve pencere
- Portal tanısal
- IV kontrastlı portal venöz kesitlerde gastrojejunostominin özellikle jejunal kenarında fokal duvar kalınlaşması, mukozal düzensizlik veya krater benzeri kontur değişikliği ve perianastomotik yağ çizgilenmesi aranır; perforasyon varsa komşu ekstralüminal gaz veya koleksiyon görülebilir. Bu bulgular mukozal ülseri kesinleştirmez.
- Kontrastsız tanısal
- BT'de anastomoz kenarında fokal duvar kalınlaşması, mukozal defekt veya çıkıntı ve komşu yağ çizgilenmesi izlenebilir; bu bulgular ülseri kesinleştirmez. BT bulguları ülseri kesinleştirmez; tanıda üst endoskopi altın standarttır ve şüpheli BT bulguları endoskopik değerlendirmeyi gündeme getirmelidir.
- Arteriyel tanısal
- Aktif kanama şüphesinde BT anjiyografi gastrojejunal anastomozdaki aktif arteriyel kanamayı gösterebilir; lümen içindeki hiperatenuan materyalin kanama olup olmadığını değerlendirmede kontrastsız seri yardımcı olabilir. BT, marjinal ülser tanısında birincil yöntem değildir.
Önerilen pencereler: Batın (G 400 / M 50), Yumuşak doku (G 400 / M 40).
BT bulguları
- Anastomozun jejunal kenarında fokal duvar kalınlaşması veya mukozal düzensizlik
- Krater benzeri lümen kontur düzensizliği — BT'de görülebilir; tek başına ülseri doğrulamaz
- Perianastomotik yağlı doku çizgilenmesi — inflamasyonu destekler, ancak BT'de tek başına özgül değildir
- Ülser kenarında fokal ödem veya çevresel duvar kontrastlanması
- Perforasyon işareti — gastrojejunostomi komşuluğunda sınırlı ekstralüminal gaz odağı veya doğrudan lümen duvar kesintisi
- Perianastomotik sıvı, kalın duvarlı koleksiyon ya da fistül traktı — komplike ülseri düşündürür
- Aktif kanama şüphesinde lümen içinde arteriyel kontrast ekstravazasyonu
- Skar ilişkili çıkış daralması ve proksimal poş stazı — kronik ülserin yapısal komplikasyonu olabilir
Normalde
Gastrojejunostomi katlantıları ülseri taklit edebilir; eşlik eden inflamasyonun olmaması, görülen değişikliğin hastanın ağrısının nedeni olma olasılığını azaltır. Gastrojejunostomi katlantıları marjinal ülseri taklit edebilir; eşlik eden inflamasyon yoksa görünüm bir katlantı veya iyileşmiş ülserle ilişkili olabilir.
Normal BT ile kıyasla
Aynı bölgenin, kaynak veri setinde patoloji içermediği belirtilen bir BT incelemesini kesit kesit kaydırın; organ sınırlarını açarak anatomiyi hasta görüntüsüyle karşılaştırın. Küçük rastlantısal bulgular tümüyle dışlanmamıştır.
Kaynak: TotalSegmentator v2.01 veri seti (Wasserthal ve ark., Radiology: Artificial Intelligence 2023), CC BY 4.0, vaka s0541; organ sınırları veri setinin otomatik segmentasyonundan, birleştirilerek sadeleştirildi. Görüntüler 2,5 mm kesit aralığına yeniden örneklendi.
Ayırıcı tanı
- Anastomoz katlantısı
- düzgün mukozal çıkıntı yapar; çevresel yağlı doku inflamasyonu ve krater biçimli duvar defekti eşlik etmez.
- Gastrojejunostomi darlığı
- lümen boyunca sabit daralma ve poş genişlemesi ön plandadır; mukozal ülser krateri şart değildir.
- Anastomoz kaçağı
- enterik kontrastın lümen dışına geçmesi veya daha yaygın perianastomotik gaz/sıvı görülür; ülserde doğrudan kaçak bulunmayabilir.
- Perforasyonsuz peptik ülser
- mide/duodenum mukozasında krater ve duvar reaksiyonu vardır; Roux-en-Y anastomoz kenarı hedefi değildir.
- Anastomoz nüksü
- düzensiz kitle benzeri duvar kalınlaşması veya lenf düğümleri olabilir; önceki kanser cerrahisi öyküsü ve seri incelemeler ayırıcıdır.
Tuzaklar
- BT'de yalnız hafif yağlı doku çizgilenmesi görülebilir; inflamasyonun az olması ülseri dışlamaz ve belirti sürüyorsa endoskopik korelasyon gerekir.
- Anastomoz kıvrımları veya iyileşmiş ülser, mukozal krater izlenimi oluşturabilir; çevresel yağ değişikliği yokluğu ve düzgün katlantı bu taklitçileri destekler.
- Marjinal ülser perforasyonunda gastrojejunostomi alanında gaz odağı görülebilir.
- Arteriyel ekstravazasyon aktif kanama şüphesi olmadan rutin bir ülser işareti değildir; fazı yalnız kanama sorusu klinik olarak varsa yorumla.
Kendini dene
Roux-en-Y hastasında BT'de gastrojejunostominin jejunal kenarında fokal kontur düzensizliği ve aynı yerde yağ çizgilenmesi var; lümen dışı kontrast ya da gaz yok. En olası açıklama nedir?
Cevabı göster
Marjinal ülser. Jejunal anastomoz kenarındaki fokal değişiklik ve lokal yağ çizgilenmesi marjinal ülseri destekler; BT bulguları özgül değildir ve mukozal ülserin doğrulanması endoskopiyle yapılır. Katlantı düzgün lümen çıkıntısıdır; bezoar intralüminal kitle, divertikül ise kese biçimli lümen devamlılığı gösterir.
Marjinal ülser şüphesi olan hastada BT portal venöz kesitte gastrik poş genişlemesi, anastomoz kenarında duvar kalınlaşması ve komşu yağ çizgilenmesi izleniyor. Bu bulgular en çok aşağıdakilerden hangisini düşündürür?
Cevabı göster
Marjinal ülser. BT'de gastrik poş genişlemesi, anastomoz kenarında fokal duvar kalınlaşması ve perianastomotik yağ çizgilenmesi marjinal ülseri düşündürür; ancak bu bulgular özgül değildir ve kesin tanı için üst endoskopisi şarttır.
Kaynaklar
Bu sayfadaki 41 cümle ve 2 quiz sorusu aşağıdaki kaynaklardan alıntılarla tek tek karşılaştırıldı; 13 cümle bu karşılaştırmada düzeltildi (2026-10-09).
- Prospective diagnosis of marginal ulceration following Roux-en-Y gastric bypass with computed tomographypmc.ncbi.nlm.nih.gov
- Marginal Ulcers after Roux-en-Y Gastric Bypass: Etiology, Diagnosis, and Managementpmc.ncbi.nlm.nih.gov
- Mini-Gastric Bypass to Control Morbid Obesity and Diabetes Mellitus: What Radiologists Need to Knowpmc.ncbi.nlm.nih.gov
- Perforated Marginal Ulcer.pubmed.ncbi.nlm.nih.gov
- S146-Jejunojejunal intussusception after roux-En-Y gastric bypass: a case series of 34 patients.pubmed.ncbi.nlm.nih.gov
- Perforated duodenal ulcers after Roux-Y Gastric Bypass.pubmed.ncbi.nlm.nih.gov
- Marginal ulcer causing delayed anastomotic perforation following one anastomosis gastric bypass (OAGB).pubmed.ncbi.nlm.nih.gov
- Non-Operative Approach to Contained Perforated Marginal Ulcers: A Systematic Review and Case Series.pubmed.ncbi.nlm.nih.gov
- The Surgical Technique of Primary Modified Fundoplication Using the Excluded Stomach with Simultaneous Gastric Bypass.pubmed.ncbi.nlm.nih.gov
- Gastric adenocarcinoma at the anastomotic site 50 years after gastrojejunostomy: A case report.pubmed.ncbi.nlm.nih.gov
- Retrocolic or Antecolic Roux-en-Y Reconstruction after Distal Gastrectomy: Which Is More Effective in the Prevention of Postoperative Gastroesophageal Reflux Disease.pubmed.ncbi.nlm.nih.gov
- Perforated marginal ulcer after gastric bypass for obesity: a systematic review.pubmed.ncbi.nlm.nih.gov
- Surgical management of marginal ulcer sequelae after Roux-en-Y gastric bypass: a single-center retrospective cohort study.pubmed.ncbi.nlm.nih.gov
- Treatment of a duodenal-caval fistula secondary to peptic ulcer disease.pubmed.ncbi.nlm.nih.gov
- Small bowel obstruction due to a phytobezoar thirty years after Roux-en-Y gastrojejunostomy: A case report.pubmed.ncbi.nlm.nih.gov
- Adhesions due to peritoneal carcinomatosis caused by a renal carcinoma leading to mechanical gastric outlet obstruction: a case report.pubmed.ncbi.nlm.nih.gov
- Pneumoperitoneum revealing pneumatosis cystoides intestinalis and stenosing pyloro-duodenal ulcer following trauma: A case report.pubmed.ncbi.nlm.nih.gov
- Surgical Management of Recurrent Gastrojejunocolic Fistula With Gastric Antrectomy and Bilateral Vagotomy.pubmed.ncbi.nlm.nih.gov
- Perforated marginal ulcers - what are the surgical options - simple closure or is definitive surgery needed? A case report.pubmed.ncbi.nlm.nih.gov
- Revisional Surgical Options After Single Anastomosis Sleeve Jejunal Bypass for Refractory Biliary Reflux: A Prospective Comparative Study Between Roux-en-Y Gastric Bypass and Reversal to Sleeve Gastrectomy.pubmed.ncbi.nlm.nih.gov
- Early and Late Complications After Sleeve Gastrectomy and Roux-en-Y Gastric Bypass: A Narrative Review.pubmed.ncbi.nlm.nih.gov
- Excluded-stomach Perforation after Roux-en-Y and One-anastomosis Gastric Bypass: A Systematic Review with Video-illustrated Case Report.pubmed.ncbi.nlm.nih.gov
- Complementary roles of <sup>18</sup>F-FDG and <sup>68</sup>Ga-pentixafor PET/CT in gastric MALT lymphoma.pubmed.ncbi.nlm.nih.gov
- Complication imaging after laparoscopic Roux-en-Y gastric bypass: clues to the diagnosis and pitfalls.pubmed.ncbi.nlm.nih.gov
- Post-Bariatric Surgery Complications and the Role of Endoscopic Intervention.pubmed.ncbi.nlm.nih.gov
- Laparoscopic gastric pouch resection and esophago-jejunostomy after gastric bypass: indications and outcomes.pubmed.ncbi.nlm.nih.gov
- Severe Gastric Outlet Obstruction From Gastric Remnant Ulceration and Stricture: A Rare Complication Manifesting 2 Decades After Roux-en-Y Gastric Bypass.pubmed.ncbi.nlm.nih.gov
- Early Markers Associated with Crohn's Disease in Emergency Department Patients with New-Onset Terminal Ileitis: An Exploratory Retrospective Cohort Study.pubmed.ncbi.nlm.nih.gov
- Topological Radiomics in Predicting Mucosal Healing and Activity Score of Crohn's Disease Using Multi-Task Deep Learning.pubmed.ncbi.nlm.nih.gov
- Comprehensive analysis of risk factors associated with submucosal invasion in patients with early-stage gastric cancer.pubmed.ncbi.nlm.nih.gov
- Abdominal apoplexy complicating ulcerative colitis: a case report of venous mesenteric hemorrhage.pubmed.ncbi.nlm.nih.gov
- Occult haemorrhagic shock due to hemomediastinum following percutaneous coronary intervention: a case report.pubmed.ncbi.nlm.nih.gov
- Pitfall in necrotizing pancreatitis: Organized hematoma with arteriovenous fistula mimicking a splenic artery pseudoaneurysm.pubmed.ncbi.nlm.nih.gov
- Delayed rupture of right external iliac artery pseudoaneurysm after removal of foreign body from small intestine: a case report.pubmed.ncbi.nlm.nih.gov
- Current insights into the diagnosis and management of small bowel bleeding.pubmed.ncbi.nlm.nih.gov
- Interventional embolization for hemorrhagic pleural effusion in an infant with kaposiform lymphangiomatosis: a case report.pubmed.ncbi.nlm.nih.gov
- Massive Psoas Muscle Bleeding from the Contralateral Lumbar Artery Obscured by a Lumbar Vertebra Fracture: A Case Report.pubmed.ncbi.nlm.nih.gov
- Transcatheter arterial embolization for traumatic adrenal hemorrhage with contrast extravasation: case series and literature review.pubmed.ncbi.nlm.nih.gov
- Spontaneous subcapsular hepatic hematoma with hepatic rupture and hemorrhage in the postpartum period: a case report and literature review.pubmed.ncbi.nlm.nih.gov
- CT-Centered Multimodality Imaging of Arterial Wall Fragility in Acute Aortic Syndromes: A Narrative Review of Imaging Markers and Clinical Implications.pubmed.ncbi.nlm.nih.gov
- Coronary Artery Disease and Preoperative Coronary Angiography in Elective Thoracic Endovascular Aortic Repair: A Retrospective Cohort Study.pubmed.ncbi.nlm.nih.gov
- Isolated gastrointestinal hereditary angioedema associated with a pathogenic <i>SERPING1</i> variant arising <i>de novo</i>: a case report.pubmed.ncbi.nlm.nih.gov
- Diagnostic and therapeutic challenges with malignant biliary tract and periampullary pathology in post-bariatric surgery.pubmed.ncbi.nlm.nih.gov
- Duodenal perforation in the excluded segment: twenty-five years post-Roux-en-Y gastric bypass surgery: a case report.pubmed.ncbi.nlm.nih.gov
- Mechanisms of aortic dissection: From pathological changes to experimental and <i>in silico</i> models.pubmed.ncbi.nlm.nih.gov
- Zygomatic Sialadenitis as a Rare Cause of Exophthalmos in a Dog.pubmed.ncbi.nlm.nih.gov
- Atypical presentation of an impending thoracoabdominal aortic aneurysm rupture: The hyperattenuating crescent sign as a life-saving imaging feature.pubmed.ncbi.nlm.nih.gov
- Spectrum of Neuroimaging Findings in CNS Lymphoproliferative Disorders.pubmed.ncbi.nlm.nih.gov
- Emergency Roux-en-Y Biliary Bypass and Duodenal Exclusion for Perforated Duodenal Ulcer.pubmed.ncbi.nlm.nih.gov
- Endoscopic Management of Post-Bariatric Surgery Complications: Diagnostic Work-Up and Innovative Approaches for Leak, Fistula, and Stricture Management.pubmed.ncbi.nlm.nih.gov
- Imaging after Pancreaticoduodenectomy: How Can the Radiologist Help the Surgeon.pubmed.ncbi.nlm.nih.gov
- Overt gastrointestinal bleeding secondary to left inferior phrenic artery pseudoaneurysm postgastric bypass surgery.pubmed.ncbi.nlm.nih.gov
- Superior mesenteric artery syndrome complicated with duodenal bulb-descending ulcerative stricture: a case report and literature review.pubmed.ncbi.nlm.nih.gov
- Case Report: Intrahepatic bile duct injury during adhesiolysis mimicking anastomotic leak.pubmed.ncbi.nlm.nih.gov
- Imaging of pediatric gastrostomy tube malposition: Pearls and pitfalls.pubmed.ncbi.nlm.nih.gov
- Etiologies, outcomes, and predictors of postoperative complications in the surgical management of extrahepatic biliary obstruction: a study at Tikur Anbesa specialized hospital, Ethiopia.pubmed.ncbi.nlm.nih.gov
- Computed Tomography Imaging of Thoracic Aortic Surgery: Distinguishing Life-Saving Repairs from Life-Threatening Complications.pubmed.ncbi.nlm.nih.gov
- Sodium Zirconium Cyclosilicate in the Gastrointestinal Tract Mimicking an Acute Gastrointestinal Bleed on CT.pubmed.ncbi.nlm.nih.gov
- Patterns of injury and violence in Yaoundé Cameroon: an analysis of hospital data.pubmed.ncbi.nlm.nih.gov
- Intermediate-Term Oncological, Anastomotic and Nutritional Outcomes of the Sutureless L-Shaped Esophagojejunostomy with Endoscopic Assistance (SLEJ) in Totally Laparoscopic Total Gastrectomy: A Follow-Up Analysis of This Technique.pubmed.ncbi.nlm.nih.gov
- The role of enteroscopy in the diagnosis and interventional management of small intestine diseases.pubmed.ncbi.nlm.nih.gov
- Best Practice Recommendations for Infertility Management.pubmed.ncbi.nlm.nih.gov
- Mucormycosis caused by unusual mucormycetes, non-Rhizopus, -Mucor, and -Lichtheimia species.pubmed.ncbi.nlm.nih.gov
- Stricturing Diseases of the Gastrointestinal Tract-Current Clinical Practice.pubmed.ncbi.nlm.nih.gov
- Pancreas-preserving duodenal resections vs pancreatoduodenectomy for groove pancreatitis. Should we revisit treatment algorithm for groove pancreatitis?pubmed.ncbi.nlm.nih.gov
- The Association of Polish Surgeons (APS) clinical guidelines for the use of laparoscopy in the management of abdominal emergencies. Part II.pubmed.ncbi.nlm.nih.gov
- Acute pancreatitis: A review of diagnosis, severity prediction and prognosis assessment from imaging technology, scoring system and artificial intelligence.pubmed.ncbi.nlm.nih.gov
- Case Report: Marjolin ulcer characterized by squamous cell carcinoma arising from chronic wounds: clinical features, diagnostic and therapeutic challenges, and insights-a report of four cases.pubmed.ncbi.nlm.nih.gov
- Radical Tumor Denervation Activates Potent Local and Global Cancer Treatment.pubmed.ncbi.nlm.nih.gov
- Through-the-scope twin clip for closure of gastric endoscopic full-thickness resection defects: a retrospective comparative study.pubmed.ncbi.nlm.nih.gov
- Conservative management of delayed perforation after colorectal endoscopic submucosal dissection: a single-center experience.pubmed.ncbi.nlm.nih.gov
- Transcolonic Endoscopic Appendectomy: A Single-Step "Two-In-One" Approach for Recurrent Appendicitis With Appendiceal Orifice Lesions.pubmed.ncbi.nlm.nih.gov
- Endovascular Coil Embolization of a Ruptured Gastroduodenal Artery Aneurysm: A Case Report.pubmed.ncbi.nlm.nih.gov
- Diagnostic Value of the Split-Bolus CT Protocol in Blunt Abdominal Trauma: Comparison With Standard Portal Venous Phase Imaging.pubmed.ncbi.nlm.nih.gov
- Beyond Bone Health: Exploring the "Heart-Brain-Bone" Axis Modulated by Lipid-Soluble Nutrients (Omega-3, Vitamin D3, and Vitamin K2).pubmed.ncbi.nlm.nih.gov
- Case Report: Single-incision laparoscopic sleeve gastrectomy plus jejunojejunal bypass for the treatment of type 2 diabetes in patients with obesity: a case series and review.pubmed.ncbi.nlm.nih.gov
- Artery first approach in robotic pancreatoduodenectomy: right-sided uncinate first technique.pubmed.ncbi.nlm.nih.gov
- Ligation site of the inferior mesenteric vein in laparoscopic radical resection of rectal cancer: a study protocol for a multicenter randomized-controlled trial.pubmed.ncbi.nlm.nih.gov
- Orbital masses: a review of CT imaging characteristics.pubmed.ncbi.nlm.nih.gov
- Navigating complexity: review and updates of endometriosis and adenomyosis imaging.pubmed.ncbi.nlm.nih.gov
- Case Report: Cystic fibrosis transmembrane conductance regulator gene heterozygous variation presenting with abdominal pain and hepatopancreatic lesions in a child.pubmed.ncbi.nlm.nih.gov
- Lower extremity infections: Essential anatomy and multimodality imaging findings.pubmed.ncbi.nlm.nih.gov
- Medical hyperspectral imaging: an updated review of technology advancements and biomedical applications.pubmed.ncbi.nlm.nih.gov
- MDCT Imaging of Non-Traumatic Thoracic Aortic Emergencies and Its Impact on Diagnosis and Management-A Reappraisal.pubmed.ncbi.nlm.nih.gov
- Ulcerative gastric MALT lymphoma with marked eosinophilic infiltration: a case report.pubmed.ncbi.nlm.nih.gov
- Case Report: Spectral CT characterization of giant esophageal schwannoma with reactive lymphoid hyperplasia mimicking lymphoproliferative disease.pubmed.ncbi.nlm.nih.gov
- Retrospective Three-Dimensional CT Reconstruction in Complex Emergency Hepato-Pancreato-Biliary Surgery: A Proof-of-Concept Case Series with Anatomical Concordance to Intraoperative Findings and Narrative Review.pubmed.ncbi.nlm.nih.gov
- Technique-Driven and Patient-Specific Variations in Complications of Mastectomy with Immediate Breast Reconstruction: An Evidence-Based Review.pubmed.ncbi.nlm.nih.gov
- Intrapleural Fibrinolytic Therapy in the Management of Pediatric Pleural Empyema: A Narrative Review.pubmed.ncbi.nlm.nih.gov
- Risk-adapted first-line therapy selection in advanced EGFR-mutant NSCLC: a practical clinical algorithm integrating tumor biology and patient factors.pubmed.ncbi.nlm.nih.gov
- Wire Injury-Induced Moderate Aortic Valve Stenosis in Mice Is Accompanied by a Chronic Systemic Inflammatory Reaction.pubmed.ncbi.nlm.nih.gov
- The pathogenesis of cerebral small vessel disease and vascular cognitive impairment.pubmed.ncbi.nlm.nih.gov
- Rare Delayed Complications of Laparoscopic Adjustable Gastric Band Erosion: Contained Gastric Perforation and Bleeding Pseudoaneurysm.pubmed.ncbi.nlm.nih.gov
- Endoscopic gastric plication complications: early hemorrhagic event and late suture dehiscence. A two-case series.pubmed.ncbi.nlm.nih.gov
- Recurrent ileocolic variceal hemorrhage treated with superselective Onyx embolization: A case report.pubmed.ncbi.nlm.nih.gov
- Advanced management of postoperative hemorrhage following gastric bypass surgery through super-selective celiac artery coil embolization.pubmed.ncbi.nlm.nih.gov
- Cross-sectional imaging after pancreatic surgery: The dialogue between the radiologist and the surgeon.pubmed.ncbi.nlm.nih.gov
- Complications of lymphoma in the abdomen and pelvis: clinical and imaging review.pubmed.ncbi.nlm.nih.gov
- Laparoscopic Reversal of Gastric Bypass: A Retrospective Review.pubmed.ncbi.nlm.nih.gov
- Gastric infarction following gastric bypass surgery.pubmed.ncbi.nlm.nih.gov
- Robot-Assisted Completion Total Gastrectomy for Remnant Gastric Cancer after Double-Tract Reconstruction with an Intracorporeal Jejunal Delta-Shaped Anastomosis: A Case Report.pubmed.ncbi.nlm.nih.gov
- Antegrade Jejunal Intussusception at the Bilopancreatic Limb Jejunojejunostomy After Laparoscopic Distal Gastrectomy With Roux-en-Y Reconstruction: A Case Report.pubmed.ncbi.nlm.nih.gov
- Laparoscopic Reversal of One-Anastomosis Gastric Bypass After Sleeve Gastrectomy: A Case Report.pubmed.ncbi.nlm.nih.gov
Eğitim amaçlıdır; hasta başında tanı ve tedavi kararının yerine geçmez. İçerik yapay zekâ destekli bir süreçle güncel literatüre göre cümle cümle kaynaklarla karşılaştırıldı, ancak uzman radyolog incelemesinden geçmedi. Klinik kararlarda güncel kılavuzları, kurum protokollerini ve radyoloji raporunu esas alın.