
Özet
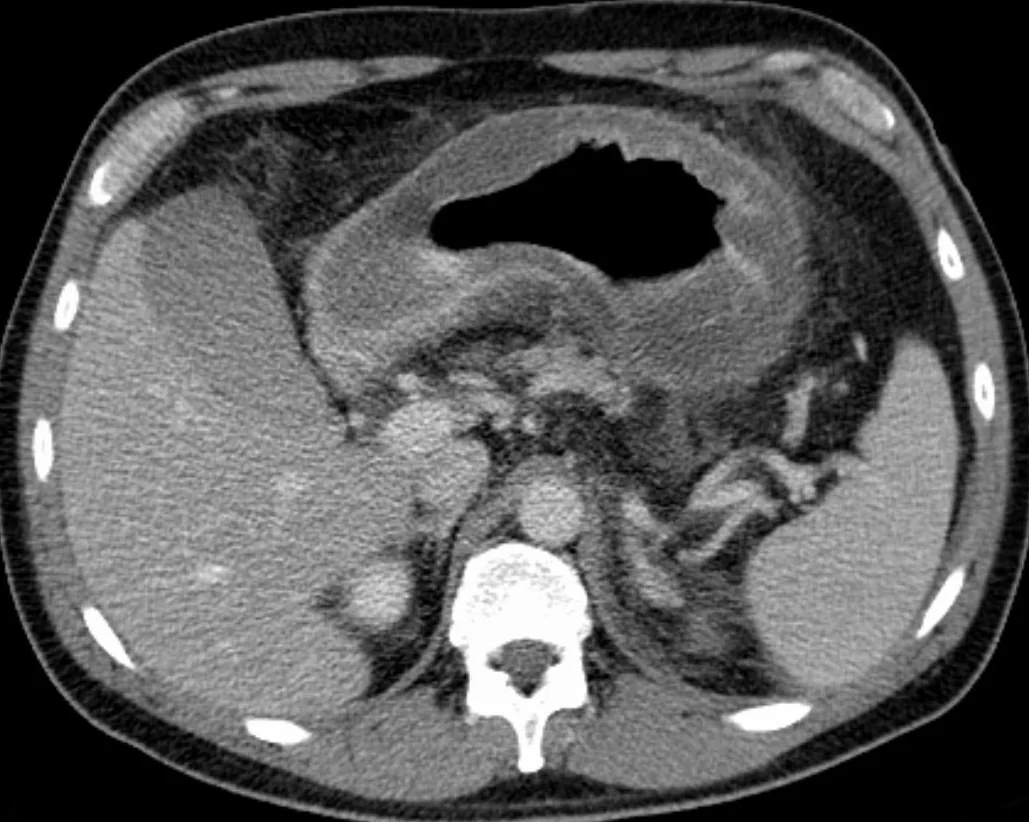
Gastrit ve gastroduodenit, mide ya da mide ile proksimal duodenum mukozasının farklı nedenlerle gelişen inflamasyonudur; tanı çoğunlukla klinik ve endoskopiktir. BT, özellikle acil başvuruda duvar-katlantı kalınlaşmasını, mukozal hiperemiyi ve submukozal ödemi gösterebilir, ancak inflamasyonun nedenini tek başına belirleyemez. Katmanlı duvar görünümü ve çevresel inflamasyon gastriti destekler; fokal kitle, ülser, perforasyon ve çıkış tıkanıklığı ayrıca araştırılmalıdır. Bu komplikasyonları atlamak kanama, obstrüksiyon veya perforasyonun tanınmasını geciktirebilir.
Faz ve pencere
- Arteriyel
- Arteriyel seri çekilmişse hiperemik mukoza belirgin kontrastlanabilir; ödemli düşük atenüasyonlu submukoza ile katmanlı/halo görünümü seçilebilir. Bu görünüm özgül değildir ve gastrit değerlendirmesi için arteriyel faz çoğu kez gerekli değildir; mide distansiyonu yetersizse duvar kalınlığı abartılı görünebilir.
- Portal tanısal
- Rutin kontrastlı incelemenin portal venöz fazında duvar ve katlantı kalınlaşması, mukozal hiper-kontrastlanma ile submukozal ödemin katmanlı görünümü, perigastrik/periduodenal yağlı doku reaksiyonu ve sıvı değerlendirilebilir; bulgular gastriti destekler fakat endoskopik doğrulama yerine geçmez.
Önerilen pencereler: Batın (G 400 / M 50), Yumuşak doku (G 400 / M 40).
BT bulguları
- Mide duvarı ve rugaelerde düzgün, yaygın ya da segmental kalınlaşma görülebilir.
- Hiperemik mukoza parlak kontrastlanırken submukozal ödem düşük atenüasyonlu bant oluşturabilir; bu mural stratifikasyon/halo görünümüdür.
- Perigastrik yağda hafif bulanıklık inflamasyonu destekler ancak etiyolojiye özgü değildir.
- Gastroduodenitte duodenum bulbusu veya ikinci bölüm duvarında kalınlaşma ve periduodenal yağ reaksiyonu eşlik edebilir.
- Ülser varsa mukozal kontrast çizgisinde fokal kesinti veya lümene açılan niş aranır.
- Pilorik ödem/stenoz ile proksimal mide distansiyonu çıkış obstrüksiyonu olasılığını artırır.
- Mide duvarı içinde gaz varsa duvar ödemi, perigastrik inflamasyon ve portal venöz gazı değerlendir; enfizemli gastrit ile gastrik amfizemi klinik tablo ve eşlik eden BT bulgularıyla ayır. Perforasyon için duvar defekti, ekstraluminal hava veya kaçağı ayrıca ara.
Normalde
Normal distandü mide duvarı düzgün konturlu, rugaeleri ince ve düzenlidir; kontrastlı incelemede mukoza ile submukoza arasında belirgin ödem bandı ve çevre yağ kirlenmesi görülmez. Antrumun fizyolojik düzgün kalınlığını gastrit lehine yorumlamadan önce korpus distansiyonu ve duodenum bulbusunun duvar-katlantı görünümüyle karşılaştır. Yeterince distandü midede duvar kalınlığı korpusta genellikle 5 mm’yi, antrumda 12 mm’yi aşmaz; antrum daha kalın ve peristaltik olabildiğinden ölçümü distansiyon ve kesitler boyunca süreklilikle birlikte değerlendir.
Normal BT ile kıyasla
Aynı bölgenin, kaynak veri setinde patoloji içermediği belirtilen bir BT incelemesini kesit kesit kaydırın; organ sınırlarını açarak anatomiyi hasta görüntüsüyle karşılaştırın. Küçük rastlantısal bulgular tümüyle dışlanmamıştır.
Kaynak: TotalSegmentator v2.01 veri seti (Wasserthal ve ark., Radiology: Artificial Intelligence 2023), CC BY 4.0, vaka s0541; organ sınırları veri setinin otomatik segmentasyonundan, birleştirilerek sadeleştirildi. Görüntüler 2,5 mm kesit aralığına yeniden örneklendi.
Ayırıcı tanı
- Gastrik adenokarsinom
- fokal asimetrik/nodüler kalınlaşma, omuzlanma, linitis plastika biçiminde yaygın rijit duvar veya metastatik bulgular şüphe uyandırır.
- Mide lenfoması
- yaygın ya da segmental belirgin duvar kalınlaşması ve orantısız lenfadenopati görülebilir; tek başına BT kesin ayrım sağlamaz.
- Mide çıkış obstrüksiyonu
- antrum/pilor düzeyinde sabit geçiş ve proksimal mide distansiyonu inflamatuvar duvar değişikliğine eşlik edebilir.
- Konjestif gastropati
- portal hipertansiyon varlığında gelişen ve mikroskobik olarak kapiller/venül genişlemeleri ile karakterize mukoza değişikliğidir; tanı genellikle endoskopik veya histolojik bulgularla konur.
- Peptik ülser
- fokal mukozal kesinti, lümene açılan niş ve lokalize çevre yağ reaksiyonu öne çıkar.
Tuzaklar
- Mural stratifikasyon gastrit için destekleyicidir fakat özgül değildir; tümör ve sistemik ödem de benzer katmanlaşma yapabilir.
- Kollabe mide veya peristaltik antrum yalancı kalın duvar oluşturabilir; kesitler boyunca sabit kalıp kalmadığını ve düzlem değişince konturun açılıp açılmadığını kontrol et.
- BT normal olsa da yüzeyel gastrit dışlanmaz; mukozal tanı gerektiğinde endoskopi referans yöntemdir.
- Duvar ödemli diye ülser/perforasyon dışlanmaz; özellikle fokal niş, çevresel serbest hava ve pilorik geçişi ayrıca ara.
Kendini dene
Epigastrik ağrıda BT'de yaygın mukoza hiper-kontrastlanması ve düşük atenüasyonlu submukoza var. En uygun yorum hangisidir?
Cevabı göster
Gastrit ile uyumlu görünüm. Hiperemik mukoza ile ödemli submukozanın katmanlı görünümü gastriti destekler, ancak tek başına kesin tanı değildir. Diğer seçeneklerde fokal kitle, rotasyon veya intraluminal materyal beklenir.
Antrumda asimetrik nodüler kalınlaşma, omuzlanma ve perigastrik infiltrasyon görülüyor. Hangi tanı özellikle dışlanmalıdır?
Cevabı göster
Gastrik adenokarsinom. Fokal asimetri, omuzlanma ve infiltratif kontur tümör şüphesini artırır ve endoskopik değerlendirme gerektirir. Basit inflamasyon daha sık düzgün/katmanlıdır; içerik duvar kaynaklı kalınlaşma yapmaz, divertikül fundustan dışa keseleşmedir.
İlgili konular
Kaynaklar
Bu sayfadaki 40 cümle ve 2 quiz sorusu aşağıdaki kaynaklardan alıntılarla otomatik olarak karşılaştırıldı; 1 cümle bu karşılaştırmada düzeltildi (2026-10-09).
- Multimodality imaging of adult gastric emergencies: A pictorial reviewpmc.ncbi.nlm.nih.gov
- Imaging of non-neoplastic duodenal diseases. A pictorial review with emphasis on MDCTpmc.ncbi.nlm.nih.gov
- Non-perforated peptic ulcer disease: multidetector CT findings, complications, and differential diagnosispmc.ncbi.nlm.nih.gov
- Yttrium-90 trans-arterial radioembolization in advanced-stage HCC: The impact of portal vein thrombosis on survival.pubmed.ncbi.nlm.nih.gov
- Gastric ischaemia as an unusual presentation of median arcuate ligament compression syndrome.pubmed.ncbi.nlm.nih.gov
- Subarachnoid hemorrhage in a case of segmental arterial mediolysis with coexisting intracranial and intraabdominal aneurysms.pubmed.ncbi.nlm.nih.gov
- Unusual Presentation of Helicobacter pylori Infection as PSMA-Avid Gastric Mass.pubmed.ncbi.nlm.nih.gov
- Gastroduodenal pathology in patients with asymptomatic gallbladder stones.pubmed.ncbi.nlm.nih.gov
- Severe cytomegalovirus gastritis after pembrolizumab in a patient with melanoma.pubmed.ncbi.nlm.nih.gov
- [Atherosclerosis of mesenteric arteries in patients with infrainguinal arterial disease].pubmed.ncbi.nlm.nih.gov
- Management of cytomegalovirus reactivation in a patient with immunotherapy-induced gastritis.pubmed.ncbi.nlm.nih.gov
- Cytomegalovirus gastritis as a rare adverse event during combined ipilimumab and nivolumab in a patient with melanoma.pubmed.ncbi.nlm.nih.gov
- Late onset of nivolumab-induced severe gastroduodenitis and cholangitis in a patient with stage IV melanoma.pubmed.ncbi.nlm.nih.gov
- TLR1 Polymorphism Associations with Gastric Mucosa Morphologic Patterns on Magnifying NBI Endoscopy: a Prospective CrossSectional Study.pubmed.ncbi.nlm.nih.gov
- Gastrogastric intussusception and acute pancreatitis caused by a large pyloric gland adenoma treated with endoscopic submucosal dissection.pubmed.ncbi.nlm.nih.gov
- Anorexia nervosa manifesting as massive ascites, hypercholesterolemia, and sequential binge eating in an 11-year-old girl: A case report.pubmed.ncbi.nlm.nih.gov
- [A case of corrosive gastritis caused by accidental ingestion of calcium chloride that resulted in gastric stenosis and penetration].pubmed.ncbi.nlm.nih.gov
- Cytomegalovirus gastritis in an immunocompetent host: insights into gut viral pathogenesis and mucosal barrier disruption.pubmed.ncbi.nlm.nih.gov
- Azathioprine-Induced Hypersensitivity Syndrome Presenting as Sepsis-Like Syndrome in a Patient With Mucous Membrane Pemphigoid: A Report of a Rare Case.pubmed.ncbi.nlm.nih.gov
- Severe upper gastrointestinal involvement in ulcerative colitis successfully treated with sequential therapy using intravenous tacrolimus and upadacitinib: a case report.pubmed.ncbi.nlm.nih.gov
- Severe gastrointestinal manifestations in childhood-onset lupus: A single-center cohort and review of the literature.pubmed.ncbi.nlm.nih.gov
- Diagnosis of small bowel inflammation using small bowel capsule endoscopy combined with abdominal CT scan.pubmed.ncbi.nlm.nih.gov
- Hypertrophic Pyloric Stenosis in an Adolescent Girl: An Atypical Presentation of an Unexpected Disease.pubmed.ncbi.nlm.nih.gov
- Narrative review of the role of gastroenterologist in the diagnosis, treatment and palliation in gastric and gastroesophageal cancer.pubmed.ncbi.nlm.nih.gov
- Non-perforated peptic ulcer disease: multidetector CT findings, complications, and differential diagnosis.pubmed.ncbi.nlm.nih.gov
- From Childhood Ingestion to Adult Obstruction: A Long-Retained Synthetic Gastric Foreign Body.pubmed.ncbi.nlm.nih.gov
- Delayed diagnosis of vascular compression syndrome mimicking chronic gastritis: a case report.pubmed.ncbi.nlm.nih.gov
- Excluded-stomach Perforation after Roux-en-Y and One-anastomosis Gastric Bypass: A Systematic Review with Video-illustrated Case Report.pubmed.ncbi.nlm.nih.gov
- Multisystem Imaging Manifestations of COVID-19, Part 2: From Cardiac Complications to Pediatric Manifestations.pubmed.ncbi.nlm.nih.gov
- International Harmonization of Nomenclature and Diagnostic Criteria (INHAND): Non-proliferative and Proliferative Lesions of the Non-human Primate ( M. fascicularis ).pubmed.ncbi.nlm.nih.gov
- Guidelines for the Prevention and Treatment of Opportunistic Infections among HIV-exposed and HIV-infected children: recommendations from CDC, the National Institutes of Health, the HIV Medicine Association of the Infectious Diseases Society of America, the Pediatric Infectious Diseases Society, and the American Academy of Pediatrics.pubmed.ncbi.nlm.nih.gov
- Research progress on the application of dual energy CT in gastric diseases.pubmed.ncbi.nlm.nih.gov
- EACR 2025 Congress: Innovative Cancer Science, 16-19 June 2025.pubmed.ncbi.nlm.nih.gov
- Patterns of injury and violence in Yaoundé Cameroon: an analysis of hospital data.pubmed.ncbi.nlm.nih.gov
- Pyloric Stenosis: A Rare Manifestation of Crohn's Disease.pubmed.ncbi.nlm.nih.gov
- Portal hypertensive gastropathy: A systematic review of the pathophysiology, clinical presentation, natural history and therapy.pubmed.ncbi.nlm.nih.gov
- Perigastric appendagitis mimicking biliary colic: Recognition of the central dot sign on CT.pubmed.ncbi.nlm.nih.gov
- Phlegmonous Gastritis During Consolidation Therapy With High-Dose Cytarabine and FLT3 Inhibitor in FLT3-ITD-Mutated Acute Myeloid Leukemia.pubmed.ncbi.nlm.nih.gov
- Gastrointestinal mucormycosis with no classical immunosuppression and the potential for Qat leaves chewing as an unidentified risk factor: a case report.pubmed.ncbi.nlm.nih.gov
- Evidence-based, cost-effective management of gastric outlet obstruction: An algorithm of the Journal of Trauma and Acute Care Surgery , Emergency General Surgery Algorithms Work Group.pubmed.ncbi.nlm.nih.gov
- Stricturing Diseases of the Gastrointestinal Tract-Current Clinical Practice.pubmed.ncbi.nlm.nih.gov
- The Diagnostic Challenge of Crohn's Disease With Initial Duodenal Involvement: Two Cases and Literature Review.pubmed.ncbi.nlm.nih.gov
- Emphysematous gastritis: The silent storm within the stomach wall.pubmed.ncbi.nlm.nih.gov
- Emphysematous gastritis: The diagnostic challenges and variable outcomes.pubmed.ncbi.nlm.nih.gov
- CT of acute abdomen in the elderly.pubmed.ncbi.nlm.nih.gov
- An Under-Recognised Rapidly Fatal Condition: Phlegmonous Gastritis.pubmed.ncbi.nlm.nih.gov
- The Great Mimicker of Gastric Cancer: A Case Report of Ménétrier's Disease.pubmed.ncbi.nlm.nih.gov
- Catching the GIST: Massive Gastrointestinal Stromal Tumor Presenting as Acute Dyspnea.pubmed.ncbi.nlm.nih.gov
- 68 Ga-DOTA-FAPI-04 PET/MR in the Evaluation of Gastric Carcinomas: Comparison with 18 F-FDG PET/CT.pubmed.ncbi.nlm.nih.gov
- A Fibroblast Activation Protein Inhibitor (FAPI)-Avid Gastric Antral Mass Mimicking Advanced Gastric Cancer: A Case of Presumed Inflamed Gastric Ectopic Pancreas.pubmed.ncbi.nlm.nih.gov
- Case Report: pulmonary MALT lymphoma with <i>BIRC3::MALT1</i> fusion and indeterminate PET/CT findings.pubmed.ncbi.nlm.nih.gov
- Case report: phlegmonous gastritis after endoscopic mucosal resection for a Helicobacter pylori-naïve foveolar-type gastric adenoma with a raspberry-like appearance.pubmed.ncbi.nlm.nih.gov
- Gastric Antral Web as an Uncommon Cause of Gastric Outlet Obstruction in an Adult Female Patient: A Case Report of a Rare Medical Condition and a Review of the Literature.pubmed.ncbi.nlm.nih.gov
- Endoscopic ultrasound-guided gastroenterostomy for the treatment of malignant gastric outlet obstruction in a 3-year-old boy.pubmed.ncbi.nlm.nih.gov
- Review of COVID-19, part 1: Abdominal manifestations in adults and multisystem inflammatory syndrome in children.pubmed.ncbi.nlm.nih.gov
- Pathological diagnosis is maybe non-essential for special gastric cancer: case reports and review.pubmed.ncbi.nlm.nih.gov
- Biomarkers in Gastric Cancer: Blood Biomarkers, Liquid Biopsy, Artificial Intelligence, and Risk-Stratified Care.pubmed.ncbi.nlm.nih.gov
- Endoscopic and Histological Diagnosis of Gastrointestinal Amyloidosis: A Narrative Review.pubmed.ncbi.nlm.nih.gov
- Management of Gastric Precancerous Lesions and Early Cancer: Practice-Oriented Answers to Clinical Questions.pubmed.ncbi.nlm.nih.gov
- Long-term safety and effectiveness of the "OptEase" vena cava filter.pubmed.ncbi.nlm.nih.gov
- Cholecystogastric fistula masquerading as gastrointestinal stromal tumour: Unusual presentation of gallbladder adenomyomatosis - a case report.pubmed.ncbi.nlm.nih.gov
- Fulminant Multisystem IgA Vasculitis With Diffuse Alveolar Hemorrhage, Severe Gastrointestinal Hemorrhage, Paralytic Ileus, and Renal Involvement in an Adolescent: A Case Report.pubmed.ncbi.nlm.nih.gov
- Imaging of intestinal vasculitis focusing on MR and CT enterography: a two-way street between radiologic findings and clinical data.pubmed.ncbi.nlm.nih.gov
- Many faces of acute bowel ischemia: overview of radiologic staging.pubmed.ncbi.nlm.nih.gov
- Imaging side effects and complications of chemotherapy and radiation therapy: a pictorial review from head to toe.pubmed.ncbi.nlm.nih.gov
- Does laparoscopic surgery decrease the risk of atrial fibrillation after foregut surgery?pubmed.ncbi.nlm.nih.gov
- Xanthogranulomatous cholecystitis: diagnostic complexity and review of the literature.pubmed.ncbi.nlm.nih.gov
- Management of Immune-Related Adverse Events in Patients Treated With Immune Checkpoint Inhibitor Therapy: American Society of Clinical Oncology Clinical Practice Guideline.pubmed.ncbi.nlm.nih.gov
- Spontaneous bacteremia and spontaneous bacterial peritonitis share similar prognosis in patients with cirrhosis: a cohort study.pubmed.ncbi.nlm.nih.gov
- Commentary: an eye on PET quantification.pubmed.ncbi.nlm.nih.gov
- Ischemic Gastroduodenitis: Navigating the Challenges of Enteral Nutrition Resumption.pubmed.ncbi.nlm.nih.gov
- ERDHEIM-Chester Disease: Two Fatal Cases With Unusual Presentations.pubmed.ncbi.nlm.nih.gov
- A Rare Case of Motor Neuropathy Secondary to Non-Hodgkin Lymphoma.pubmed.ncbi.nlm.nih.gov
- Keratinizing squamous cell carcinoma of the distal Esophagus in a young adult woman with celiac disease: a case report.pubmed.ncbi.nlm.nih.gov
- Acute Intestinal Obstruction from Small Bowel Stricture following Superior Mesenteric and Portal Vein Thrombosis: A Case Report.pubmed.ncbi.nlm.nih.gov
- Endo-hepatology: Bridging the gap between lumen and liver.pubmed.ncbi.nlm.nih.gov
- Portal hypertensive enteropathy: multimodality assessment through computed tomography and magnetic resonance enterography.pubmed.ncbi.nlm.nih.gov
- A Misplaced Pocket of Air: Intramural Gastric Air Most Consistent With Gastric Emphysema.pubmed.ncbi.nlm.nih.gov
- Geriatric Patient Successfully Managed With Conservative Therapy Despite Portal Venous Gas.pubmed.ncbi.nlm.nih.gov
- Not All Gastric Air Is Equal: A Case Report Highlighting the Difficulty in Distinguishing Between Benign and Lethal Gastric Pneumatosis.pubmed.ncbi.nlm.nih.gov
- Pneumopericardium and multicompartmental air dissemination after colorectal endoscopic resection managed conservatively: a case report.pubmed.ncbi.nlm.nih.gov
- Atypical Presentation of Boerhaave Syndrome with Left Shoulder Pain as the Initial Manifestation: A Case Report.pubmed.ncbi.nlm.nih.gov
- Methods of Surgical Repair for Iatrogenic Sigmoid Colon Perforation Following Colonoscopy: A Case Report and Literature Review.pubmed.ncbi.nlm.nih.gov
- Evaluation of Endoscopic Findings in Gastrointestinal Tract Wall Thickening Detected on Abdominal Radiological Imaging: A Two-Center Retrospective Descriptive Study.pubmed.ncbi.nlm.nih.gov
- Imaging features of bronchogenic cyst of the stomach: A case report with literature review.pubmed.ncbi.nlm.nih.gov
- Research Progress on the Efficacy and Mechanism of Acupuncture in Treating Chronic Gastritis.pubmed.ncbi.nlm.nih.gov
Eğitim amaçlıdır; hasta başında tanı ve tedavi kararının yerine geçmez, tıbbi tavsiye değildir. Metinler yapay zekâ desteğiyle yazıldı ve otomatik bir adımda kaynak alıntılarıyla karşılaştırıldı; bu bir tıbbi doğrulama değildir ve içerik uzman radyolog incelemesinden geçmedi. Klinik kararlarda güncel kılavuzları, kurum protokollerini ve radyoloji raporunu esas alın.