Özet
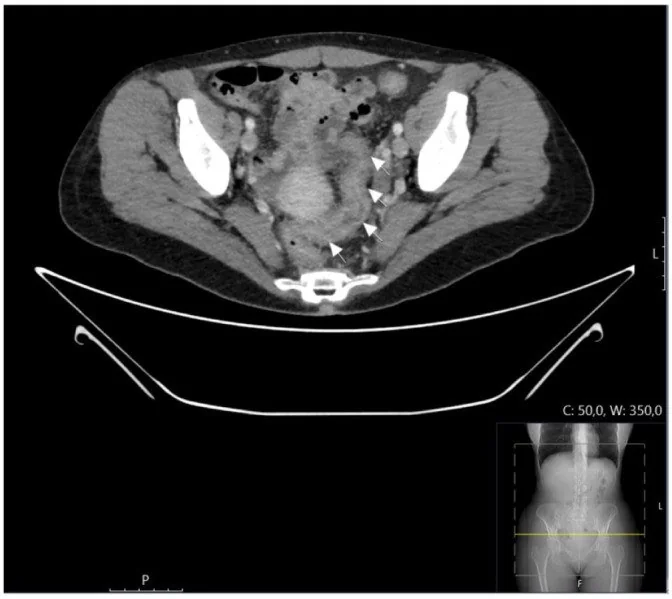
İmmün kontrol noktası inhibitörü kullanan ve karın ağrısı ya da ishal gelişen hastada kolit, tedaviye bağlı önemli bir bağırsak toksisitesidir. Kontrastlı BT tanıyı tek başına koymaz; duvar ve mukoza değişikliklerinin dağılımını gösterir, ayrıca dilatasyon, perforasyon ve eşlik eden başka akut karın nedenlerini araştırır. Yaygın kolit ile divertiküloz zeminindeki segmental tutulum farklı görünümler oluşturabilir. İskemik hasar, perforasyon veya ağır dilatasyonun atlanması acil komplikasyonun fark edilmesini geciktirebilir.
Faz ve pencere
- Portal tanısal
- İntravenöz kontrast sonrası kolon mukozasının belirginleşmesi, duvar kalınlaşması ve mezenterik vasa recta dolgunluğu değerlendirilir; yaygın tutulumda lümen sıvıyla dolu olabilir. Segmental tutulumda duvar değişikliği ve perikolik yağ çizgilenmesi sıklıkla divertiküloz bulunan kolon kesimine eşlik eder. Bu bulgular kolit paternini gösterir, ancak ilaca bağlı nedeni tek başına kanıtlamaz.
Önerilen pencereler: Batın (G 400 / M 50), Yumuşak doku (G 400 / M 40).
BT bulguları
- Yaygın duvar kalınlaşması — kolonun uzun kesimlerinde devamlı ya da atlamalı dağılım gösterir.
- Mukozal hiperenhansman — kontrastlı incelemede kolon mukozası kontrastlanma artışı gösterir; eşlik eden duvar kalınlaşması değerlendirilir.
- Mezenterik damar belirginliği — vasa recta dolgun veya kıvrımlı görünür; tedavi öncesi incelemeyle kıyas ipucu sağlar.
- Sıvı dolu kolon — lümen içeriği sıvı ağırlıklı ve kolon genişlemiş olabilir.
- Divertiküloz zemininde segmental kolit — divertiküllerin bulunduğu kolon kesiminde orta derecede duvar kalınlaşması, damar belirginliği ve perikolik yağ çizgilenmesi.
- İzole rektosigmoid tutulum — divertiküloz olmaksızın rektum ve sigmoidde mukozal belirginleşme; yağlı doku çizgilenmesi baskın bulgu olmayabilir.
- Perforasyon veya ağır dilatasyon — ekstraluminal serbest hava, duvar bütünlüğünde kesinti ya da belirgin kolon genişlemesi aranır.
Normalde
İyi distandü normal kolonda duvar ince ve düzgün, mukoza diğer bağırsak segmentlerine benzer biçimde kontrastlanmış, mezenterik damarlar belirgin tortiyöz değildir. Şüpheli kolon kesimini tedavi öncesi BT ve komşu sağlam segmentlerle karşılaştırın; kalınlaşmanın yaygın mı divertiküloz çevresinde sınırlı mı olduğunu ve perikolik yağ değişikliğini izleyin.
Normal BT ile kıyasla
Aynı bölgenin, kaynak veri setinde patoloji içermediği belirtilen bir BT incelemesini kesit kesit kaydırın; organ sınırlarını açarak anatomiyi hasta görüntüsüyle karşılaştırın. Küçük rastlantısal bulgular tümüyle dışlanmamıştır.
Kaynak: TotalSegmentator v2.01 veri seti (Wasserthal ve ark., Radiology: Artificial Intelligence 2023), CC BY 4.0, vaka s0119; organ sınırları veri setinin otomatik segmentasyonundan, birleştirilerek sadeleştirildi. Görüntüler 2,5 mm kesit aralığına yeniden örneklendi.
Ayırıcı tanı
- Enfeksiyöz kolit
- sıklıkla sağ kolon ağırlıklı, daha homojen duvar kontrastlanması gösterebilir; klinik ve dışkı testleriyle ayrım gerekir.
- Ülseratif kolit
- rektumdan başlayıp proksimale uzanan sürekli tutulum ve distal kolonda daha belirgin inflamasyon beklenir.
- Crohn hastalığı
- terminal ileum ve kolonda atlamalı, transmural tutulum; fistül, apse veya fibrofatty proliferasyon eşlik edebilir.
- İskemik kolit
- damar dağılımına uyan segmentte ödemli duvar, azalmış kontrastlanma veya ileri olguda pnömatozis görülebilir.
- Aktif divertiküloz
- semptomların nispeten hafif olması ve dışkıda bakteriyel patojen ya da lökosit bulunmaması, segmental immün kolit ile karşılaştırıldığında ayırt edici bulgu sağlar.
Tuzaklar
- BT’de kolit görünümü immün toksisiteye özgü değildir; enfeksiyon, inflamatuvar bağırsak hastalığı ve iskemi klinik bağlamla dışlanmalıdır.
- Divertiküloz zeminindeki segmental değişiklikler — semptomların hafif seyretmesi ve dışkı patojen/lökosit testlerinin negatif olması, segmental immün kolitin aktif divertikülozdan ayrımında rehberlik eder.
- Pnömatozis, halo veya target görünümü immün kolite özgü kabul edilmemeli; başka kolit nedenleri ve iskemi de düşünülmelidir.
- BT’de belirgin anormallik görülmemesi semptomatik immün koliti dışlamaz; görüntüleme tanı için endoskopi ve klinik değerlendirmeye alternatif değildir.
Kendini dene
İmmün kontrol noktası inhibitörü kullanan hastada dışkı etken incelemeleri negatif; yaygın kolon duvar kalınlaşması ve mezenterik damar belirginliği görülüyor. BT bulguları ve tedavi öyküsü hangi tanıyı destekler?
Cevabı göster
İmmünoterapi ilişkili kolit. Yaygın duvar kalınlaşması, mukozal hiperenhansman ve mezenterik damar belirginliği immün ilişkili yaygın kolit paternini destekler. Negatif dışkı etken incelemesi ve tedavi öyküsü olasılığı artırır; BT tek başına ilaca bağlı nedeni kanıtlamaz. İskemi damar dağılımına uyan tutulum ve azalmış kontrastlanmayla, ülseratif kolit sürekli distal tutulumla; enfeksiyon klinik ve mikrobiyolojik verilerle değerlendirilir.
İmmün kontrol noktası inhibitörü kullanan, dışkı patojen incelemesi negatif hastada divertikülozlu sigmoid kesimde orta derecede kalınlaşma, perikolik yağ reaksiyonu ve damar dolgunluğu var; inflame divertikül seçilmiyor. En uygun patern hangisidir?
Cevabı göster
Segmental immün kolit. Divertiküloz içeren sınırlı kolon kesimindeki orta derecede kalınlaşma, perikolik yağ çizgilenmesi ve damar belirginliği immün ilişkili segmental kolit (SCAD-benzeri) paternini destekler. Inflame divertikülün gösterilmemesi akut divertikülit lehine kanıtı azaltır; Crohn’da atlamalı transmural hastalık ve terminal ileum tutulumu, iskemide damar dağılımı/perfüzyon bozukluğu, ülseratif kolitte sürekli distal tutulum aranır.
İlgili konular
Kaynaklar
Bu sayfadaki 39 cümle ve 2 quiz sorusu aşağıdaki kaynaklardan alıntılarla tek tek karşılaştırıldı; 2 cümle bu karşılaştırmada düzeltildi (2026-10-09).
- Imaging of Adverse Events Related to Checkpoint Inhibitor Therapypmc.ncbi.nlm.nih.gov
- Gastrointestinal adverse events of immunotherapypmc.ncbi.nlm.nih.gov
- Highly multiplexed spatial analysis identifies tissue-resident memory T cells as drivers of ulcerative and immune checkpoint inhibitor colitis.pubmed.ncbi.nlm.nih.gov
- Ipilimumab alone or ipilimumab plus anti-PD-1 therapy in patients with metastatic melanoma resistant to anti-PD-(L)1 monotherapy: a multicentre, retrospective, cohort study.pubmed.ncbi.nlm.nih.gov
- FDG PET/CT for Evaluation of Immunotherapy Response in Lung Cancer Patients.pubmed.ncbi.nlm.nih.gov
- Immune-mediated Disease in Ipilimumab Immunotherapy of Melanoma with FDG PET-CT.pubmed.ncbi.nlm.nih.gov
- Immunogenicity of Biologics in Chronic Inflammatory Diseases: A Systematic Review.pubmed.ncbi.nlm.nih.gov
- Pembrolizumab for management of patients with NSCLC and brain metastases: long-term results and biomarker analysis from a non-randomised, open-label, phase 2 trial.pubmed.ncbi.nlm.nih.gov
- Ipilimumab-induced colitis on FDG PET/CT.pubmed.ncbi.nlm.nih.gov
- [Adverse events of immune checkpoint inhibitors].pubmed.ncbi.nlm.nih.gov
- Image intensity histograms as imaging biomarkers: application to immune-related colitis.pubmed.ncbi.nlm.nih.gov
- Immune checkpoint inhibitor-associated gastrointestinal and hepatic adverse events and their management.pubmed.ncbi.nlm.nih.gov
- Drug-induced Pancreatic Atrophy ("The Vanishing Pancreas").pubmed.ncbi.nlm.nih.gov
- [Can nivolumab be used safely in idiopathic pulmonary fibrosis?].pubmed.ncbi.nlm.nih.gov
- Isolated recto-sigmoid colitis: a new imaging pattern of ipilimumab-associated colitis.pubmed.ncbi.nlm.nih.gov
- Pancreatitis Secondary to Anti-Programmed Death Receptor 1 Immunotherapy Diagnosed by FDG PET/CT.pubmed.ncbi.nlm.nih.gov
- Probable everolimus-associated severe colitis with hematochezia in a patient with metastatic hormone receptor-positive, HER2-negative breast cancer: a case report.pubmed.ncbi.nlm.nih.gov
- Immune checkpoint inhibitor-related intestinal pseudo-obstruction and multisystem immune-related adverse events in a post-gastrectomy patient: a case report and literature review.pubmed.ncbi.nlm.nih.gov
- Immune Checkpoint Inhibitor Esophagitis: Clinical and Endoscopic Presentation, Treatment Outcomes, and Complications.pubmed.ncbi.nlm.nih.gov
- A Case of Fulminant Immune-Related Enterocolitis During Immune Checkpoint Inhibitor Therapy for Metastatic Renal Cell Carcinoma.pubmed.ncbi.nlm.nih.gov
- Myokine-mediated mechanisms of immune checkpoint inhibitors-associated colorectal injury and repair in rectal cancer.pubmed.ncbi.nlm.nih.gov
- Segmental Colitis Associated with Diverticulosis: Status Quo.pubmed.ncbi.nlm.nih.gov
- Imaging Findings of Complications of New Anticancer Drugs.pubmed.ncbi.nlm.nih.gov
- Focus on Immune Checkpoint Inhibitors-related Intestinal Inflammation: From Pathogenesis to Therapeutical Approach.pubmed.ncbi.nlm.nih.gov
- Idiopathic mesenteric phlebosclerosis: A case report.pubmed.ncbi.nlm.nih.gov
- Hematemesis resulting from mesenteric venous thrombosis: A case report.pubmed.ncbi.nlm.nih.gov
- The Importance of Magnetic Resonance Enterography in Monitoring Inflammatory Bowel Disease: A Review of Clinical Significance and Current Challenges.pubmed.ncbi.nlm.nih.gov
- Analysis of clinical characteristics of 117 cases of ischemic colitis.pubmed.ncbi.nlm.nih.gov
- Diagnostic Role of Multi-Detector Computed Tomography in Acute Mesenteric Ischemia.pubmed.ncbi.nlm.nih.gov
- The Role of CT-Angiography in the Acute Gastrointestinal Bleeding: A Pictorial Essay of Active and Obscure Findings.pubmed.ncbi.nlm.nih.gov
- A Case of Amyloid Light-Chain Amyloidosis Presenting as Colitis.pubmed.ncbi.nlm.nih.gov
- When Pancreatitis Strikes the Colon: A Rare Case Report of Sigmoid Perforation.pubmed.ncbi.nlm.nih.gov
- Hepatic and Pancreatobiliary Immune-Related Adverse Events in Patients Receiving Immune Checkpoint Inhibitors: A Multidisciplinary Approach.pubmed.ncbi.nlm.nih.gov
- Hematological Toxicities in the Modern Era of Melanoma Therapy.pubmed.ncbi.nlm.nih.gov
- A case report of a rare intrahepatic cholangiocarcinoma with rectal metastasis.pubmed.ncbi.nlm.nih.gov
- Gastrointestinal adverse events of immunotherapy.pubmed.ncbi.nlm.nih.gov
- The Role of Imaging in Inflammatory Bowel Diseases: From Diagnosis to Individualized Therapy.pubmed.ncbi.nlm.nih.gov
- Comprehensive Imaging Evaluation and Staging of Crohn's Disease: When and Why to Use Intestinal Ultrasound, MRE, or CTE: Current Guidelines and Future Directions.pubmed.ncbi.nlm.nih.gov
- Long-term safety and effectiveness of the "OptEase" vena cava filter.pubmed.ncbi.nlm.nih.gov
- Guidelines on the Use of Therapeutic Apheresis in Clinical Practice-Evidence-Based Approach From the Writing Committee of the American Society for Apheresis: The Tenth Special Issue.pubmed.ncbi.nlm.nih.gov
- Chemotherapy-induced bowel ischemia: diagnostic imaging overview.pubmed.ncbi.nlm.nih.gov
- Consensus guidelines for the use and interpretation of angiogenesis assays.pubmed.ncbi.nlm.nih.gov
- Pneumatosis Intestinalis Secondary to Appendicitis: What Do We Know?pubmed.ncbi.nlm.nih.gov
- Colonic Volvulus.pubmed.ncbi.nlm.nih.gov
- A Study on the Spectrum of Imaging Findings of Post-ERCP-Specific Complications: A Retrospective Descriptive Study.pubmed.ncbi.nlm.nih.gov
- Integrating Intestinal Ultrasound in the Personalized Management of IBD.pubmed.ncbi.nlm.nih.gov
- The Many Faces of the Angry Peritoneum.pubmed.ncbi.nlm.nih.gov
- Gastrointestinal Ultrasound: Measurements and Normal Findings - What Do You Need to Know?pubmed.ncbi.nlm.nih.gov
- Is 18 F-FDG-PET/CT an Optimal Imaging Modality for Detecting Immune-Related Adverse Events after Immune-Checkpoint Inhibitor Therapy? Pros and Cons.pubmed.ncbi.nlm.nih.gov
- Checkpoint Inhibitor-Induced Colitis: From Pathogenesis to Management.pubmed.ncbi.nlm.nih.gov
- Clostridioides difficile infection: history, epidemiology, risk factors, prevention, clinical manifestations, treatment, and future options.pubmed.ncbi.nlm.nih.gov
- Mass-Forming NSAID-Associated Colopathy Mimicking Right-Sided Colon Cancer: A Case Report.pubmed.ncbi.nlm.nih.gov
- When It Is Not NEC: Recognizing Mimics of Necrotizing Enterocolitis in Preterm Infants.pubmed.ncbi.nlm.nih.gov
- Recent advances in the diagnosis and management of amoebiasis.pubmed.ncbi.nlm.nih.gov
- Apical Periodontitis May Exacerbate Ulcerative Colitis via Neutrophil Extracellular Trap-Mediated Systemic Inflammation and Intestinal Barrier Disruption in Mice.pubmed.ncbi.nlm.nih.gov
- Current Status of Diagnosis and Treatment of Cap Polyposis: Insights From Chinese Studies and Comparative Analysis with Japanese Cases.pubmed.ncbi.nlm.nih.gov
- Incidental findings in female pelvis MRI performed for gynaecological malignancies.pubmed.ncbi.nlm.nih.gov
- The Diagnostic Challenge of Crohn's Disease With Initial Duodenal Involvement: Two Cases and Literature Review.pubmed.ncbi.nlm.nih.gov
- The Overlap Between Crohn's Disease and Intestinal Tuberculosis: A Never-Ending Story.pubmed.ncbi.nlm.nih.gov
- Endoscopic Skipping, Stricturing, and Penetrating Complications in Crohn's Disease on Tandem Ileo-colonoscopy and Cross-sectional Imaging: A Retrospective Cohort Study.pubmed.ncbi.nlm.nih.gov
- Computed tomography findings and surgical outcomes in acute mesenteric ischemia: a retrospective single-center cohort study.pubmed.ncbi.nlm.nih.gov
- Gastrointestinal complications of cocaine use: a narrative literature review.pubmed.ncbi.nlm.nih.gov
- Mesenteric Ischemia: A Comprehensive Review of the Role of Radiology in Diagnosis.pubmed.ncbi.nlm.nih.gov
- Perforation in a patient with stercoral colitis and diverticulosis: who did it?pubmed.ncbi.nlm.nih.gov
- Immune checkpoint inhibitor-related pancreatitis: a comprehensive review of epidemiology, pathophysiology, and management.pubmed.ncbi.nlm.nih.gov
- A Rare Case of Severe Disseminated Pyoderma Gangrenosum of the Upper Body With Concurrent Nasopharyngeal and Inferior Orbital Wall Necrosis.pubmed.ncbi.nlm.nih.gov
- Trends and Outcomes in Acute Colonic Diverticulitis: A Single-Center Three-Year Retrospective Cohort Study From Greece.pubmed.ncbi.nlm.nih.gov
- Small Bowel Diverticulosis and COVID-19: Awareness Is the Key: A Case Series and Review of the Literature.pubmed.ncbi.nlm.nih.gov
- Pneumatosis intestinalis revisited: associated imaging findings, clinical correlation, management, risk stratification and future perspectives.pubmed.ncbi.nlm.nih.gov
- The Usefulness and Limitations of Radiologic Findings for Diagnosis of Infectious Diseases: A Call for Antimicrobial Stewardship.pubmed.ncbi.nlm.nih.gov
- POCUS for acute abdominal pain: practical scan protocols on gastrointestinal diseases and an evidence review.pubmed.ncbi.nlm.nih.gov
- Organ preservation after neoadjuvant immunotherapy in mismatch repair-deficient colorectal cancer: response assessment, watch-and-wait, and salvage surgery.pubmed.ncbi.nlm.nih.gov
- Colorectal Cancer: Epidemiology, Risk Factors, Signaling Pathways, Clinical Features, Screening, Diagnosis, and Management.pubmed.ncbi.nlm.nih.gov
- Synergistic neoadjuvant radioimmunotherapy in locally advanced rectal cancer: mechanisms of pathologic response and the shift toward organ preservation.pubmed.ncbi.nlm.nih.gov
- Iatrogenic perforation of a sigmoid diverticulum following diagnostic colonoscopy.pubmed.ncbi.nlm.nih.gov
- Perforated Ileal Diverticulitis Presenting With Acute Peritonitis in an Elderly Patient: A Case Report.pubmed.ncbi.nlm.nih.gov
- Acute abdomen secondary to perforated jejunal diverticulitis: an unusual clinical presentation - case report.pubmed.ncbi.nlm.nih.gov
- Visual theranostic oral nanozymes for IBD from principles to preclinical design.pubmed.ncbi.nlm.nih.gov
- Role of multidetector computed tomography in patients with acute infectious colitis.pubmed.ncbi.nlm.nih.gov
- Gastrointestinal perforation: clinical and MDCT clues for identification of aetiology.pubmed.ncbi.nlm.nih.gov
- Risk Factors Associated with Intestinal Strangulation in Patients with Adhesive Small Bowel Obstruction: A Retrospective Analysis of 951 Cases.pubmed.ncbi.nlm.nih.gov
- Acute toxic megacolon in visceral myopathy: A rare and challenging case report with literature review.pubmed.ncbi.nlm.nih.gov
- Special Issue: EACR 2026 Congress: Innovative Cancer Science, 8-11 June 2026.pubmed.ncbi.nlm.nih.gov
- Nontuberculous mycobacterial infections in the setting of immune checkpoint inhibitor therapy: A case series.pubmed.ncbi.nlm.nih.gov
- Cytotoxic T-Lymphocyte-Associated Protein 4 Deficiency Colitis Masked by Recurrent Cytomegalovirus Colitis Successfully Treated With Vedolizumab.pubmed.ncbi.nlm.nih.gov
- Review of COVID-19, part 1: Abdominal manifestations in adults and multisystem inflammatory syndrome in children.pubmed.ncbi.nlm.nih.gov
- Multisystem Imaging Manifestations of COVID-19, Part 2: From Cardiac Complications to Pediatric Manifestations.pubmed.ncbi.nlm.nih.gov
- Metabolic determinants of cancer immunotherapy outcomes identified by plasma profiling.pubmed.ncbi.nlm.nih.gov
- Soil-derived microbiota induces T regulatory cells and protect against mouse colitis, metabolic disease, and sepsis.pubmed.ncbi.nlm.nih.gov
- Intratumoral Microorganisms in Tumors: Current Understanding and Emerging Therapeutic Strategies.pubmed.ncbi.nlm.nih.gov
- Therapeutic implications of SARS-CoV-2 dysregulation of the gut-brain-lung axis.pubmed.ncbi.nlm.nih.gov
- International Society of Paediatric Surgical Oncology (IPSO) Surgical Practice Guidelines.pubmed.ncbi.nlm.nih.gov
- EACR 2025 Congress: Innovative Cancer Science, 16-19 June 2025.pubmed.ncbi.nlm.nih.gov
- Characteristics, treatment, and outcome of diverticulitis after immune checkpoint inhibitor treatment in patients with malignancies.pubmed.ncbi.nlm.nih.gov
- Colonic diverticular disease.pubmed.ncbi.nlm.nih.gov
- Role of magnetic resonance in bowel pathologies: Beyond inflammatory bowel disease.pubmed.ncbi.nlm.nih.gov
- Rapid Progressive Liver Atrophy During Immune Checkpoint Inhibitor Hepatitis: Imaging Perspectives Beyond Aminotransferase Elevation.pubmed.ncbi.nlm.nih.gov
- Single-cell transcriptomic insights into the immune heterogeneity of immune checkpoint inhibitors related organ toxicities.pubmed.ncbi.nlm.nih.gov
- Vedolizumab: Beyond Inflammatory Bowel Disease.pubmed.ncbi.nlm.nih.gov
- Clinical Decision Making in Inflammatory Bowel Disease Mimics: Practice Management from Inflammatory Bowel Disease LIVE.pubmed.ncbi.nlm.nih.gov
- Management of acute severe ulcerative colitis-an update for generalist and specialist clinicians.pubmed.ncbi.nlm.nih.gov
- Faecal Calprotectin: A Non-Invasive Marker for Diagnosing and Monitoring Acute Diverticulitis.pubmed.ncbi.nlm.nih.gov
- Utility of Colonoscopy After Acute Colonic Diverticulitis.pubmed.ncbi.nlm.nih.gov
- Imaging of ectopic gastric mucosa in Meckel's diverticulum: A case report and literature review.pubmed.ncbi.nlm.nih.gov
- Complicated Jejunal Diverticulosis as a Rare Cause of Small Bowel Perforation in an Immunocompromised Patient: A Case Report.pubmed.ncbi.nlm.nih.gov
- A Rare Case of Giant Meckel's Diverticulum in an Adult: Diagnostic and Therapeutic Challenges.pubmed.ncbi.nlm.nih.gov
Eğitim amaçlıdır; hasta başında tanı ve tedavi kararının yerine geçmez. İçerik yapay zekâ destekli bir süreçle güncel literatüre göre cümle cümle kaynaklarla karşılaştırıldı, ancak uzman radyolog incelemesinden geçmedi. Klinik kararlarda güncel kılavuzları, kurum protokollerini ve radyoloji raporunu esas alın.