Özet
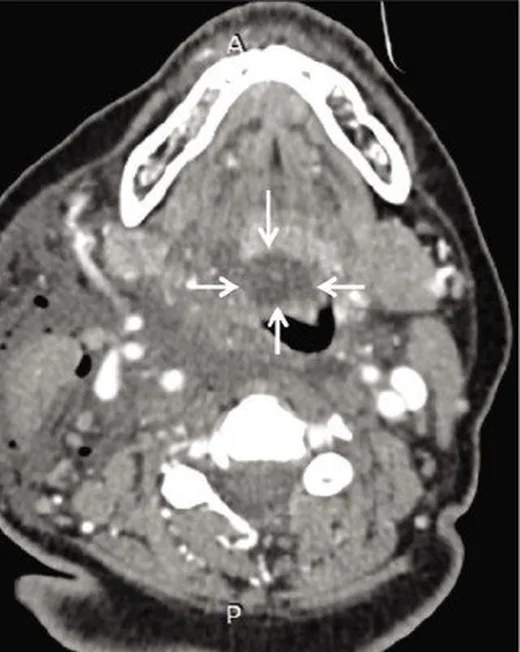
Epiglottik retansiyon kisti, epiglot yüzeyindeki mukus bez kanallarının tıkanmasına bağlı gelişen, çoğunlukla benign ve tesadüfi bir kistik lezyondur. Kontrastlı boyun BT'sinde epiglot ve vallekula bölgesindeki kistlerin varlığı ve konumu gösterilebilir. Büyük kist hava yolunu örtebilir; enfeksiyon geliştiğinde duvar ve çevre dokulardaki inflamasyon daha belirgin hale gelir. Epiglottik kistler ikincil enfeksiyonla epiglottit veya epiglottik apse ile komplike olabileceğinden bu olasılıklar ayırıcı tanıda dikkate alınmalıdır.
Faz ve pencere
- Venöz tanısal
- Kontrastlı boyun BT'sinde epiglot yüzeyine tutunan, homojen düşük atenüasyonlu ve iyi sınırlı kistik odak izlenir; enfeksiyon şüphesinde rim-enhanse duvar ve çevre inflamasyon arayışı yapılır.
Önerilen pencereler: Yumuşak doku (G 400 / M 40).
BT bulguları
- Kist epiglotun lingual yüzünde vallekulaya taşabilir veya laringeal yüzünde supraglottik hava yoluna doğru büyüyebilir.
- İçerik homojen düşük atenüasyonludur ve lezyon genellikle iyi sınırlı, yuvarlak/oval konturludur.
- İnce duvarlı ve enfeksiyon bulgusu olmayan kistte belirgin epiglot veya çevre yumuşak doku ödemi beklenmez.
- Büyük kist epiglotu laringeal girişe doğru iter ve hava sütununu daraltabilir.
- Enfekte kistte duvar kalınlaşması veya komşu yumuşak doku ödemi eşlik edebilir; bu bulgular klinik ve diğer görüntü özellikleriyle birlikte yorumlanır.
- Epiglottik kist ikincil enfeksiyonla epiglottit veya epiglottik abseyle komplike olabilir; bu nedenle enfeksiyon bulguları kist morfolojisiyle birlikte değerlendirilmelidir.
- Supraglottik ödem görülmesi supraglottit olasılığını destekleyebilir.
Normalde
Vallekula, dil kökü ile epiglotun lingual yüzü arasında yer alır. Kıyaslamada epiglot yüzeyine tutunan sıvı atenüasyonlu yuvarlak odak, epiglot konturındaki ödem ve laringeal giriş açıklığı ile karşılaştırılmalıdır.
Normal BT ile kıyasla
Aynı bölgenin, kaynak veri setinde patoloji içermediği belirtilen bir BT incelemesini kesit kesit kaydırın; organ sınırlarını açarak anatomiyi hasta görüntüsüyle karşılaştırın. Küçük rastlantısal bulgular tümüyle dışlanmamıştır.
Kaynak: TotalSegmentator v2.01 veri seti (Wasserthal ve ark., Radiology: Artificial Intelligence 2023), CC BY 4.0, vaka s0622; organ sınırları veri setinin otomatik segmentasyonundan, birleştirilerek sadeleştirildi. Görüntüler 2,5 mm kesit aralığına yeniden örneklendi.
Ayırıcı tanı
- Akut epiglottit
- enfeksiyöz süreçte epiglotta ve çevre yumuşak dokularda yaygın ödem ve kalınlaşma görür, sınırlı kistik oluşum oluşturmaz.
- Epiglottik apse
- merkezinde sıvı, çevresinde rim-enhanse duvar ve çevre yumuşak doku ödemine neden olabilir.
- Vallekula kisti
- çoğunlukla vallekula/lingual epiglot arayüzünde bulunur ve epiglotu aşağı itebilir.
- Larengeal hemangiom, epiglotta mavi-kırmızı, pedinküllü ve belirgin vaskülarite gösteren yüzeyel vasküler lezyon olarak izlenebilir.
- Supraglottik neoplazm
- solid kontrastlanan doku, infiltratif sınır veya mukozal düzensizlik ile kistik retansiyon odağından ayrılır.
Tuzaklar
- Epiglottik kist ikincil enfeksiyonla epiglottit veya epiglottik apse ile komplike olabilir; bu olasılıklar değerlendirilirken enfeksiyon bulguları aranmalıdır.
- Epiglottit kisti çevreleyebilir; epiglotun yaygın kalınlaşmasını sınırlı, düzgün konturlu kistik odaktan ayrı tarif et.
- Lingual yüzdeki kist vallekula kaynaklı kitle gibi görünebilir; koronal/sagittal düzlemde epiglotla tutunma yüzünü belirle.
Kendini dene
Kontrastlı boyun BT'sinde epiglotta iyi sınırlı, homojen düşük atenüasyonlu kistik yapılar görülüyor. Olgu raporundaki tanı nedir?
Cevabı göster
Epiglottik kist. Olgu raporunda kontrastlı boyun BT'sinde epiglottik kistler tanımlanmış, lezyonların kistik yapısı histopatolojiyle doğrulanmıştır.
Kontrastlı boyun BT'sinde epiglotta rim-enhanse duvarlı, merkezinde düşük atenüasyonlu odağı olan lezyon izleniyor. En olası tanı?
Cevabı göster
Epiglottik abse. Rim-enhanse duvar ve çevre inflamasyon, kistik odakta abseyi destekler. Retansiyon kisti ince duvarlıdır, hemangiom damar içi kontrastlanır, kanser ise solid/infiltratiftir.
İlgili konular
Kaynaklar
Bu sayfadaki 35 cümle ve 2 quiz sorusu aşağıdaki kaynaklardan alıntılarla tek tek karşılaştırıldı; 9 cümle bu karşılaştırmada düzeltildi (2026-10-08).
- Clinically Suspected Fungal Laryngitis Masquerading as Laryngeal Carcinoma in a High-Risk Patientpmc.ncbi.nlm.nih.gov
- Vallecular Large B-Cell Lymphoma: An Uncommon Presentation of Follicular-Origin Diseasepmc.ncbi.nlm.nih.gov
- Asymptomatic giant epiglottic cyst causing an unexpectedly difficult airway: a case reportpmc.ncbi.nlm.nih.gov
- CT and MRI Key Features of Benign Tumors and Tumor-like Lesions of the Tongue: A Pictorial Reviewpmc.ncbi.nlm.nih.gov
- Incidental finding of two epiglottic cysts: Case report and literature reviewpmc.ncbi.nlm.nih.gov
- Airway obstruction requiring tracheal intubation after fine-needle aspiration of the thyroid gland: a case report.pubmed.ncbi.nlm.nih.gov
- Incidental finding of two epiglottic cysts: Case report and literature review.pubmed.ncbi.nlm.nih.gov
- Asymptomatic giant epiglottic cyst causing an unexpectedly difficult airway: a case report.pubmed.ncbi.nlm.nih.gov
- CT and MRI Key Features of Benign Tumors and Tumor-like Lesions of the Tongue: A Pictorial Review.pubmed.ncbi.nlm.nih.gov
- Clear cell, giant myoepithelioma of tongue base: a diagnostic and surgical challenge.pubmed.ncbi.nlm.nih.gov
- Imaging for Pediatric Head and Neck Emergencies: Critical Insights.pubmed.ncbi.nlm.nih.gov
- Antimicrobial prescribing guidelines for horses in Australia.pubmed.ncbi.nlm.nih.gov
- End-stage renal disease as a risk factor for epiglottitis: a population-based cohort study in Taiwan.pubmed.ncbi.nlm.nih.gov
- Cries, Stridor, and Clues: Unmasking a Rare Airway Obstruction in an Infant.pubmed.ncbi.nlm.nih.gov
- Trends in Preoperative Airway Assessment.pubmed.ncbi.nlm.nih.gov
- Case Report: Synchronous lingual osseous choristoma and suprahyoid thyroglossal duct cyst: insights into the embryological thyroglossal-hyoid axis.pubmed.ncbi.nlm.nih.gov
- Laryngeal Schwannoma, Alarming Mass of Airway: A Case Report.pubmed.ncbi.nlm.nih.gov
- Alpelisib for the treatment of PIK3CA-related head and neck lymphatic malformations and overgrowth.pubmed.ncbi.nlm.nih.gov
- Extrapulmonary tuberculosıs: an old but resurgent problem.pubmed.ncbi.nlm.nih.gov
- Epiglottic masses identified on CT imaging: A case report and review of the broad differential diagnosis.pubmed.ncbi.nlm.nih.gov
- Comprehensive review of post-treatment imaging in head and neck cancers: from expected to unexpected and beyond.pubmed.ncbi.nlm.nih.gov
- MRI of acute neck infections: evidence summary and pictorial review.pubmed.ncbi.nlm.nih.gov
- Anesthetic management of vallecular cyst excision in an infant: An airway challenge.pubmed.ncbi.nlm.nih.gov
- An Uncommon Epiglottic Cyst Presentation in an Adolescent: A Case Report and Literature Review.pubmed.ncbi.nlm.nih.gov
- Prevalence and Radiographic Features of Head and Neck Soft Tissue Calcifications on Digital Panoramic Radiographs: A Retrospective Study.pubmed.ncbi.nlm.nih.gov
- Multimodality imaging of mediastinal masses and mimics.pubmed.ncbi.nlm.nih.gov
- Submucosal laryngeal lesions: A puzzling diagnostic conundrum.pubmed.ncbi.nlm.nih.gov
- Interventional neuroradiology of the head and neck.pubmed.ncbi.nlm.nih.gov
- Magnetic Resonance Imaging Features of Hepatic Hydatid Disease: A Pictorial Review with Emphasis on Atypical Presentations and Differential Diagnosis.pubmed.ncbi.nlm.nih.gov
- Mucinous cystic neoplasms of the liver: current insights into epidemiology, diagnosis, and treatment.pubmed.ncbi.nlm.nih.gov
- Imaging of lower extremity infections: predisposing conditions, atypical infections, mimics, and differentiating features.pubmed.ncbi.nlm.nih.gov
- Radiographic imaging of human papillomavirus related carcinomas of the oropharynx.pubmed.ncbi.nlm.nih.gov
- Clinically Suspected Fungal Laryngitis Masquerading as Laryngeal Carcinoma in a High-Risk Patient.pubmed.ncbi.nlm.nih.gov
- When Adult Epiglottitis Does Not Improve With Intravenous Therapy: Think Epiglottic Abscess.pubmed.ncbi.nlm.nih.gov
- Case Report: Recurrent supraglottitis in a patient with metastatic melanoma treated with ipilimumab and nivolumab.pubmed.ncbi.nlm.nih.gov
- Epiglottitis in Patients Treated for Acute Leukemia: Case Series and Systematic Review of the Literature.pubmed.ncbi.nlm.nih.gov
- Evidence-based guideline diagnosis, treatment, prevention and aftercare of oropharyngeal and hypopharyngeal carcinoma.pubmed.ncbi.nlm.nih.gov
- Reconstruction of vocal tract geometries from biomechanical simulations.pubmed.ncbi.nlm.nih.gov
- Imaging in laryngeal cancers.pubmed.ncbi.nlm.nih.gov
- Delayed Diagnosis of an Adult Epiglottic Abscess: A Case Report.pubmed.ncbi.nlm.nih.gov
- Sphenoid sinus anatomical variants and pathologies: pictorial essay.pubmed.ncbi.nlm.nih.gov
- International Harmonization of Nomenclature and Diagnostic Criteria (INHAND): Non-proliferative and Proliferative Lesions of the Non-human Primate ( M. fascicularis ).pubmed.ncbi.nlm.nih.gov
- Rare Diseases of the Nose, the Paranasal Sinuses, and the Anterior Skull Base.pubmed.ncbi.nlm.nih.gov
- Double thumb sign in a case of epiglottitis.pubmed.ncbi.nlm.nih.gov
- Acute airway obstruction, an unusual presentation of vallecular cyst.pubmed.ncbi.nlm.nih.gov
- Tonsillar Lymphangiomatous Polyp Mimicking a Vallecular Cyst in an Adult: A Case Report.pubmed.ncbi.nlm.nih.gov
- Giant Epiglottic Inclusion Cyst.pubmed.ncbi.nlm.nih.gov
- Non-Contiguous Double Thyroglossal Duct Cysts: A Case Report.pubmed.ncbi.nlm.nih.gov
- Unanticipated Difficult Intubation in a Child Due to a Vallecular Cyst: A Case Report.pubmed.ncbi.nlm.nih.gov
- Incidentally Detected Asymptomatic Epiglottic Capillary Hemangioma in a 66-Year-Old Female: A Case Report.pubmed.ncbi.nlm.nih.gov
- Large Vallecula Epiglottica Lipoma: A Rare but Fatal Cause of Dysphagia.pubmed.ncbi.nlm.nih.gov
- Large Vallecular Masses; Differential Diagnosis and Imaging Features.pubmed.ncbi.nlm.nih.gov
- Vallecular Large B-Cell Lymphoma: An Uncommon Presentation of Follicular-Origin Disease.pubmed.ncbi.nlm.nih.gov
- Clinical characteristics and treatment for laryngeal cyst in children: a case series study.pubmed.ncbi.nlm.nih.gov
- Differences in characteristics and infection severity between odontogenic and other bacterial oro-naso-pharyngeal infections.pubmed.ncbi.nlm.nih.gov
- A radiologic review of hoarse voice from anatomic and neurologic perspectives.pubmed.ncbi.nlm.nih.gov
- Rising Incidence of Acute Epiglottitis in Eastern China: An Eight-Year Retrospective Study and Its Association with the 24 Solar Terms.pubmed.ncbi.nlm.nih.gov
- 3D morphometric analysis of the epiglottis using CBCT: age and gender differences.pubmed.ncbi.nlm.nih.gov
- Identify Patients at Risk of Moderate or Severe OSAHS During ENT Examination.pubmed.ncbi.nlm.nih.gov
- Dynamics of oropharyngeal structures during respiration with the volume-altered tongue base of minipigs.pubmed.ncbi.nlm.nih.gov
- The mineralised epiglottis: a narrative review illustrated by an index case.pubmed.ncbi.nlm.nih.gov
- Endoscopic CO<sub>2</sub> Laser Excision of Internal Pyolaryngocele: A Rare Airway Emergency Case Report With Review of the Literature.pubmed.ncbi.nlm.nih.gov
- Posterior Lingual Abscess; Report of Two Cases.pubmed.ncbi.nlm.nih.gov
Eğitim amaçlıdır; hasta başında tanı ve tedavi kararının yerine geçmez. İçerik yapay zekâ destekli bir süreçle güncel literatüre göre cümle cümle kaynaklarla karşılaştırıldı, ancak uzman radyolog incelemesinden geçmedi. Klinik kararlarda güncel kılavuzları, kurum protokollerini ve radyoloji raporunu esas alın.