Özet
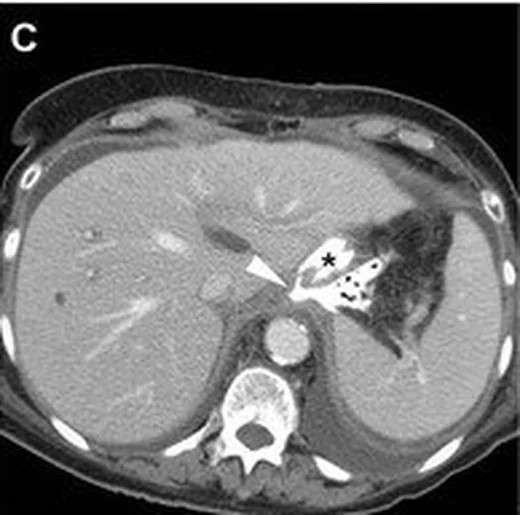
Gastrik rezeksiyon veya bariatrik cerrahi sonrası anastomoz ya da stapler hattının ayrışması, enterik içeriğin cerrahi yatağa geçmesine ve lokal enfeksiyon, apse veya peritonite yol açabilir. BT, ameliyatla değişmiş anatomiyi haritalarken lümen dışına kontrast geçişini, perianastomotik gaz-sıvı koleksiyonlarını ve çevre dokudaki inflamasyonu gösterir. BT'de anastomoz duvar kesintisi kaçağın özgül ancak duyarlılığı düşük bir doğrudan bulgusudur; görülmemesi kaçağı dışlamaz. Kaçak, perianastomotik koleksiyon ya da yaygın peritonit şeklinde görülebilir; değerlendirmede odağın yerini ve yayılımını birlikte tarif et.
Faz ve pencere
- Kontrastsız
- Duvar dışı serbest hava, cerrahi yatak sıvısı veya hemorajik koleksiyon görülebilir; erken ameliyat sonrası serbest hava beklenebildiğinden bu faz tek başına kaçak tanısı koydurmaz.
- Portal tanısal
- İntravenöz kontrastlı BT'de gastrojejunostomi, özofagojejunostomi veya sleeve stapler hattında fokal duvar kesintisi ya da kalınlaşma ile komşu koleksiyon ve inflamatuvar değişiklikler değerlendirilir. Uygun hastada oral suda çözünen kontrast anastomozu geçip lümen dışına çıkıyorsa doğrudan kaçak odağını gösterir.
Önerilen pencereler: Batın (G 400 / M 50), Yumuşak doku (G 400 / M 40).
BT bulguları
- Oral kontrastın anastomoz veya stapler hattı komşuluğunda ekstralüminal birikimi
- Anastomozda fokal duvar kesintisi ya da anastomoz lümeninden dışarı uzanan kontrast
- Anastomozun hemen yanında kümelenen ekstralüminal gaz ve sıvı; koleksiyon gelişmişse çevresel kontrastlanan duvar
- Anastomoz çevresi yağ planlarında çizgilenme ve cerrahi yatak boyunca uzanan peritoneal inflamasyon
- Sol subfrenik veya sol üst kadran koleksiyonu, özellikle gastrojejunostomi ya da özofagojejunostomi komşuluğunda
- Sleeve gastrektomide proksimal stapler hattı yakınında ekstralüminal kontrast, gaz veya organize koleksiyon
- Anastomozdan uzaklaşan fistül traktı ya da yaygın serbest sıvı ve periton içi enfeksiyon bulguları
Normalde
Normal anastomozda opak enterik kontrast bağırsak lümeni içinde devam eder; duvar konturu kapalıdır ve komşu cerrahi yatakta lümene bağlı gaz-sıvı odağı bulunmaz. Erken postoperatif BT'de az miktarda serbest hava görülebileceği için kıyasta havanın anastomozla doğrudan ilişkisini, odaklı sıvı/koleksiyon ve çevre yağ reaksiyonunu, ayrıca önceki incelemeye göre değişimi değerlendir.
Normal BT ile kıyasla
Aynı bölgenin, kaynak veri setinde patoloji içermediği belirtilen bir BT incelemesini kesit kesit kaydırın; organ sınırlarını açarak anatomiyi hasta görüntüsüyle karşılaştırın. Küçük rastlantısal bulgular tümüyle dışlanmamıştır.
Kaynak: TotalSegmentator v2.01 veri seti (Wasserthal ve ark., Radiology: Artificial Intelligence 2023), CC BY 4.0, vaka s0541; organ sınırları veri setinin otomatik segmentasyonundan, birleştirilerek sadeleştirildi. Görüntüler 2,5 mm kesit aralığına yeniden örneklendi.
Ayırıcı tanı
- Beklenen erken postoperatif hava
- anastomoz çevresinde kontrastlı bağlantı veya odaklı inflamatuvar koleksiyon olmadan sınırlı serbest hava bulunabilir.
- Postoperatif seroma
- perianastomotik sıvı hem kaçakta hem geçici postoperatif koleksiyonda görülebilir; sıvı koleksiyonu tek başına bu iki durumu güvenilir biçimde ayırt ettirmez.
- Postoperatif apse
- çevresel kontrastlanan duvar, içeride gaz ve çevre yağ reaksiyonu yapabilir; anastomozla doğrudan bağlantı saptanmadıkça kaynağı tek başına belirlenmiş olmaz.
- Kısa kör jejunal ans
- Roux-en-Y rekonstrüksiyonunda özofagojejunostomi altındaki kısa kör ans kontrastla dolup kaçak gibi görünebilir; jejunuma devamlılığını ve beklenen şeklini izle.
- Viseral perforasyon
- Persistan veya artan pnömoperitoneum, rezidüel postoperatif havaya kıyasla viseral perforasyon şüphesini artırır; bulguyu anastomoz çevresiyle ilişkisiyle birlikte değerlendir.
Tuzaklar
- Erken dönemde yalnız serbest hava kaçak kanıtı değildir; odağın anastomozla ilişkisini, koleksiyonu, duvar bütünlüğünü ve klinik zamanlamayı birlikte değerlendir.
- BT'de anastomoz duvar kesintisinin görülmemesi kaçağı dışlamaz; bu doğrudan bulgu özgül, ancak duyarlılığı düşüktür.
- Roux-en-Y ameliyatında özofagojejunostomi altındaki kısa kör jejunal ans, anastomoz dışına taşmış kontrast gibi görünebilir; beklenen ans konturunu ve jejunuma devamlılığını izle.
- Anastomoz komşuluğundaki dren kateteri kontrastla opaklaşabilir ve bu, kaçağın tek bulgusu olabilir; kateter lümenini koleksiyondan ayır.
Kendini dene
Total gastrektomi sonrası oral kontrast özofagojejunostomiden sol subfrenik koleksiyona geçiyor. En olası komplikasyon nedir?
Cevabı göster
Anastomoz kaçağı. Özofagojejunostomiden lümen dışına uzanan enterik kontrast, anastomoz kaçağını doğrudan gösterir. Seroma ve diğer seçenekler lümenden koleksiyona kontrastlı bağlantıyı açıklamaz.
Gastrik bypassın erken dönem BT'sinde az miktarda serbest hava var; anastomoz çevresinde koleksiyon veya oral kontrast sızıntısı görülmüyor. Hangi yorum doğru?
Cevabı göster
Hava tek başına özgül değil. Ameliyat sonrasında sınırlı serbest hava beklenebilir ve tek başına kaçağı kanıtlamaz. Ekstralüminal kontrast özgül doğrudan bulgudur; duvar kesintisi ve perianastomotik koleksiyon şüpheyi destekleyebilir, ancak sıvı koleksiyonu tek başına seromadan güvenilir biçimde ayırt edilemez.
İlgili konular
Kaynaklar
Bu sayfadaki 38 cümle ve 2 quiz sorusu aşağıdaki kaynaklardan alıntılarla tek tek karşılaştırıldı; 6 cümle bu karşılaştırmada düzeltildi (2026-10-09).
- Normal and Abnormal Postoperative Imaging Findings after Gastric Oncologic and Bariatric Surgerypmc.ncbi.nlm.nih.gov
- Computed Tomography-based Diagnosis of Post-laparoscopic Sleeve Gastrectomy Gastric Leakpubmed.ncbi.nlm.nih.gov
- Early postoperative imaging after non-bariatric gastric resection: a primer for radiologistsrcastoragev2.blob.core.windows.net
- Operative management of acute abdomen after bariatric surgery in the emergency setting: the OBA guidelinescris.unibo.it
- Early postoperative imaging after non-bariatric gastric resection: a primer for radiologistspmc.ncbi.nlm.nih.gov
- Early small bowel obstruction caused by hemobezoar after Roux-en-Y transit bipartition: a case reportpmc.ncbi.nlm.nih.gov
- Posterior nasal hemorrhage mimicking intra-abdominal hemorrhage after gastrectomy: a case reportpmc.ncbi.nlm.nih.gov
- Boerhaave Syndrome Caused by Pancreatitis-Induced Gastric Outlet Obstruction: A Case Reportpmc.ncbi.nlm.nih.gov
- Complications of pancreato-duodenectomy.pubmed.ncbi.nlm.nih.gov
- Anastomotic leakage after gastrointestinal surgery: diagnosis and management.pubmed.ncbi.nlm.nih.gov
- Presentation and surgical management of leaks after mini-gastric bypass for morbid obesity.pubmed.ncbi.nlm.nih.gov
- Imaging of postoperative complications following Ivor-Lewis esophagectomy.pubmed.ncbi.nlm.nih.gov
- Imaging after Bariatric Surgery: When Interpretation Is a Challenge, from Normal to Abnormal.pubmed.ncbi.nlm.nih.gov
- Mini-gastric bypass to control morbid obesity and diabetes mellitus: what radiologists need to know.pubmed.ncbi.nlm.nih.gov
- Diagnostic value of drain amylase for detecting intrathoracic leakage after esophagectomy.pubmed.ncbi.nlm.nih.gov
- Pancreatic atrophy relative to external versus internal drainage of the pancreatic duct after pylorus-preserving pancreaticoduodenectomy.pubmed.ncbi.nlm.nih.gov
- Pancreatic Leak After a Laparoscopic Sleeve Gastrectomy.pubmed.ncbi.nlm.nih.gov
- Clinical outcomes of endoscopic and surgical management for postoperative upper gastrointestinal leakage.pubmed.ncbi.nlm.nih.gov
- Complications of Roux-en-Y gastric bypass and sleeve gastrectomy.pubmed.ncbi.nlm.nih.gov
- Radiation to the Gastric Fundus Increases the Risk of Anastomotic Leakage After Esophagectomy.pubmed.ncbi.nlm.nih.gov
- Usefulness of Clinical Signs and Diagnostic Tests for Suspected Leaks in Bariatric Surgery.pubmed.ncbi.nlm.nih.gov
- Laparoscopic sleeve gastrectomy: imaging of normal anatomic features and postoperative gastrointestinal complications.pubmed.ncbi.nlm.nih.gov
- Outcomes of avoidance of routine nasogastric decompression following elective major gastrointestinal and hepatopancreatobiliary surgery: a single-center prospective observational cohort study.pubmed.ncbi.nlm.nih.gov
- Surgical Management of Recurrent Gastrojejunocolic Fistula With Gastric Antrectomy and Bilateral Vagotomy.pubmed.ncbi.nlm.nih.gov
- Remnant Gastric Necrosis after Laparoscopic Distal Gastrectomy Managed with Double-Elemental Diet Tube and Laparoscopic Gastrojejunostomy: A Case Report.pubmed.ncbi.nlm.nih.gov
- Cholecystogastric fistula masquerading as gastrointestinal stromal tumour: Unusual presentation of gallbladder adenomyomatosis - a case report.pubmed.ncbi.nlm.nih.gov
- Boerhaave Syndrome Caused by Pancreatitis-Induced Gastric Outlet Obstruction: A Case Report.pubmed.ncbi.nlm.nih.gov
- Post-Pancreatectomy Acute Pancreatitis in Pancreatic Cancer: A Single-Center Experience.pubmed.ncbi.nlm.nih.gov
- Prevention, Recognition, and Management of Anastomotic Leakage and Pelvic Sepsis After Rectal Cancer Surgery: A Structured Narrative Review.pubmed.ncbi.nlm.nih.gov
- CT oral contrast and contemporary imaging pathways for suspected oesophageal perforation in the emergency department: a retrospective observational study.pubmed.ncbi.nlm.nih.gov
- Complication imaging after laparoscopic Roux-en-Y gastric bypass: clues to the diagnosis and pitfalls.pubmed.ncbi.nlm.nih.gov
- Case Report: Intrahepatic bile duct injury during adhesiolysis mimicking anastomotic leak.pubmed.ncbi.nlm.nih.gov
- Multifocal small bowel gastrointestinal stromal tumor causing perforation peritonitis: A rare cause of acute abdomen.pubmed.ncbi.nlm.nih.gov
- Surgical Procedures Used in the Treatment of Postoperative Acute Pancreatitis Grade C After Pancreatoduodenectomy-A Narrative Review.pubmed.ncbi.nlm.nih.gov
- Endoscopic Management of Post-Bariatric Surgery Complications: Diagnostic Work-Up and Innovative Approaches for Leak, Fistula, and Stricture Management.pubmed.ncbi.nlm.nih.gov
- Duodenal Trauma: Mechanisms of Injury, Diagnosis, and Management.pubmed.ncbi.nlm.nih.gov
- Radiological Assessment After Pancreaticoduodenectomy for a Precision Approach to Managing Complications: A Narrative Review.pubmed.ncbi.nlm.nih.gov
- Jejunojejunostomy intussusception following conversion from gastric sleeve to gastric bypass: a case report.pubmed.ncbi.nlm.nih.gov
- Acute Limb Ischemia Caused by Distal Embolization from an External Iliac Artery Pseudoaneurysm Associated with a Protruding Acetabular Screw: A Case Report.pubmed.ncbi.nlm.nih.gov
- Oral intake recovery following salvage laryngectomy with circumferential free flap reconstruction in a patient with prior pharyngogastric anastomosis and chemoradiation.pubmed.ncbi.nlm.nih.gov
- Shear wave elastography in the differentiation of intra-abdominal hematoma and abscess.pubmed.ncbi.nlm.nih.gov
- Computed Tomography Imaging of Thoracic Aortic Surgery: Distinguishing Life-Saving Repairs from Life-Threatening Complications.pubmed.ncbi.nlm.nih.gov
- Utility of POCUS (Point of Care Ultrasound) in Renal Transplantation.pubmed.ncbi.nlm.nih.gov
- Endoscopic management for gastrointestinal leaks, perforations, and fistulae: Technical tips and outcomes.pubmed.ncbi.nlm.nih.gov
- VACStent closure of oesophageal defects by covered stent and endoscopic vacuum therapy: initial use and clinical outcomes.pubmed.ncbi.nlm.nih.gov
- Early small bowel obstruction caused by hemobezoar after Roux-en-Y transit bipartition: a case report.pubmed.ncbi.nlm.nih.gov
- Development and internal validation of a prediction model for early anastomotic leak after minimally invasive esophagectomy: a prospective cohort study.pubmed.ncbi.nlm.nih.gov
- Posterior nasal hemorrhage mimicking intra-abdominal hemorrhage after gastrectomy: a case report.pubmed.ncbi.nlm.nih.gov
- Civil medical liability in general surgery: A systematic review.pubmed.ncbi.nlm.nih.gov
- Infectious Complications in Metabolic and Bariatric Surgery: A Comprehensive Narrative Review of Pathophysiology, Prevention, and Management.pubmed.ncbi.nlm.nih.gov
- Case Report: Aortoesophageal fistula after radical gastrectomy for cardia cancer: diagnostic problems and successful staged treatment.pubmed.ncbi.nlm.nih.gov
- Pediatric blunt duodenal injury: a 9-year retrospective single-center series from Vietnam.pubmed.ncbi.nlm.nih.gov
- Perforated Gastric Cancer: Epidemiology, Diagnosis, and Surgical Management Strategies.pubmed.ncbi.nlm.nih.gov
- Exploring the boundaries of anastomotic leak: experience in a high-volume center.pubmed.ncbi.nlm.nih.gov
- Systematic review of the significance of neutrophil to lymphocyte ratio in anastomotic leak after gastrointestinal surgeries.pubmed.ncbi.nlm.nih.gov
- Gastric and peritoneal metastases from breast carcinoma with a mixed ductal-lobular phenotype and aberrant E-cadherin: a case report.pubmed.ncbi.nlm.nih.gov
- A modified endoluminal vacuum therapy system for salvage management of recurrent anastomotic leak after revisional bariatric surgery.pubmed.ncbi.nlm.nih.gov
- Colon Perforation Caused by a Transanal Drainage Tube After Robot-Assisted Low Anterior Resection: A Case Report.pubmed.ncbi.nlm.nih.gov
- Comparison of Clinical Outcomes Between Robot-Assisted Esophagectomy With Total Mesoesophageal Excision and Conventional Minimally Invasive Esophagectomy for Esophageal Cancer.pubmed.ncbi.nlm.nih.gov
- The Stent That Went Too Far: Ascending Colon Perforation Following Gastric Stent Migration.pubmed.ncbi.nlm.nih.gov
- SAGES colorectal and metabolic bariatric surgery committee joint task force call to action for synchronized severe obesity and colorectal cancer management.pubmed.ncbi.nlm.nih.gov
- Traumatic Abdominal Wall Hernia With Sigmoid Colon Transection Following Bicycle Handlebar Injury: A Rare Case Report.pubmed.ncbi.nlm.nih.gov
- Case Report: Use of the over-the-scope clipping system in a trauma patient for a large bowel anastomotic leak.pubmed.ncbi.nlm.nih.gov
- Assessment of Technical and Clinical Success of Percutaneous Transhepatic Biliary Drainage for Postoperative Bile Leaks: A Favorable Alternative to Early Surgical Revision?pubmed.ncbi.nlm.nih.gov
Eğitim amaçlıdır; hasta başında tanı ve tedavi kararının yerine geçmez. İçerik yapay zekâ destekli bir süreçle güncel literatüre göre cümle cümle kaynaklarla karşılaştırıldı, ancak uzman radyolog incelemesinden geçmedi. Klinik kararlarda güncel kılavuzları, kurum protokollerini ve radyoloji raporunu esas alın.