Özet
Paraözofageal hernide mide fundusunun bir bölümü özofagusun yanından hiatusa çıkar; tip II'de gastroözofageal bileşke normal yerinde kalırken tip III'te o da toraksa yükselir. Büyük intratorasik mide toraks içinde kitle etkisi, retansiyon veya mide çıkış obstrüksiyonu oluşturabilir. BT, herni kesesinin içeriğini, bileşkenin konumunu ve mide yönelimini aynı incelemede gösterir; akut başvuruda volvulus ve duvar perfüzyon bozukluğunu araştırır. Herni boynundaki sıkışma ya da iskemi gözden kaçarsa strangülasyon ve perforasyon riski fark edilmeyebilir.
Faz ve pencere
- Kontrastsız tanısal
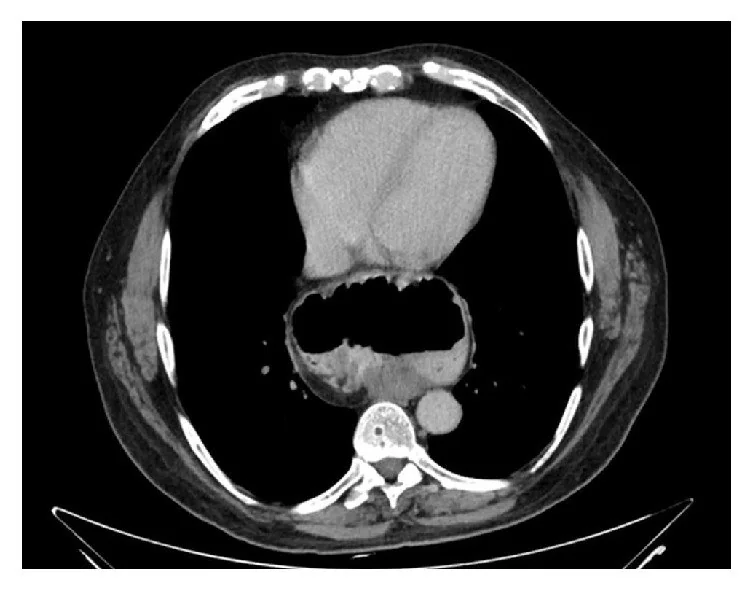
- Hiatus yanında toraksa geçmiş fundus/mide bölümü, mide kıvrımları, hava-sıvı seviyesi ve intratorasik içerik tanımlanabilir; GE bileşkenin yeri çok düzlemli görüntülerde belirlenir.
- Venöz
- Akut komplikasyon şüphesinde mide duvarı kontrastlanması, ödem, perigastrik sıvı ve komşu yağ dokusu değerlendirilir; eşlik eden volvulusun iskemi bulguları bu fazda daha iyi görülür.
Önerilen pencereler G genişlik, M merkez; değerler Hounsfield birimi (HU)
- MediastenG 350 / M +50
- BatınG 400 / M +50
BT bulguları
- Hiatusun yanında torasik fundus — diyafram kruslarının üstünde, distal özofagusun yanında yer alan mide lümeni.
- GE bileşke yerinde, fundus yukarıda — tip II paraözofageal yerleşimin ayırt edici anatomisi.
- GE bileşke ve fundusun birlikte toraksa çıkması — fundusun bileşkeden daha kraniyalde kaldığı tip III görünümü.
- Mide dışı organın herni kesesine girmesi — kolon, ince bağırsak, omentum veya başka visseral içeriği araştırın.
- Herni boynunda mide lümeni daralması — geçişte keskin kalibrasyon değişikliği ve proksimal mide distansiyonu.
- Mide ekseninde rotasyon ve antrum-pilor yer değişikliği — intratorasik mide volvulusu eşlik edebilir.
- Duvar ödemi, azalmış kontrastlanma, perigastrik sıvı veya pnömatozis — komplike hernide iskemi ya da ileri duvar hasarı bulguları.
- Volvulus kuşkusunda mide rotasyonunu organoaksiyel veya mezenterioaksiyel olarak tanımlayın; mide yönelimiyle birlikte herni boynundaki darlığı ve pilordaki geçiş noktasını değerlendirin.
Ölçütler ve sınıflamalar
- Paraözofageal hiatal herni tip II–IV
- Tip II: fundus hiatus yanından toraksa çıkar, GE bileşke normal konumdadır. Tip III: hem GE bileşke hem fundus torakstadır ve fundus bileşkenin üzerindedir. Tip IV: mideye ek olarak başka bir karın organı herni kesesine girer.
Normalde
Normalde fundus sol hemidiyaframın altında, gastroözofageal bileşke hiatusun alt seviyesinde ve özofagus orta hatta/solunda devam eder; posterior mediastende mide kıvrımları bulunmaz. Hiatusu sagittal ve koronal düzlemde izleyerek fundusun özofagus yanından geçip geçmediğini, bileşkenin yerini ve herni içeriğinin mide dışı organ içerip içermediğini kıyaslayın.
Normal BT ile kıyasla
Aynı bölgenin, kaynak veri setinde patoloji içermediği belirtilen bir BT incelemesini kesit kesit kaydırın; organ sınırlarını açarak anatomiyi hasta görüntüsüyle karşılaştırın. Küçük rastlantısal bulgular tümüyle dışlanmamıştır.
Kaynak: TotalSegmentator v2.01 veri seti (Wasserthal ve ark., Radiology: Artificial Intelligence 2023), CC BY 4.0, vaka s1278; organ sınırları veri setinin otomatik segmentasyonundan, birleştirilerek sadeleştirildi. Görüntüler 2,5 mm kesit aralığına yeniden örneklendi.
Ayırıcı tanı
- Tip I kayıcı hiatal herni
- GEJ diyafram üstüne kayar; fundus da genellikle birlikte toraks içinde yer alır.
- Epifrenik divertikül distal özofagusla ilişkili bir divertiküldür ve özofagus motilite bozukluklarıyla ilişkili olabilir.
- Mediastinal neoplazmlar ayırıcı tanıda düşünülebilir; hiatal herni içinde pankreas herniasyonu varsa BT’de damarların toraksa uzanışını gösteren “vasküler döngü” bulgusu, bunu mediastinal neoplazmdan ayırmaya yardımcı olabilir.
- Mide pull-up rekonstrüksiyonu
- cerrahi anastomoz ve rezeksiyon sonrası değişmiş mide anatomisiyle ayırt edilir.
Tuzaklar
- Tek aksiyel kesitte GE bileşke seçilmeyebilir; tip II ile tip III ayrımı için distal özofagusu hiatus boyunca koronal-sagittal düzlemde takip edin.
- Herni içindeki mide gazı retro-kardiyak akciğer kavitesi sanılabilir; mide duvar kıvrımlarını ve lümenin hiatusa devamını doğrulayın.
- Herni kesesindeki kolon veya ince bağırsak tip IV'ü düşündürür; toraks içindeki her gazlı visserayı mide olarak adlandırmayın.
- Geniş herni tek başına akut volvulus anlamına gelmez; anormal eksen, obstrüksiyon geçişi ve iki daralma noktasını ayrıca arayın.
Kendini dene
Fundus hiatus yanından toraksa çıkmış, ancak GE bileşke diyafram altında normal yerinde. Bu hangi tiptir?
Cevabı göster
Tip II paraözofageal. Tip II'de fundus özofagus yanında herniye olurken GE bileşke yerinde kalır. Tip I'de bileşke yükselir; Tip III'te fundusla bileşke birlikte yükselir; Tip IV'te mide dışı organlar da keseye katılır.
İntratorasik mideye ek olarak transvers kolonun da herni kesesinde olduğu görülüyor. Sınıflama nedir?
Cevabı göster
Tip IV hiatal herni. Mide dışı bir karın organının herni kesesine girmesi tip IV tanımına uyar. Diğer tipler kolon gibi ek visseral içeriği içermez.
İlgili konular
Kaynaklar
Bu sayfadaki 41 cümle ve 2 quiz sorusu aşağıdaki kaynaklardan alıntılarla otomatik olarak karşılaştırıldı; 4 cümle bu karşılaştırmada düzeltildi (2026-10-09).
- The Fundoplication Revision of a Recurrent Large Paraesophageal Hiatal Hernia in a 63-Year-Old Femalepmc.ncbi.nlm.nih.gov
- Perforated Cameron's Ulcer from Incarcerated Paraesophageal Hernia with Gastric Volvuluspmc.ncbi.nlm.nih.gov
- A rare pediatric case of type III congenital paraesophageal hiatal hernia with infantile hypertrophic pyloric stenosis: A case reportpmc.ncbi.nlm.nih.gov
- Robot-Assisted Laparoscopic Hiatal Hernia Repair in a Patient With Right Aortic Arch: Implications for Surgical Planning and Symptom Resolutionpmc.ncbi.nlm.nih.gov
- Laparoscopic repair of a primary parahiatal hernia combined with gastric volvulus: a case report and literature reviewpmc.ncbi.nlm.nih.gov
- Congenital Paraesophageal Hernia in a Cat.pubmed.ncbi.nlm.nih.gov
- Gastric necrosis following a hiatal hernia: A case report.pubmed.ncbi.nlm.nih.gov
- Large hiatus hernia: time for a paradigm shift?pubmed.ncbi.nlm.nih.gov
- Woman with recurrent vomiting.pubmed.ncbi.nlm.nih.gov
- Post-Esophagectomy Hiatal Hernia: A Case Series.pubmed.ncbi.nlm.nih.gov
- Morphology of the Esophageal Hiatus: Is It Different in 3 Types of Hiatus Hernias?pubmed.ncbi.nlm.nih.gov
- Experience with laparoscopic treatment for paraesophageal hiatal hernia.pubmed.ncbi.nlm.nih.gov
- Successful laparoscopic management of paraesophageal hiatal hernia with upside-down intrathoracic stomach: a case report.pubmed.ncbi.nlm.nih.gov
- Gastric Cancer Arising from an Upside-Down Stomach through a Paraesophageal Hiatal Hernia.pubmed.ncbi.nlm.nih.gov
- Laparoscopic repair of complete intrathoracic stomach with iron deficiency anemia: A case report.pubmed.ncbi.nlm.nih.gov
- Resolution of megaesophagus after correction of a paraesophageal hernia.pubmed.ncbi.nlm.nih.gov
- Robotic Surgical Repair of a Parahiatal Hernia: A Case Report.pubmed.ncbi.nlm.nih.gov
- Transverse colon incarceration and necrosis in a hiatal hernia: a case report.pubmed.ncbi.nlm.nih.gov
- Iatrogenic Gastric Perforation Following Emergency Endoscopic Decompression for Obstructive Shock Caused by an Incarcerated Hiatal Hernia: A Case Report.pubmed.ncbi.nlm.nih.gov
- Strangulated Giant Paraesophageal Hernia Resulting in Ischemia and Perforation: A Case Report.pubmed.ncbi.nlm.nih.gov
- Fatal gastric volvulus: forensic pathology considerations and postmortem CT findings.pubmed.ncbi.nlm.nih.gov
- Role of interventional pulmonology in intensive care units: A scoping review.pubmed.ncbi.nlm.nih.gov
- BRAZILIAN HERNIA AND ABDOMINAL WALL SOCIETY STATEMENT ON LARGE HIATAL HERNIAS MANAGEMENT.pubmed.ncbi.nlm.nih.gov
- Autologous Posterior Rectus Sheath as a Vascularized Onlay Flap: a Novel Approach to Hiatal Hernia Repair.pubmed.ncbi.nlm.nih.gov
- Perforated Cameron's Ulcer from Incarcerated Paraesophageal Hernia with Gastric Volvulus.pubmed.ncbi.nlm.nih.gov
- Successful Hiatal Hernia Repair in a 95-Year-Old Patient: A Case Report.pubmed.ncbi.nlm.nih.gov
- Twist in the Bowel: A Multimodality Radiological Imaging Spectrum.pubmed.ncbi.nlm.nih.gov
- Gastric outlet obstruction in uncomplicated mesentero-axial gastric volvulus associated to hiatal hernia.pubmed.ncbi.nlm.nih.gov
- Hiatal Hernia With Gastric Perforation.pubmed.ncbi.nlm.nih.gov
- CT of Gastric Volvulus: Interobserver Reliability, Radiologists' Accuracy, and Imaging Findings.pubmed.ncbi.nlm.nih.gov
- Age-stratified outcomes of laparoscopic hiatal hernia repair with Nissen fundoplication in children: a single-center experience.pubmed.ncbi.nlm.nih.gov
- Standardized W-H fundoplication procedure for gastroesophageal reflux disease (2026).pubmed.ncbi.nlm.nih.gov
- Grade IV hiatal hernia in a neonate: A radiologic mimic of congenital diaphragmatic hernia.pubmed.ncbi.nlm.nih.gov
- Hiatal Herniapubmed.ncbi.nlm.nih.gov
- The "ABCD" framework for assessment: a task-oriented approach to reconcile multimodal diagnostic discordance.pubmed.ncbi.nlm.nih.gov
- Management of complicated diaphragmatic hernia in the acute setting: a WSES position paper.pubmed.ncbi.nlm.nih.gov
- Hiatal Hernia with Prolapse of the Pancreas Causing Bile Duct Stricture and Liver Function Disorders: A Case Report and Literature Review.pubmed.ncbi.nlm.nih.gov
- A Comparative Assessment of the Diagnosis of Swallowing Impairment and Gastroesophageal Reflux in Canines and Humans.pubmed.ncbi.nlm.nih.gov
- Laparoscopic distal gastrectomy with simultaneous hiatal repair for gastric cancer associated with a paraesophageal hernia containing the small intestine: a case report.pubmed.ncbi.nlm.nih.gov
- A Massive Type IV Hiatal Hernia With Gastric Volvulus and the Complicated Road to Recovery.pubmed.ncbi.nlm.nih.gov
- Removal of the sac during surgery for the repair of "giant" paraesophageal hernias.pubmed.ncbi.nlm.nih.gov
- Does laparoscopic surgery decrease the risk of atrial fibrillation after foregut surgery?pubmed.ncbi.nlm.nih.gov
- Patterns of injury and violence in Yaoundé Cameroon: an analysis of hospital data.pubmed.ncbi.nlm.nih.gov
- Secondary Mesenteroaxial Gastric Volvulus in an Elderly Female: A Rare Presentation of an Occult Diaphragmatic Hernia.pubmed.ncbi.nlm.nih.gov
- Gastric Volvulus as a Rare Sequelae of a Hiatal Hernia: A Case Report and Review of the Literature.pubmed.ncbi.nlm.nih.gov
- Gastric Volvulus After Nissen Fundoplication: A Case Report.pubmed.ncbi.nlm.nih.gov
- Mesenteroaxial Gastric Volvulus: A Case Report.pubmed.ncbi.nlm.nih.gov
- Radiological Confirmation of Enteral Feeding Tube Placement Before Initiating Enteral Nutrition: A Review.pubmed.ncbi.nlm.nih.gov
- Three-dimensional computed tomography reconstruction of the gastroesophageal junction following hiatal hernia repair with Collis gastroplasty and fundoplication: a novel method to demonstrate postoperative morphology and better understand hiatal hernia recurrence.pubmed.ncbi.nlm.nih.gov
- Beyond the Diaphragm: Grynfeltt-Lesshaft Hernia Presenting With Small Bowel Obstruction.pubmed.ncbi.nlm.nih.gov
- Cameron Lesions: Endoscopic Characteristics, Clinical Profile, and Therapeutic Implications-A Retrospective Study of 43 Patients.pubmed.ncbi.nlm.nih.gov
- Surgical repair of paraesophageal hernia resolves unexplained iron deficiency anemia in the vast majority of patients: a propensity-matched multicenter study.pubmed.ncbi.nlm.nih.gov
- A retrospective comparative study comparing laparoscopic and robotic hiatal hernia repair: surgical outcomes, recurrence rate, and postoperative morbidity.pubmed.ncbi.nlm.nih.gov
- Sliding hiatal hernia detected by transnasal esophagogastroscopy is associated with poorer treatment response in reflux-associated globus sensation.pubmed.ncbi.nlm.nih.gov
- Evaluation of resection of the gastroesophageal junction and jejunal interposition (Merendino procedure) as a rescue procedure in patients with a failed redo antireflux procedure. A single-center experience.pubmed.ncbi.nlm.nih.gov
- Esophagogastric junction outflow obstruction: Where are we now in diagnosis and management?pubmed.ncbi.nlm.nih.gov
- Clinical Practice Update: The Use of Per-Oral Endoscopic Myotomy in Achalasia: Expert Review and Best Practice Advice From the AGA Institute.pubmed.ncbi.nlm.nih.gov
- Prenatal ultrasound diagnosis of a rare morgagni hernia: a case report.pubmed.ncbi.nlm.nih.gov
- Minimally Invasive Sampling of Mediastinal Lesions.pubmed.ncbi.nlm.nih.gov
- Japanese Clinical Practice Guidelines for Vascular Tumors, Vascular Malformations, Lymphatic Malformations, and Lymphangiomatosis 2022.pubmed.ncbi.nlm.nih.gov
- Oral intake recovery following salvage laryngectomy with circumferential free flap reconstruction in a patient with prior pharyngogastric anastomosis and chemoradiation.pubmed.ncbi.nlm.nih.gov
- Emergency Minimally Invasive Esophagogastrectomy and Delayed Esophagocoloplasty for Caustic Ingestion: A Stepwise Video-Based Approach.pubmed.ncbi.nlm.nih.gov
- Does Omitting Distal Anastomosis in Hypopharyngeal Defect Reconstruction Improve Dietary Outcomes?pubmed.ncbi.nlm.nih.gov
- Mesentero-axial gastric volvulus in an old woman: a case report of a diagnostic challenge.pubmed.ncbi.nlm.nih.gov
- A case report on secondary mesentero-axial gastric volvulus.pubmed.ncbi.nlm.nih.gov
- The lymphatic system and sentinel lymph nodes: conduit for cancer metastasis.pubmed.ncbi.nlm.nih.gov
- Pediatric emergency medicine point-of-care ultrasound: summary of the evidence.pubmed.ncbi.nlm.nih.gov
- Giant Type IV hiatal hernia with intrathoracic migration of abdominal viscera and atypical clinical presentation: a case report.pubmed.ncbi.nlm.nih.gov
- The Wandering Pancreas: A Rare Case of Complex Hiatal Hernia Presenting With Thoracic Symptoms.pubmed.ncbi.nlm.nih.gov
- A case report of occult Cameron ulcer and a systematic review of the literature.pubmed.ncbi.nlm.nih.gov
- Symmetrical anterior-posterior partial fundoplication: technique and outcomes.pubmed.ncbi.nlm.nih.gov
- The Biological Conservative Reconstruction (BIOCORN) Procedure: Redefining Surgical Treatment of Gastroesophageal Reflux Disease (GERD) and Hiatal Hernia Through Anatomical Preservation.pubmed.ncbi.nlm.nih.gov
- The Fundoplication Revision of a Recurrent Large Paraesophageal Hiatal Hernia in a 63-Year-Old Female.pubmed.ncbi.nlm.nih.gov
- A Pancreas Out of Place: Acute Interstitial Pancreatitis Caused by Pancreatic Herniation in a Type IV Paraesophageal Hernia.pubmed.ncbi.nlm.nih.gov
- The Predilection of Specific Diseases to Affect Different Sections of the Esophagus.pubmed.ncbi.nlm.nih.gov
- Bronchopulmonary malformation of the foregut communicating with the distal Oesophagus in a form of an Epiphrenic diverticulum. An exceptional cause of epiphrenic diverticulum in adults: Case report.pubmed.ncbi.nlm.nih.gov
- Esophageal diverticula: from diagnosis to therapeutic management-narrative review.pubmed.ncbi.nlm.nih.gov
- Esophageal and Oropharyngeal Dysphagia: Clinical Recommendations From the United European Gastroenterology and European Society for Neurogastroenterology and Motility.pubmed.ncbi.nlm.nih.gov
- Dots, lines, contours, and ends: An image-based review of esophageal pathology.pubmed.ncbi.nlm.nih.gov
- Extrinsic Left Atrial Compression: An Echocardiography-Guided Diagnosis Illustrated by Two Clinical Cases and a Structured Review of Published Cases.pubmed.ncbi.nlm.nih.gov
- LOOPS for thought: identifying gastrointestinal pathology on transthoracic echocardiography.pubmed.ncbi.nlm.nih.gov
- Tension Gastrothorax in a Child With Undiagnosed Congenital Diaphragmatic Hernia: A Case Report and Proposed Emergency Management Algorithm.pubmed.ncbi.nlm.nih.gov
- Giant Hiatal Hernia Mimicking Acute Coronary Syndrome: A Case Report.pubmed.ncbi.nlm.nih.gov
- Tension gastrothorax in late diagnosis of congenital diaphragmatic hernia.pubmed.ncbi.nlm.nih.gov
- Diagnostic challenges of hiatal hernia Type IV: An imaging perspective.pubmed.ncbi.nlm.nih.gov
- IDEAL Phase 2a Results: Posterior Rectus Sheath Flap for Hiatal Augmentation in Complex Paraesophageal Hernias.pubmed.ncbi.nlm.nih.gov
- A Rare Case of Omental Strangulation Through the Esophageal Hiatus Successfully Repaired Through a Robotic-Assisted Approach.pubmed.ncbi.nlm.nih.gov
- Pancreas in the chest: Diaphragmatic hernia with obstruction.pubmed.ncbi.nlm.nih.gov
- Clinical features and imaging findings for a mediastinal hemangiosarcoma in a dog.pubmed.ncbi.nlm.nih.gov
- Gastric Volvulus, Pancreatic Volvulus, and Wandering Spleen: A Rare Emergency Triad Behind Acute Abdomen.pubmed.ncbi.nlm.nih.gov
Eğitim amaçlıdır; hasta başında tanı ve tedavi kararının yerine geçmez, tıbbi tavsiye değildir. Metinler yapay zekâ desteğiyle yazıldı ve otomatik bir adımda kaynak alıntılarıyla karşılaştırıldı; bu bir tıbbi doğrulama değildir ve içerik uzman radyolog incelemesinden geçmedi. Klinik kararlarda güncel kılavuzları, kurum protokollerini ve radyoloji raporunu esas alın.